

Stem Cell Therapy for Autoimmune Diseases
Autoimmune Diseases and Stem Cell Therapy Germany
An individualised treatment programme with cell-free MSC secretome (MSEC) and autologous bone marrow concentrate (BMC) for adults with autoimmune diseases such as multiple sclerosis (MS) and rheumatoid arthritis (RA). MSEC is given into the cerebrospinal fluid in MS and into a vein in RA; BMC is injected into affected joints. Offenbach, Germany. Experimental — fully legal — manufactured under German regulatory authorisation and official inspection since 2018.
Autoimmune diseases occur when the immune system mistakenly attacks the body’s own tissues. Depending on the condition, this can affect joints, the nervous system, or other organs, leading to ongoing inflammation and loss of normal function. Dr. mult. Stehling and ANOVA IRM have treated 48 people with autoimmune diseases since 2016 (as of October 2026).
Treatment is typically focused on suppressing immune activity and managing symptoms. While this can help reduce flare-ups, it does not always change how the disease progresses over time.
Stem cell therapy for autoimmune diseases is being explored as a different approach. Rather than focusing only on suppression, it is being investigated for its potential to influence how immune responses are regulated within the body.
At ANOVA Institute for Regenerative Medicine (ANOVA IRM), treatment is focused on selected autoimmune conditions where stem cell-based therapies may be considered as part of a medically guided approach. It is offered alongside — never instead of — the treatment by your rheumatologist or neurologist.
| Component | Detail |
|---|---|
| Two products | Bone Marrow Concentrate (BMC) and Mesenchymal Stem Cell Secretome (MSEC), each manufactured under official authorisation; no marketing authorisation (experimental) |
| Authorisations | BMC § 20b / § 13 AMG · MSEC § 20b / § 20c AMG (German Medicines Act) |
| Location | Offenbach am Main, Germany |

Autoimmune diseases in brief, the conditions we treat and the programme with its three components — the essentials at a glance.
You are hereIntroduction & Summary
What are autoimmune diseases, in brief?
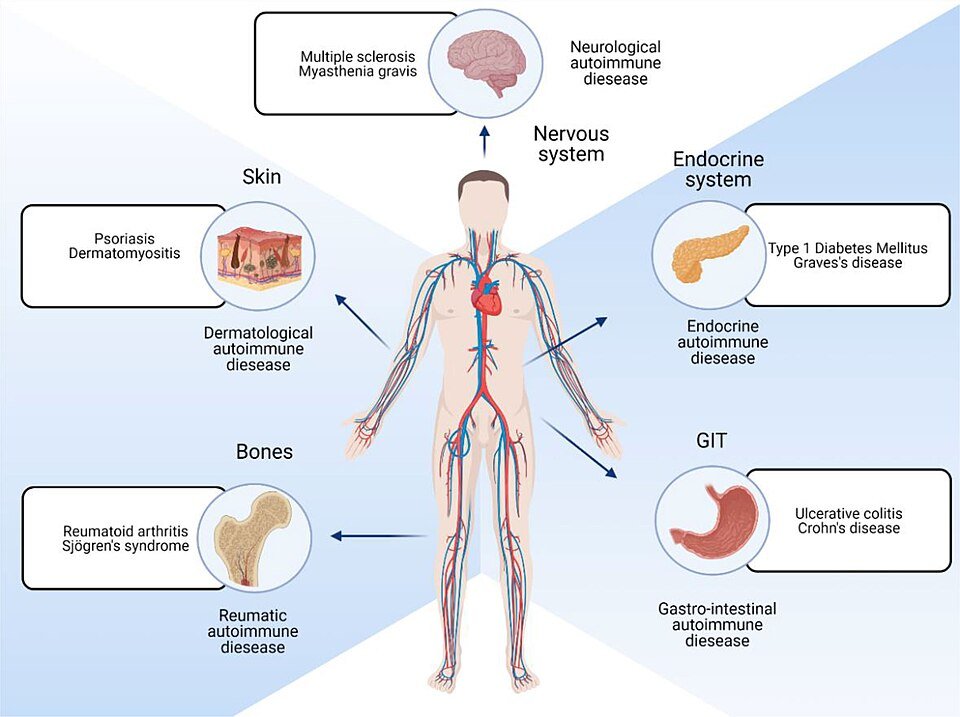
In autoimmune diseases, the immune system no longer reliably tells the body’s own tissue apart from foreign invaders such as bacteria or viruses. Many different autoimmune diseases are known. Some affect a single organ, such as the brain and spinal cord in multiple sclerosis; others affect several organs, such as rheumatoid arthritis, which starts in the joints.[5] In a study of 22 million people in the UK, about one in ten had at least one of 19 common autoimmune diseases, women about twice as often as men.[1]
Typical complaints, depending on the disease, are:
- Tiredness (fatigue) and a general feeling of illness
- Painful, swollen joints and morning stiffness
- Numbness, weakness, unsteady gait or visual disturbances
- Skin rashes, recurring fever or digestive problems
Many autoimmune diseases run in flare-ups and calmer phases. To date no cure is known for most autoimmune diseases. More details can be found below in our scientific section on autoimmune diseases.
Autoimmune Diseases Treated at ANOVA IRM
These are the primary autoimmune conditions treated at ANOVA IRM, each involving persistent immune activity that contributes to ongoing disease progression.
Multiple Sclerosis (MS)
Multiple sclerosis (MS) is an autoimmune disease where the immune system attacks the myelin sheath insulating nerve fibres in the central nervous system. As this protective covering breaks down, nerve signalling is disrupted, affecting movement, coordination, sensation, and other neurological functions.
As this damage progresses, communication between the brain and body becomes increasingly impaired. Treatment therefore aims to limit further disruption to nerve signalling and support overall neurological function.
At ANOVA IRM, stem cell-based therapies are applied with the aim of influencing activity within the central nervous system.
Learn more about stem cell treatment for multiple sclerosis →
Rheumatoid Arthritis (RA)
Rheumatoid arthritis is a chronic autoimmune disease in which the immune system attacks the joint lining, causing inflammation, pain, swelling, and progressive joint damage. Over time, this reduces mobility and disrupts normal joint function.
This damage is not simple wear and tear but a sustained process affecting the synovial tissue and surrounding structures. As it progresses, joint stability becomes harder to maintain and overall function declines. Treatment aims to slow disease progression, while joint-level therapies are being investigated for their potential to support function in affected areas, even as the underlying autoimmune process continues.
At ANOVA IRM, secretome-based therapies are applied with the aim of influencing inflammatory activity. Where joints are already affected, treatment may be combined with Bone Marrow Concentrate (BMC) for local application within the joint.
Learn more about stem cell treatment for rheumatoid arthritis →
What is the ANOVA autoimmune diseases programme?
ANOVA offers autologous mesenchymal stem cell secretome (MSEC) and bone marrow concentrate (BMC) for autoimmune diseases. The programme has three components: a diagnostic MRI, MSEC given into the cerebrospinal fluid or a vein, and BMC injected into affected joints. Each component is selected individually; the programme is not a fixed package.
In autoimmune diseases, immune cells keep the affected tissue inflamed. Stem cells are thought to communicate with these immune cells, mainly through the messengers they release, the mesenchymal stem cell secretome. MSEC and BMC are intended to dampen this immune over-reaction and to reduce the inflammation that drives ongoing damage. MSEC is aimed at the immune reaction in the nervous system or throughout the body, BMC at individual joints.
ANOVA IRM has not yet tested MSEC or BMC for autoimmune diseases in a clinical study. The current state of research is described in the clinical and scientific section below.
The ANOVA Autoimmune Diseases Programme — Components
Diagnostic MRI
In MS, an MRI of the brain and spinal cord shows which lesions are active; in RA, an MRI with contrast shows inflamed joint lining. From this we see where the disease is active and which product, route and site suit you. Before MSEC, an MRI of the abdominal wall is also needed to exclude a hernia before the fat collection.
MSC secretome (MSEC)
MSEC is the cell-free mixture of signalling molecules, including exosomes, released by your own mesenchymal stromal cells from fat tissue. The fat is collected in a mini-liposuction under brief sedation. In MS, MSEC is given into the cerebrospinal fluid (intrathecally); in RA with many inflamed joints, into a vein. One production yields 10 doses for a longer treatment period.
Bone marrow concentrate (BMC)
BMC is made from your own bone marrow, collected from the pelvic bone under brief sedation, concentrated, tested and injected into an affected joint on the same day, during a two-day visit. In autoimmune diseases we use BMC when rheumatoid arthritis has already damaged individual joints.
Which diagnostics do we use for autoimmune diseases at ANOVA IRM?
Autoimmune diseases can look alike and change over time, so we first look at how active your disease is and where. Dr. Stehling, founder of ANOVA IRM, is a radiologist and physicist. We work with the Prof. Dr. Stehling Institut für Bildgebende Diagnostik GmbH, which, like ANOVA IRM, belongs to Dr. Stehling and is located in the same building.
Which tests are used to diagnose autoimmune diseases?
The diagnosis is made by your rheumatologist or neurologist from the medical history, the examination, blood tests and imaging. Blood tests look for autoantibodies, such as rheumatoid factor and anti-CCP in RA, and for inflammation markers such as CRP. In MS, MRI of the brain and spinal cord and, where needed, the cerebrospinal fluid are examined; in RA, ultrasound and MRI show inflamed joint lining earlier than X-ray.
What do we review before autoimmune disease treatment at ANOVA IRM?
Before any treatment decision we review your diagnosis, how active the disease is, which organs or joints are affected and which medication you take. We also check whether you are fit for the brief sedation needed for tissue collection.
With MSEC:
- Standard: an MRI of the abdominal wall to exclude a hernia before the liposuction, no more than four weeks old.
- Optional: MRI of the brain and spinal cord in MS, or of affected joints in RA, with contrast to assess inflammatory activity.
- Optional: CT guidance for the application into the cerebrospinal fluid in MS.
With BMC:
- Standard: no MRI required.
- Optional, often useful: arthro-MRI or MRI with contrast to show active inflammation in a joint.
Your own doctors at home can carry out these examinations; please send us the results. They can also be done in-house. If you would like existing findings assessed independently, we offer a second opinion. The full diagnostic pathway is described on our diagnostics page.
Why ANOVA IRM for autoimmune diseases?
Dr. mult. Stehling and ANOVA IRM have been treating people with autoimmune diseases since 2016; 48 people so far, including 38 with multiple sclerosis and 7 with rheumatoid arthritis (as of October 2026).
ANOVA IRM has manufactured MSEC and BMC in its own facility in Offenbach since 2018, under official authorisations and regular inspection. Imaging is led by radiologists in the same building, and an anaesthesiologist looks after you during tissue collection. Why an autologous product used only for our own patients requires no marketing authorisation is explained on our regulatory status page. Standard care comes first: the treatment by your rheumatologist or neurologist remains the basis, and MSEC and BMC are offered in addition to it.
What can you expect as a patient with an autoimmune disease?
Initial evaluation can begin remotely, by phone or video, without travel to Germany. Treatment itself requires visits to Offenbach am Main, less than 20 minutes from Frankfurt Airport. You receive an individual written cost estimate before any treatment decision.
Quick answers
Is there a cure for autoimmune diseases?
Not for most of them. Medication that suppresses or modulates the immune system can bring many autoimmune diseases into a calm phase, but it usually has to be taken continuously.[6] In selected severe cases, for example aggressive MS, a haematopoietic stem cell transplant is used. MSEC and BMC at ANOVA IRM are experimental options alongside this therapy, not a cure.
Is stem cell therapy a cure for autoimmune diseases?
No. Stem cell therapy is not considered a cure for autoimmune diseases. It is an experimental approach that is being investigated for a possible influence on disease activity and inflammation. It does not eliminate the underlying condition, and outcomes vary between patients.
Is stem cell therapy for autoimmune diseases legal in Germany?
Yes, if the provider holds the required official authorisations. ANOVA IRM manufactures MSEC under a procurement authorisation (Section 20b AMG) and a manufacturing authorisation under Section 20c AMG, and BMC under Section 20b and a manufacturing authorisation under Section 13 AMG. Both are given as an individual therapeutic attempt; see our regulatory status page.
Is stem cell therapy for autoimmune diseases safe?
Not without qualification: like any medical therapy, it carries risks, here from tissue collection, brief sedation and the application itself. Your doctor explains these risks to you beforehand. Because the products are autologous, made from your own cells, no donor tissue is involved. An official authorisation adds safety, because the competent authority inspects the facility every two years and every change to the process and every new material must be reported to it. Providers without an authorisation are not checked in this way. Since 2016 Dr. mult. Stehling and ANOVA IRM have used the same process for MSEC, under an authorisation according to Section 20c AMG since 2018, and 355 people have been treated with it. BMC has been made with the same process since 2012. After a pause from 2017 due to a change in German law, it has been manufactured again since 2019 under an authorisation according to Section 13 AMG, and 153 people have received it since then. As of October 2026, neither product has caused a serious adverse event. Clinical research first checks safety in phase 1/2 studies with roughly 10 to 100 patients. ANOVA IRM has not conducted such a study, but the number of people treated with MSEC is well above that. Ask every provider to show its authorisations; the regulators’ view is summarised under unproven therapies.
What medication is used for autoimmune diseases?
Medication that suppresses or modulates the immune system is the basis: cortisone for flare-ups, disease-modifying drugs such as methotrexate in rheumatoid arthritis and interferons or ocrelizumab in multiple sclerosis, and biologics such as TNF inhibitors.[3],[4] MSEC and BMC at ANOVA IRM are given in addition to this medication, not instead of it.
Who qualifies, what the process actually involves, and what it costs — step by step.
You are hereAutoimmune Disease Treatment: Eligibility, Process & Cost
In this section you will find everything about treatment for autoimmune diseases at ANOVA IRM: who is eligible, the process step by step and the cost.
What does the autoimmune disease treatment timeline look like?
- 01
Remote assessment
Review of your diagnosis, current medication and images by email, phone or video; two weeks to a few months, depending on available appointments.
- 02
Screening at home
Blood test and existing findings before you travel, to avoid an unnecessary journey.
- 03
First visit (two days)
Day 1: consultation, consent, blood tests and, if useful, MRI. Day 2 with MSEC: mini-liposuction under brief sedation. Day 2 with BMC: bone marrow collection, preparation, testing and injection into the joint.
- 04
MSEC production
About four weeks of production and quality control; 10 doses, stored for up to two years.
- 05
Application and follow-up
MSEC according to your plan over several visits; review of your progress together with your rheumatologist or neurologist.
Who May Be Considered for Stem Cell Therapy for Autoimmune Diseases?
Stem cell-based therapies may be considered for patients with autoimmune disorders such as multiple sclerosis or rheumatoid arthritis, particularly where progression continues despite standard treatment.
Suitability depends on multiple factors, including diagnosis, disease stage, overall health, and functional status. Patients must be medically fit for the procedure and the required tissue harvesting, with eligibility determined through detailed medical evaluation.
Learn more about the diagnostic work-up →
Considering Stem Cell Therapy for an Autoimmune Disease?
Autoimmune diseases can present differently depending on how they affect the body, which is why treatment decisions require careful evaluation of both the condition and the individual patient.
At ANOVA IRM, treatment decisions are based on medical history, current therapies, and diagnostic findings, which can be submitted in advance or completed as part of the process. Consultations may then be used to review these findings and discuss whether stem cell-based therapy may be appropriate.
Consultations can begin remotely, with on-site evaluation available where further diagnostic work-up is needed.
What are the contraindications for autoimmune disease treatment?
Our treatments are experimental. We treat only people for whom, after medical assessment, we consider the benefit-risk balance to support treatment.
Applies to all ANOVA treatments:
- Active cancer within the last two years
- Under the age of legal majority
- Pregnancy or breastfeeding
- Active infectious disease (hepatitis A, B, C, HIV, syphilis or other)
Specific to autoimmune diseases:
- Infection of a joint, or of the skin at the injection or collection site
- Unable to breathe unaided, or difficulty breathing in the supine position (sedation for tissue collection)
- Severe difficulty swallowing (dysphagia), because of the sedation
- Psychiatric disorder that would prevent informed consent or cooperation
Immunosuppressive medication and blood thinners are not in themselves contraindications, but please tell us about them before your visit.
How Stem Cell Therapy for Autoimmune Diseases Is Applied at ANOVA IRM
Treatment at ANOVA IRM is not based on a single protocol. Instead, it follows a standardized clinical process, with application method and timing varying depending on the condition and patient.
Key elements of this approach include:
- Autologous stem cell sourcing: Therapies use cells derived from the patient’s own body, including adipose tissue or Bone Marrow Concentrate (BMC). Autologous material is used because it does not introduce foreign donor cells, which may reduce the risk of immune reactions compared to donor-based treatments.
- Focus on mesenchymal stem cells (MSCs): Selected because their immunomodulatory properties are the subject of ongoing laboratory and early clinical research, particularly in conditions where immune activity contributes to ongoing disease processes.
- Use of the MSC secretome (MSEC): Treatment focuses on signalling molecules released by stem cells, which are being investigated in research for their influence on immune signalling pathways rather than for suppression alone.
- Controlled processing and quality standards: All stem cell products are prepared, tested, and handled under strict stem cell therapy protocols for quality, consistency, and traceability.
- Diagnostics-led treatment planning: Therapy is guided by diagnostic findings and individual patient factors to determine whether treatment is appropriate and how it should be applied.
- Regulated medical framework: Treatments are performed under German regulatory authorisation and regular official inspection; details are given under production and quality control below.
- Structured treatment protocols: Depending on the condition, therapy may involve repeated applications over time as part of a broader treatment strategy.
Learn more about the stem cell therapies used at ANOVA IRM →
What screening is needed before you travel for autoimmune disease treatment?
A short screening in your home country helps you avoid a journey that would not lead to treatment. It usually consists of a blood test for infections and other reasons against treatment, plus your recent images and the letters of your rheumatologist or neurologist.
What happens at your first visit to Offenbach for an autoimmune disease?
The first visit takes two consecutive days in Offenbach and is outpatient. On day one, your doctor explains the treatment, obtains your consent and takes blood; an MRI can be added. With MSEC, a small amount of abdominal fat is collected on day two, and the first dose follows about four weeks later. With BMC, bone marrow is taken from the pelvic bone on day two and injected into the affected joint a few hours later.
How are your MSEC and BMC produced and quality-controlled?
MSEC: Mesenchymal stromal cells are isolated from the fat tissue and expanded in our own facility, under official authorisation and officially inspected good professional practice (GFP, gute fachliche Praxis; similar to Good Tissue Practice, GTP, in the US, but more than GTP). The cells produce your MSEC preparation, the signalling molecules they release, not the living cells. Production and quality control take about four weeks and yield 10 doses, stored at −80 °C for up to two years.
BMC: BMC is prepared on the day of collection in our own facility, under a manufacturing authorisation (Section 13 AMG) and good manufacturing practice (GMP). The bone marrow is concentrated but not multiplied; key quality tests are completed before the injection.
How are MSEC and BMC applied in autoimmune diseases?
Because autoimmune diseases are chronic and there is currently no cure for most of them, we recommend a longer-term MSEC treatment using all 10 doses produced rather than a single application; see the timeline above. MSEC and BMC are intended to influence the course of the disease, not to cure it.
The schedule is set individually for each patient, for example:
- MSEC: two doses at the start, then, if you live close by, one dose every 4 to 6 weeks.
- If you live further away: a double dose every 3 months, so that the 10 doses produced are used over about 15 months.
- Route in MS: into the cerebrospinal fluid (intrathecally) by lumbar puncture. This is intended to bring the secretome closer to the spinal cord and brain than an infusion into the bloodstream, which would have to cross the blood–brain barrier.
- Route in RA: MSEC into a vein (intravenous) when many joints are inflamed; BMC into individual affected joints (intra-articular).
Intrathecal applications are standard procedures when performed by experienced physicians; where the anatomy requires it, ANOVA IRM uses CT guidance from the radiology in the same building. The benefit-risk assessment of intrathecal administration is set out on a separate page.
What does autoimmune disease treatment with MSEC or BMC cost?
MSEC treatment for autoimmune diseases costs approximately €20,000 to €36,000, and BMC for affected joints approximately €8,000 to €9,000; both are billed according to the German Medical Fee Schedule (GOÄ). For MSEC, the base package of the mini-liposuction and the first three doses costs approximately €20,000. Each further dose costs approximately €2,250 to €2,350, depending on the route. With BMC, the cost is closer to €9,000 where CT guides the injection, otherwise closer to €8,000. Further examinations and your sedation wishes also affect the total, and you receive an individual written estimate before any decision. Our blog post on treatment cost explains the main cost factors. Travel and accommodation are not included. All prices are subject to change.
With MSEC, a double liposuction is possible and yields 20 doses from one collection. The cost is correspondingly higher and is shown in your estimate.
Why does the cost of autoimmune disease treatment vary?
All treatments at ANOVA IRM are billed according to the German Medical Fee Schedule (Gebührenordnung für Ärzte, GOÄ). In autoimmune diseases, the cost depends mainly on the product, the number of MSEC doses and the route: into the cerebrospinal fluid in MS, into a vein in RA, or BMC into a joint. Your written cost estimate shows the exact amount.
Frequently asked questions — autoimmune diseases: eligibility, process and travel
Who is a candidate for stem cell therapy for autoimmune diseases?
Candidates are typically patients with diagnosed autoimmune conditions and ongoing disease activity despite standard therapy. Suitability depends on factors such as disease stage, overall health, and whether the procedure is medically appropriate, which is determined through a detailed evaluation.
How are MSEC and BMC administered for autoimmune diseases?
How long does stem cell therapy for autoimmune diseases take?
Does health insurance cover stem cell therapy for autoimmune diseases in Germany?
Should I continue my existing autoimmune disease therapy with my rheumatologist or neurologist?
How often do I need to travel to Germany for stem cell therapy for autoimmune diseases?
With MSEC, a two-day collection visit is followed by visits for the doses: every 4 to 6 weeks if you live close by, otherwise a double dose every 3 months. With BMC alone, usually once for two days. From Frankfurt Airport, Offenbach can be reached in less than 20 minutes. Every step of the visits is described on our MSC secretome page.
What medical records should I send for an autoimmune disease assessment?
Please send us your most recent documents; we will ask if we need anything else. Helpful are, for example, letters from your rheumatologist or neurologist, recent blood tests with autoantibodies and inflammation markers, MRI images and a list of your current medication. Large image files can be transferred online; we send you the instructions.
Does ANOVA IRM treat international patients with autoimmune diseases?
Yes. We advise patients with autoimmune diseases from abroad in English, and the first assessment takes place by email, phone or video, so no travel is needed at this stage.
Causes of autoimmune diseases, the standard of care, the rationale for MSEC and BMC and all references.
You are hereAutoimmune Diseases: Clinical & Scientific Evidence
Understanding Autoimmune Diseases
To understand how stem cell therapy may be applied, it is important to look at how immune control breaks down in autoimmune disease.
These conditions are driven by a loss of immune tolerance, meaning the body can no longer reliably distinguish between its own tissues and external threats, leading to immune responses being directed against healthy tissue.
While the affected tissues vary, many autoimmune diseases share common biological patterns, including:
- ongoing inflammatory signalling that disrupts normal tissue function
- failure of normal immune regulation that allows responses to remain active
- cumulative damage caused by repeated immune-mediated injury
Because this activity is continuous rather than triggered by a single event, damage tends to build over time. This is why many autoimmune diseases follow a pattern of flare-ups and progression that can be difficult to fully control.

What causes autoimmune diseases, and what are the risk factors?
The causes of autoimmune diseases are not fully understood. A genetic predisposition and environmental triggers act together; in identical twins, both develop the same autoimmune disease in only 12 to 67 per cent of cases, which points to environmental and chance factors.[2] Known risk factors are:
- Genes, for example certain variants of the HLA genes, which control immune responses
- Female sex; hormones are thought to play a part
- Infections, which may trigger an immune reaction against the body’s own tissue
- Smoking and other environmental factors
- An existing autoimmune disease, because a second one is more common in people who already have one[1]
What drives the progression of autoimmune diseases?
The trigger of an autoimmune disease and what drives it forward are two separate questions. Once the disease has started, immune cells and their messengers keep the affected tissue inflamed and recruit further immune cells. The longer this inflammation remains active, the more tissue is damaged, for example myelin in MS or cartilage and bone in RA. Our programme is aimed at this inflammation and the course of the disease, not at its original cause.
What is the standard of care for autoimmune diseases?
The standard of care depends on the disease and is led by rheumatologists, neurologists and other specialists; current recommendations are summarised for RA by EULAR and for MS in a review.[3],[4] It includes:
- Cortisone (glucocorticoids) for flare-ups
- Conventional disease-modifying drugs such as methotrexate in rheumatoid arthritis
- Disease-modifying therapies in MS, such as interferons, glatiramer acetate or ocrelizumab
- Biologics, for example TNF inhibitors, and JAK inhibitors as tablets
- Physiotherapy, occupational therapy and rehabilitation
In selected severe cases, for example aggressive relapsing MS, an autologous haematopoietic stem cell transplant (aHSCT) is established; it replaces the immune system after high-dose chemotherapy.[6] CAR-T cell therapy from cancer medicine is being researched in severe autoimmune diseases such as lupus.[7] The standard of care for each disease is described on our pages on multiple sclerosis and rheumatoid arthritis.

Important: This is the established standard of care. ANOVA IRM’s programme is offered alongside — not in place of — appropriate established treatment.
How are autoimmune diseases diagnosed, and what do we not do ourselves?
Autoimmune diseases are diagnosed by specialists from the history, the examination, blood tests for autoantibodies and inflammation markers, and imaging. The diagnosis, the medication and its monitoring stay with your rheumatologist or neurologist. MRI and CT, including CT guidance for an application into the cerebrospinal fluid, are carried out at the Institut für Bildgebende Diagnostik in the same building, which also belongs to Dr. Stehling.
How Stem Cell Therapy Is Thought to Work in Autoimmune Diseases
Stem cell-based therapies are being investigated for their potential to influence dysregulated immune activity and reduce chronic inflammation.
Mesenchymal stem cells (MSCs) are central to this approach because of how, in external laboratory studies, they have been observed to interact with immune cells involved in ongoing inflammation. External laboratory and preclinical research suggests that, instead of targeting a single pathway, they may moderate how immune responses are regulated more broadly.
This possible effect is thought to rely mainly on paracrine signalling, including the release of signalling molecules known as the MSC secretome (MSEC). In external laboratory research, these factors have been observed to influence inflammatory signalling and how the local environment responds to ongoing immune processes.[12],[13]
The hypothesis is that, as this environment becomes less driven by persistent inflammation, the affected area could become more stable. This could help support function and reduce the cycle of ongoing tissue damage over time; it has not yet been shown in clinical studies.
Stem cell-based therapies are not considered a cure, but are experimental approaches that aim to influence disease activity and support function in selected patients.
Mesenchymal stromal cell secretome — what the terms mean
Mesenchymal stem cells and mesenchymal stromal cells are two names for the same cells, abbreviated MSC. The International Society for Cell & Gene Therapy recommends “mesenchymal stromal cells” for the cells grown in the laboratory, and “stem cells” only where stem cell properties have been demonstrated.[10],[11] The mesenchymal stromal cell secretome is therefore the same as the mesenchymal stem cell secretome, or MSC secretome: the mixture of growth factors, cytokines, microRNAs and extracellular vesicles such as exosomes that these cells release.[12]
MSC secretome (MSEC)
ANOVA IRM has not yet tested MSEC for autoimmune diseases in a clinical study. In external laboratory and animal studies, extracellular vesicles of the mesenchymal stromal cell secretome changed the behaviour of immune cells involved in inflammation. They converted inflammatory macrophages and dendritic cells into calming forms and increased regulatory T cells.[13] These studies used laboratory preparations, not MSEC. They provide background for the rationale, not direct evidence for MSEC.
Bone marrow concentrate (BMC)
BMC itself has not been studied in autoimmune diseases, to our knowledge. In a small external phase 1/2 study, 15 patients with rheumatoid arthritis of the knee received cultured mesenchymal stromal cells from their own bone marrow into the joint, and 15 received saline. Pain and function improved more with the cells, but the advantage could not be maintained beyond 12 months.[17] These cells were multiplied in the laboratory and differ from BMC.
Mesenchymal stem cells in clinical studies of autoimmune diseases
External clinical studies have tested mesenchymal stem cells in rheumatoid arthritis, type 1 diabetes, multiple sclerosis, lupus, inflammatory bowel disease and other autoimmune diseases; most were small and early.[14] In an external meta-analysis of mostly small, uncontrolled studies in MS, about 40 per cent of patients improved after mesenchymal stem cells, about a third remained stable and about 18 per cent worsened.[15] Without control groups, these figures do not show an effect. In a meta-analysis of 11 randomised external studies of haematopoietic and mesenchymal stem cells with 691 patients with MS, a benefit over the control treatment could not yet be demonstrated.[16] These studies used living cells, not MSEC or BMC.
What is the efficacy hypothesis behind MSEC and BMC in autoimmune diseases?
In autoimmune diseases, the problem is an immune over-reaction that keeps tissue inflamed. The hypothesis is that the soluble factors of the mesenchymal stem cell secretome communicate with the immune cells involved and help to rebalance them. MSEC in the cerebrospinal fluid or a vein is intended to act on the immune reaction in the nervous system or throughout the body, BMC in the joint on local inflammation and pain.
Talk to us about current changes or additions to the autoimmune diseases programme.
Where does our own evidence on autoimmune diseases stand?
We have not yet evaluated our own data on autoimmune diseases. This section therefore summarises published external evidence, not our own patient outcomes. Some patients describe their experience on our testimonials page; these are individual accounts, not evidence that a treatment works.
What the published evidence on autoimmune diseases does not yet tell us
- Most clinical studies of mesenchymal stem cells in autoimmune diseases are small, early and of short duration.
- They used cultured or donor cells, which differ from MSEC and BMC at ANOVA IRM in source, preparation and dose.
- In a meta-analysis of randomised studies in MS with haematopoietic and mesenchymal stem cells, a benefit over control could not yet be demonstrated; long-term safety data are lacking.
- In Germany and the EU, no stem cell-based treatment is approved as a standard treatment for multiple sclerosis or rheumatoid arthritis.
Legal framework for MSEC and BMC in autoimmune diseases
For autoimmune diseases, ANOVA IRM uses two products. MSEC is an autologous tissue preparation, manufactured under a procurement authorisation (Section 20b AMG) and a manufacturing authorisation under Section 20c AMG. BMC is an advanced therapy medicinal product, manufactured under a procurement authorisation (Section 20b AMG) and a manufacturing authorisation (Section 13 AMG). All authorisations were issued and are regularly inspected by the Hessian State Office for Health and Care (HLfGP). The individual treatment attempt (individueller Heilversuch) concerns the administration only and follows full disclosure and informed consent. As both products are used only for our own patients, no authorisation under Section 4b, no marketing authorisation under Section 21 and no approval under Section 21a AMG is required. More on our regulatory status page.
Frequently asked questions — autoimmune diseases, evidence and approval status
Is stem cell therapy approved for autoimmune diseases?
Not as an MSC or secretome product for multiple sclerosis or rheumatoid arthritis, to our knowledge, in Germany, the EU or the US. An autologous haematopoietic stem cell transplant is established in selected severe autoimmune diseases, such as aggressive MS; it is a different therapy from MSEC.[6] Crohn’s disease is an immune-mediated bowel disease. For its fistulas, a donor-cell product was authorised in the EU in 2018 and withdrawn in 2024 after an external phase 3 study could not demonstrate a benefit over placebo.[8] In South Korea, an autologous product for these fistulas has been approved since 2012.[9] ANOVA IRM gives MSEC and BMC as an individual therapeutic attempt after individual medical assessment and informed consent.
Are MSC studies evidence that MSEC or BMC works in autoimmune diseases?
Are stem cell therapies for autoimmune diseases supported by research or clinical trials?
Stem cell therapies for autoimmune diseases have been studied in external clinical research, clinical studies, and clinical trials in conditions such as multiple sclerosis and rheumatoid arthritis, as well as other different autoimmune diseases.[14] Most of them were small phase 1 and 2 studies. Current clinical evidence continues to evolve, and more research is needed to better understand long-term clinical outcomes.
What results can I expect from stem cell therapy for autoimmune diseases?
Stem cell-based therapies aim to reduce inflammatory activity and support more stable disease progression. Whether and how much an individual patient benefits cannot be predicted; it depends on the specific disease, its stage and your overall health. As with other therapies for autoimmune diseases, patient outcomes can vary.
What types of stem cells are used at ANOVA IRM for autoimmune diseases?
ANOVA IRM uses two autologous products for autoimmune diseases. Mesenchymal stem cell secretome (MSEC) is produced from mesenchymal stromal cells from your own fat tissue and is itself cell-free. Bone marrow concentrate (BMC) from your own pelvic bone contains mesenchymal and haematopoietic stem cells in their natural composition. Details are on our MSC secretome page and our BMC page.
Does ANOVA use embryonic or pluripotent stem cells for autoimmune diseases?
No. ANOVA IRM uses adult autologous stem cells only and does not use embryonic stem cells or induced pluripotent stem cells.
Is stem cell therapy for autoimmune diseases the same as a stem cell transplant or hematopoietic stem cell transplantation?
No. ANOVA IRM’s approach is different from a stem cell transplant or hematopoietic stem cell transplantation. It does not involve high dose immunosuppression, replacement of the immune system, or creation of a new immune system.[6] It is also different from allogeneic transplants that use donor stem cells and carry risks such as graft versus host disease.
How common are autoimmune diseases?
Common. In a UK study of 22 million people, about one in ten had at least one of 19 common autoimmune diseases: about 13 per cent of women and 7 per cent of men. Between 2000 and 2019, new diagnoses rose by about 4 per cent.[1]
What are the symptoms of autoimmune diseases?
The symptoms depend on which tissue the immune system attacks, and many begin gradually. Common symptoms of autoimmune diseases are:
- Fatigue, low-grade fever and a general feeling of illness
- Joint pain, swelling and stiffness, as in rheumatoid arthritis
- Numbness, weakness, balance and vision problems, as in multiple sclerosis
- Skin rashes, hair loss, dry eyes or mouth and digestive complaints in other autoimmune diseases
Which forms of autoimmune diseases are there, and how do they progress?
Doctors distinguish autoimmune diseases that affect one organ from those that affect several organs or the whole body.[5] How they develop depends on the disease and its therapy.
- Organ-specific: for example multiple sclerosis (brain and spinal cord), type 1 diabetes (pancreas) or Hashimoto’s thyroiditis (thyroid).
- Systemic: for example rheumatoid arthritis, lupus or Sjögren’s syndrome, which can affect joints, skin, blood vessels and internal organs.
- Course: often in flare-ups with calmer phases in between; some forms, such as progressive MS, worsen steadily.
What complications can autoimmune diseases cause?
Persistent inflammation can permanently damage the affected tissue, for example joints in rheumatoid arthritis or nerve fibres in multiple sclerosis, and lead to disability. Medication that suppresses the immune system raises the risk of infections. In addition, people with one autoimmune disease develop a second one more often than others.[1]
Important Pages
Questions people usually ask next. Each is answered in full on its own page.
- Who are we?
- Is ANOVA legal?
- Is stem cell therapy safe?
- What is MSEC (MSC Secretome)?
- What is BMC (Bone Marrow Concentrate)?
- What are stem cells?
- What should I ask when looking for a stem cell treatment?
- Which conditions do we treat?
- Rheumatoid arthritis treatment options — standard and emerging
- Benefit-risk assessment of intrathecal administration
- Does the secretome pass the blood–brain barrier?
Affiliations of ANOVA
ANOVA IRM shares its premises in Offenbach with two further institutions owned by Dr. Stehling: the Institut für Bildgebende Diagnostik (IBDO), providing MRI and CT imaging, and the VITUS PRIVATKLINIK Prof. Dr. Stehling GmbH. Because imaging is carried out in the same building, condition-specific diagnostics — including MRI with contrast and CT-guided applications — can be performed in-house rather than referred elsewhere. See diagnostics at ANOVA IRM.
References — autoimmune diseases literature
Specific literature is maintained on the pages for multiple sclerosis and rheumatoid arthritis, and general literature on the MSC secretome and BMC pages.
Autoimmune diseases — frequency, mechanisms and standard of care
- [1] Conrad N, Misra S, Verbakel JY, et al. Incidence, prevalence, and co-occurrence of autoimmune disorders over time and by age, sex, and socioeconomic status: a population-based cohort study of 22 million individuals in the UK. Lancet. 2023;401(10391):1878–1890. doi:10.1016/S0140-6736(23)00457-9. PMID: 37156255.
- [2] Wang L, Wang FS, Gershwin ME. Human autoimmune diseases: a comprehensive update. J Intern Med. 2015;278(4):369–395. doi:10.1111/joim.12395. PMID: 26212387.
- [3] Smolen JS, Landewé RBM, Bergstra SA, et al. EULAR recommendations for the management of rheumatoid arthritis with synthetic and biological disease-modifying antirheumatic drugs: 2022 update. Ann Rheum Dis. 2023;82(1):3–18. doi:10.1136/ard-2022-223356. PMID: 36357155.
- [4] McGinley MP, Goldschmidt CH, Rae-Grant AD. Diagnosis and treatment of multiple sclerosis: a review. JAMA. 2021;325(8):765–779. doi:10.1001/jama.2020.26858. PMID: 33620411.
- [5] Davidson A, Diamond B. Autoimmune diseases. N Engl J Med. 2001;345(5):340–350. doi:10.1056/NEJM200108023450506. PMID: 11484692.
- [6] Alexander T, Greco R, Snowden JA. Hematopoietic stem cell transplantation for autoimmune disease. Annu Rev Med. 2021;72:215–228. doi:10.1146/annurev-med-070119-115617. PMID: 33106103.
- [7] Mackensen A, Müller F, Mougiakakos D, et al. Anti-CD19 CAR T cell therapy for refractory systemic lupus erythematosus. Nat Med. 2022;28(10):2124–2132. doi:10.1038/s41591-022-02017-5. PMID: 36109639.
Approval status
- [8] European Medicines Agency. Alofisel withdrawn from the EU market. Amsterdam: EMA; 13 December 2024. https://www.ema.europa.eu/en/news/alofisel-withdrawn-eu-market (accessed 9 October 2026).
- [9] Ministry of Food and Drug Safety (MFDS), Republic of Korea. Bio & Cosmetics — Manufactures: Cupistem (autologous adipose-derived stem cells, Anterogen), approved in January 2012 for Crohn’s fistula. https://www.mfds.go.kr/eng/brd/m_30/view.do?seq=71337 (accessed 9 October 2026).
Mesenchymal stromal cells and their secretome — terms and mechanisms
- [10] Dominici M, Le Blanc K, Mueller I, et al. Minimal criteria for defining multipotent mesenchymal stromal cells. The International Society for Cellular Therapy position statement. Cytotherapy. 2006;8(4):315–317. doi:10.1080/14653240600855905. PMID: 16923606.
- [11] Viswanathan S, Shi Y, Galipeau J, et al. Mesenchymal stem versus stromal cells: International Society for Cell & Gene Therapy (ISCT®) Mesenchymal Stromal Cell committee position statement on nomenclature. Cytotherapy. 2019;21(10):1019–1024. doi:10.1016/j.jcyt.2019.08.002. PMID: 31526643.
- [12] Vizoso FJ, Eiro N, Cid S, et al. Mesenchymal stem cell secretome: toward cell-free therapeutic strategies in regenerative medicine. Int J Mol Sci. 2017;18(9):1852. doi:10.3390/ijms18091852. PMID: 28841158.
- [13] Harrell CR, Jovicic N, Djonov V, et al. Mesenchymal stem cell-derived exosomes and other extracellular vesicles as new remedies in the therapy of inflammatory diseases. Cells. 2019;8(12):1605. doi:10.3390/cells8121605. PMID: 31835680.
Mesenchymal stem cells in autoimmune diseases — clinical studies (other products than MSEC and BMC)
- [14] Jasim SA, Yumashev AV, Abdelbasset WK, et al. Shining the light on clinical application of mesenchymal stem cell therapy in autoimmune diseases. Stem Cell Res Ther. 2022;13(1):101. doi:10.1186/s13287-022-02782-7. PMID: 35255979.
- [15] Islam MA, Alam SS, Kundu S, et al. Mesenchymal stem cell therapy in multiple sclerosis: a systematic review and meta-analysis. J Clin Med. 2023;12(19):6311. doi:10.3390/jcm12196311. PMID: 37834955.
- [16] Maji S, Mishra A, Srinivasan A, Maiti R. Efficacy and safety of hematopoietic and mesenchymal stem cells in multiple sclerosis: a meta-analysis. Neurol Res. 2026;48:96–106. doi:10.1080/01616412.2025.2521712. PMID: 40566801.
- [17] Shadmanfar S, Labibzadeh N, Emadedin M, et al. Intra-articular knee implantation of autologous bone marrow-derived mesenchymal stromal cells in rheumatoid arthritis patients with knee involvement: results of a randomized, triple-blind, placebo-controlled phase 1/2 clinical trial. Cytotherapy. 2018;20(4):499–506. doi:10.1016/j.jcyt.2017.12.009. PMID: 29428486.