

Translational Medicine — Works in Progress
The ANOVA Incontinence Stem Cell Treatment Programme Germany
Autologous bone marrow concentrate (BMC) or cell-free MSC secretome (MSEC) therapy for people with urinary incontinence (UI), mainly stress urinary incontinence (SUI) in women and in men after prostate surgery. The product is chosen case by case, with BMC as our first choice. Offenbach, Germany. Experimental — fully legal — manufactured under German regulatory authorisation and official inspection since 2018.
You have tried a lot. Perhaps you have been told there is nothing more to be done. We listen first, examine thoroughly, and then tell you honestly whether a stem cell-based therapy, one of our programmes or another option could be right for you. Each option is discussed as an addition to your current treatment, never as a replacement.
| Component | Detail |
|---|---|
| Two products | Bone Marrow Concentrate (BMC) and Mesenchymal Stem Cell Secretome (MSEC), each manufactured under official authorisation; no marketing authorisation (experimental) |
| Authorisations | BMC § 20b / § 13 AMG · MSEC § 20b / § 20c AMG (German Medicines Act) |
| Location | Offenbach am Main, Germany |

Urinary incontinence in brief, the programme and its components — the essentials at a glance.
You are hereIntroduction & Summary
What is urinary incontinence (UI), in brief?
Urinary incontinence (UI), often called bladder weakness, means any involuntary leakage of urine. Urine is held in the bladder by the urethral sphincter, a ring of muscle around the urethra, and by the muscles and connective tissue of the pelvic floor. If the sphincter or its support is weakened, the closure can no longer withstand a sudden rise in pressure in the abdomen. It is common: a quarter to almost half of adult women report some leakage of urine.[1]
Doctors distinguish stress urinary incontinence (SUI), with leakage on coughing, laughing, sneezing or lifting, from urge incontinence, in which a sudden urge cannot be held back. Both together are called mixed incontinence. In women, pregnancy, vaginal birth, overweight and the menopause are the main causes of SUI.[3],[4],[5] In men, SUI usually follows surgery on the prostate, such as radical prostatectomy for prostate cancer or a transurethral resection of the prostate (TURP).[6] To date no treatment is known that restores a weakened or damaged urethral sphincter.
The diagnosis rests on the medical history, a bladder diary, a physical examination and a urine test; a pad test, ultrasound and pressure measurements of the bladder (urodynamics) may follow. MRI, with contrast where needed, can show the pelvic floor and the sphincter.
Common symptoms are leakage on physical effort, a sudden strong urge, passing urine often, waking at night to pass urine and the need for pads.
More details can be found below in our scientific section on urinary incontinence.


What is the ANOVA urinary incontinence (UI) programme?
ANOVA offers bone marrow concentrate (BMC) or mesenchymal stem cell secretome (MSEC) for urinary incontinence, mainly stress urinary incontinence; we choose the product case by case, with BMC as our first choice. The programme combines a diagnostic MRI of the pelvic floor and the urethral sphincter with BMC or MSEC injected locally around the urethral sphincter. Each component is selected individually; the programme is not a fixed package. Urinary incontinence belongs to our area of translational medicine — works in progress, in which each treatment is planned case by case.
In stress urinary incontinence, the sphincter muscle, its nerves and its blood supply are damaged — by childbirth and age in women, by surgery in men — and scar tissue can form. Stem cells are thought to act mainly through the factors they release, the secretome. BMC and MSEC, injected locally around the urethral sphincter, are intended to potentially influence the function of the remaining sphincter muscle through its muscle fibres, nerves and blood vessels. They are not intended to replace a sphincter that has been destroyed.
ANOVA IRM has not yet tested BMC or MSEC for urinary incontinence in a clinical study. The current state of research is described in the clinical and scientific section below.

The ANOVA UI Programme — Components
Pelvic floor and sphincter MRI
With BMC, an MRI before treatment is not mandatory, but it can be very useful. With MSEC, an MRI of the abdominal wall is required before the mini-liposuction to exclude a hernia. A dynamic MRI shows how the pelvic floor moves when you strain, and a high-resolution MRI shows the urethral sphincter itself. Both help to decide whether BMC or MSEC is suitable and where exactly it should be applied.
Bone marrow concentrate (BMC)
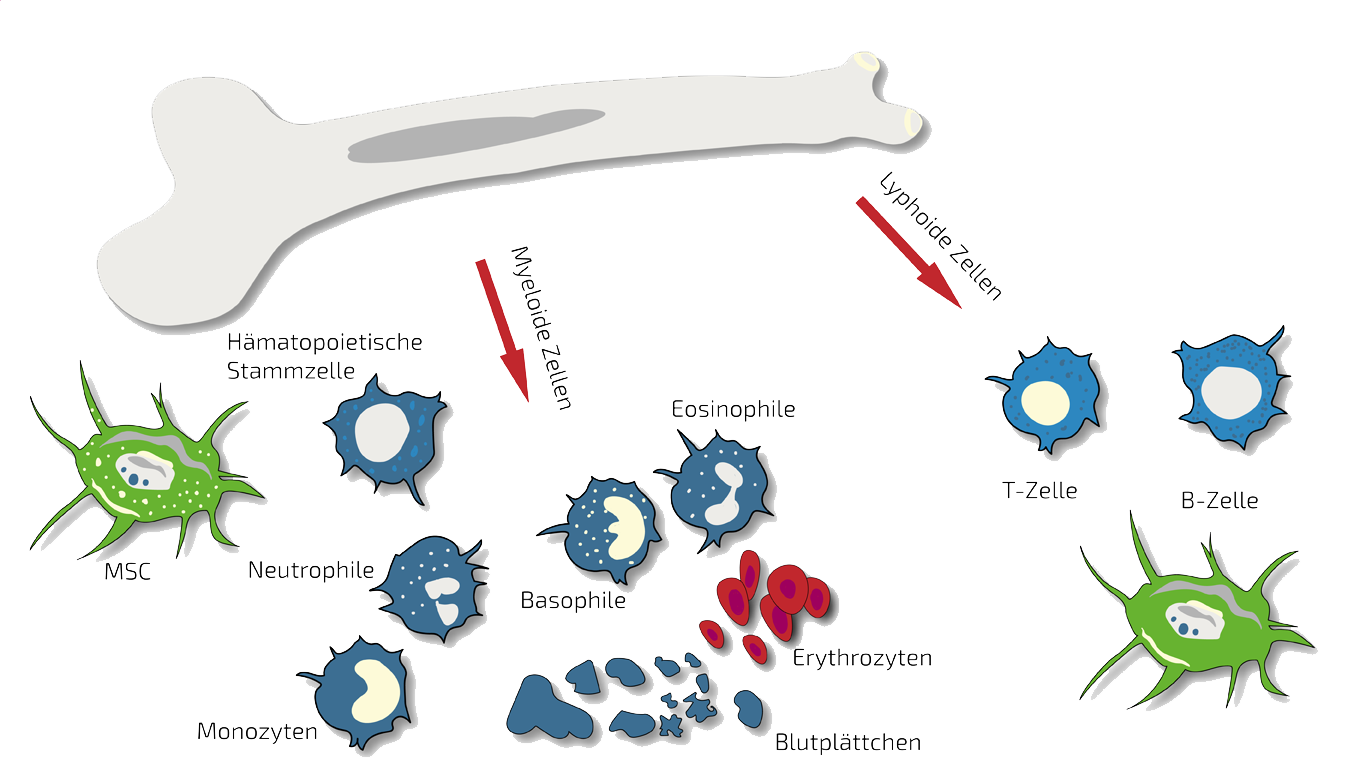
BMC contains your own adult stem cells, haematopoietic and mesenchymal stem cells in their natural composition, together with growth factors. It is collected from the pelvic bone under brief sedation, concentrated, tested and injected locally around the urethral sphincter on the same day. Small external studies with other cell products injected at the sphincter reported less leakage in some women and men.[16],[19] The current state of research is set out in the clinical and scientific section below.
MSC secretome (MSEC)
MSEC contains the signalling molecules released by your own mesenchymal stromal cells, which are grown from fat tissue obtained in a mini-liposuction. It is injected locally around the urethral sphincter over several sessions: after a two-day visit for tissue collection, further visits follow for the applications of your plan. In laboratory and animal studies, such cell-free factors may support the muscle and nerve fibres of an injured sphincter.[21] The current state of research is set out in the clinical and scientific section below.
Which diagnostics do we use for urinary incontinence at ANOVA IRM?
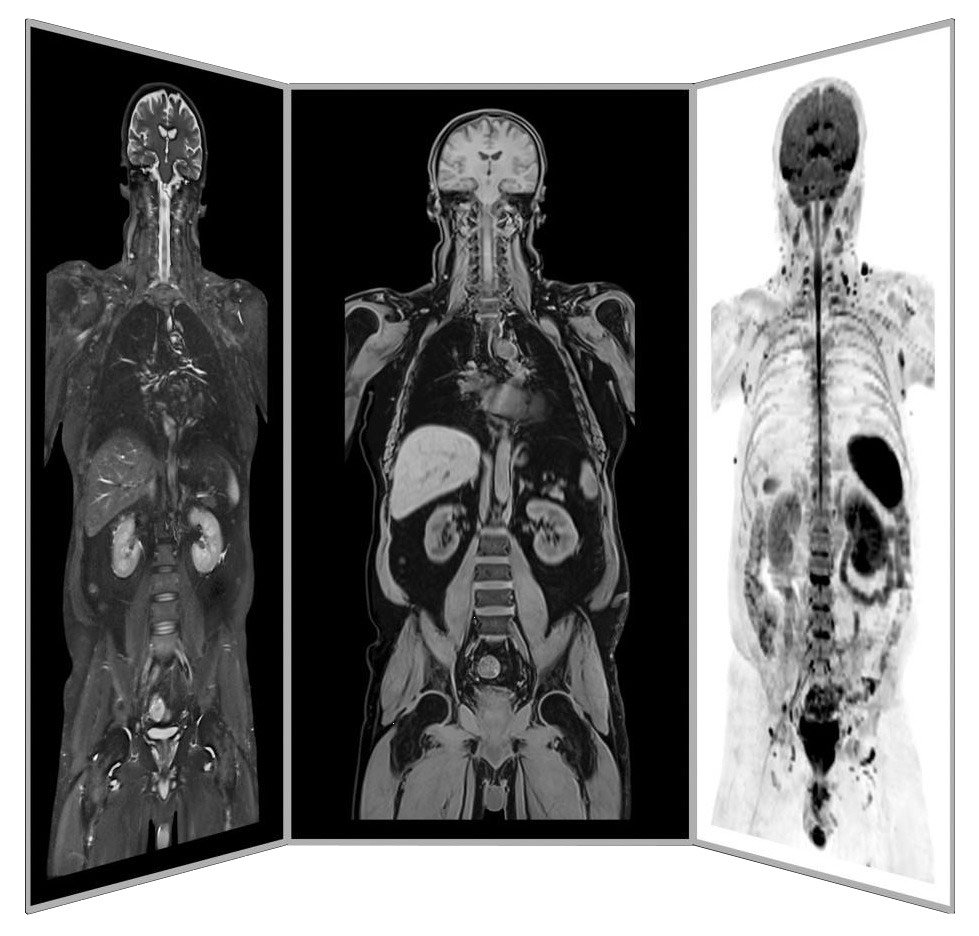
Together with the Prof. Dr. Stehling Institut für Bildgebende Diagnostik GmbH, which also belongs to Dr. Stehling and is located in the same building, we have developed MRI methods for the pelvic floor. They include dynamic MRI of the pelvic floor under strain and high-resolution MRI of the urethral sphincter. These images show us whether BMC or MSEC is suitable and where it should be applied.
Which tests are used to diagnose urinary incontinence?
Diagnosis starts with your history, a bladder diary over several days, a questionnaire on leakage and quality of life, a physical examination and a urine test to rule out infection.[9] A cough stress test and a pad test show how much urine is lost. Ultrasound measures the urine left in the bladder after voiding. Before an operation, pressure measurements of the bladder and urethra (urodynamics) are often added. MRI, with contrast where needed, shows the pelvic floor, the sphincter and, in men, the length of the urethra below the prostate.[7],[8]
What do we review before urinary incontinence treatment at ANOVA IRM?
Before any treatment decision we review which type of incontinence you have and how severe it is, and which treatments and operations you have already had. In men after prostate surgery, we also review the reports on the cancer, the operation and your latest PSA results. We check that you can safely have the brief sedation needed for the bone marrow collection (BMC) or the mini-liposuction (MSEC).
With BMC:
- Standard: no MRI required.
- Optional: further diagnostic MRI, with or without contrast, where your incontinence situation calls for it — for example a dynamic MRI of the pelvic floor or a high-resolution MRI of the urethral sphincter.
- Optional: ultrasound guidance while BMC is injected at the sphincter.
With MSEC:
- Standard: an MRI of the abdominal wall to exclude a hernia is required before the liposuction, taken no more than four weeks beforehand. It can be done at home or at ANOVA IRM.
- Optional: ultrasound guidance while MSEC is injected at the sphincter.
- Optional: further MRI scans, with or without contrast, where your incontinence situation calls for them — for example a dynamic MRI of the pelvic floor.
All of these examinations can also be carried out by your own doctors at home; please send us the results. For your convenience they can also be done in-house. The full diagnostic pathway is described on our diagnostics page.
© Siemens Healthcare GmbH.
Why ANOVA IRM for urinary incontinence?
The pelvic floor MRI methods described above are carried out in the same building, so the injection at the sphincter can be planned with imaging. ANOVA IRM has manufactured BMC and MSEC in its own facility in Offenbach since 2018; why neither requires a marketing authorisation is set out on our regulatory status page.
What can you expect as a patient with urinary incontinence?
The first assessment can take place remotely, by phone or video, before any journey to Germany. Treatment itself takes place in person in Offenbach am Main, less than 20 minutes from Frankfurt Airport. Before you decide, you receive an individual written cost estimate; the services of our patient care team are free of charge. If you would like existing findings assessed independently, we also offer a second opinion.
Quick answers
Is there a cure for urinary incontinence (UI)?
Often, depending on the type. Stress urinary incontinence can often be cured or clearly improved with pelvic floor muscle training or an operation, such as a mid-urethral sling in women or an artificial urinary sphincter in men.[11],[12],[14] Urge incontinence is usually controlled rather than cured. Bone marrow concentrate (BMC) or MSC secretome (MSEC) at ANOVA IRM is an experimental option alongside these treatments, not a cure.
Does stem cell therapy cure stress urinary incontinence?
No. Stem cell therapy is not a cure for stress urinary incontinence. BMC or MSEC injected locally around the urethral sphincter is intended to support the function of the remaining sphincter muscle. It is given alongside pelvic floor muscle training and the established operations, never instead of them.
Is urinary incontinence stem cell therapy legal in Germany?
Yes, provided the manufacturer holds the required official authorisations. For people with urinary incontinence, ANOVA IRM produces BMC under a collection (procurement) authorisation (Section 20b AMG) and a manufacturing authorisation under Section 13 AMG, and MSEC under the same collection authorisation and a manufacturing authorisation under Section 20c AMG. These were granted by the Darmstadt Regional Council, today the Hessian State Office for Health and Care (HLfGP), with the involvement of the Paul-Ehrlich-Institut; the HLfGP inspects the facility regularly. Both products are given as an individual treatment attempt (individueller Heilversuch); the legal basis is set out on our regulatory status page.
Is urinary incontinence stem cell therapy safe?
Not without qualification. Every treatment carries risks, including those of tissue collection, sedation and the injection at the urethra, which your doctor explains before treatment. Manufacturing under an official authorisation adds a layer of safety: the competent authority inspects the facility every two years, and every change to the process and every new material must be reported to it. Providers without an authorisation are not subject to this control.
Dr. mult. Stehling and ANOVA IRM have made BMC with the same process since 2012. After a pause from 2017 because of a change in German law, manufacturing resumed in 2019 under an authorisation according to Section 13 AMG; since then, 153 people have been treated with BMC (as of October 2026). To date, no serious adverse event has been caused by the product. No karyotyping is required for BMC, because the cells are not cultured or expanded but applied on the day of collection.
Dr. mult. Stehling and ANOVA IRM have made MSEC with the same process since 2016, under an authorisation according to Section 20c AMG since 2018, and have treated 355 people with it (as of October 2026). To date, no serious adverse event has been caused by the product. This experience is well above the roughly 10 to 100 patients of a phase 1/2 study, the step in which clinical research first examines safety; ANOVA IRM has not conducted such a study. No karyotyping is required for MSEC, because MSEC is cell-free and therefore cannot contain cancer cells. Ask every provider for its authorisations; what regulators warn about is summarised under unproven therapies.
What medication is used for urinary incontinence?
For stress urinary incontinence in women, duloxetine is the only medication authorised in the EU; vaginal oestrogen can help after the menopause.[15],[9] Urge incontinence is treated with antimuscarinic drugs, mirabegron or, if these do not help, botulinum toxin injected into the bladder.[9] Bone marrow concentrate (BMC) or mesenchymal stem cell secretome (MSEC) at ANOVA IRM is added to this treatment and does not replace it.
Who qualifies, what the process actually involves, and what it costs — step by step.
You are hereUrinary Incontinence Treatment: Eligibility, Process & Cost
In this section you will find everything about treatment for urinary incontinence (UI) at ANOVA IRM: who is eligible, the process step by step and the cost.
What does the urinary incontinence treatment timeline look like?
- 01
Initial evaluation
Remote, by phone or video — typically 2 weeks to a few months
- 02
Preliminary screening
In your home country, to avoid an unnecessary journey
- 03
First visit — blood tests and collection
Two-day outpatient visit. Day 1: consultation, informed consent and blood tests; if you wish, an MRI of the pelvic floor or the sphincter. Day 2 with BMC: bone marrow collection under brief sedation; BMC is concentrated, tested and injected around the urethral sphincter the same day (about 2–4 hours). Day 2 with MSEC: mini-liposuction under brief sedation, if the results are normal
- 04
Production and quality control (MSEC)
Approximately 4 weeks; yields 10 doses
- 05
Storage (MSEC)
Up to 2 years, for the applications of your plan
- 06
Application schedule and follow-up
Set individually: BMC once, on day 2; MSEC starting with two doses, or optionally three, then one dose every 4–6 weeks or a double dose every 3 months, depending on where you live. Progress is reviewed by phone or video
Who qualifies for urinary incontinence treatment, and what are the requirements?
We consider adults with urinary incontinence after a full diagnostic work-up, mainly women and men with stress urinary incontinence or mixed incontinence. After surgery for prostate cancer, the operation must have taken place at least two years ago, and your latest PSA results must show no sign of the cancer returning. You need to be well enough for the bone marrow collection (BMC) or the mini-liposuction (MSEC) under brief sedation and able to travel to Offenbach. Every treatment recommendation follows a full clinical evaluation in which the treating physician weighs benefit and risk. Applying for an evaluation does not mean that treatment will be offered.
What are the contraindications for urinary incontinence treatment?
Our treatments are experimental. We treat only people for whom, after medical assessment, we consider the benefit-risk balance to support treatment.
Applies to all ANOVA treatments:
- Active cancer within the last two years
- Under the age of legal majority
- Pregnancy or breastfeeding
- Active infectious disease (hepatitis A, B, C, HIV, syphilis or other)
Specific to urinary incontinence:
- Surgery for prostate cancer less than two years ago, or any sign of the cancer returning
- Advanced prolapse of the pelvic organs that should first be treated by an operation
- Unable to breathe unaided, or difficulty breathing in the supine position (sedation for tissue collection)
- Psychiatric disorder that would prevent informed consent or cooperation
A blood clotting disorder or blood-thinning medication is not a contraindication in itself. Whether it needs to be paused for the tissue collection and the injection is decided with your treating doctors; please never stop it on your own.
What does urinary incontinence therapy at ANOVA IRM involve, step by step?
What screening is needed before you travel for urinary incontinence treatment?
A preliminary screening in your home country helps you avoid an unnecessary journey — for BMC as well as for MSEC. It usually consists of a blood test for HIV, hepatitis A, B or C, syphilis and other active infections, and a urine test. In men after prostate cancer surgery, your latest PSA result and your urologist's follow-up report also show early whether medical factors would rule out treatment.
What happens at your visit to Offenbach for urinary incontinence?
Your first visit to Offenbach takes two days and is outpatient, for BMC and MSEC alike. On the first day, your doctor explains the treatment and obtains your consent; blood tests are carried out at ANOVA IRM as German medical rules require. If you wish, an MRI of the pelvic floor or the sphincter can be done the same day. With BMC, bone marrow is collected from the pelvic bone under brief sedation on the second day. BMC is concentrated, tested and injected around the urethral sphincter the same day, which takes about two to four hours. With MSEC, a small amount of abdominal fat is collected on the second day by mini-liposuction under brief sedation, if the results are normal. The first MSEC application usually follows four to six weeks later.
How are your BMC and MSEC for urinary incontinence produced and quality-controlled?
BMC: Your BMC is produced on the day of collection in our own facility in Offenbach, under a manufacturing authorisation (Section 13 AMG) and good manufacturing practice (GMP). The most important quality tests are completed before the injection; the remaining tests follow afterwards.
MSEC: Mesenchymal stromal cells are isolated from the collected fat tissue and expanded under controlled conditions in our own facility. This takes place under official authorisation and officially inspected good professional practice (GFP, gute fachliche Praxis; similar to Good Tissue Practice, GTP, in the US, but more than GTP). These cells are then used to produce your MSEC preparation — the signalling molecules they release, not the living cells. Production and quality control take approximately four weeks and yield 10 doses per production cycle. The complete quality control is finished before the first application, and the released secretome is stored at −80 °C for up to two years.
How often are BMC and MSEC applied in urinary incontinence?
Stress urinary incontinence is often a lasting condition. BMC is applied once, during the two-day visit. With MSEC we plan several sessions rather than a single application; see the timeline above.
The schedule is set individually for each patient, for example:
- BMC: one application on day two of the visit.
- MSEC: two doses at the start, or optionally a boost of three doses.
- If you live close by: then one MSEC dose every 4 to 6 weeks.
- If you live further away: then a double dose of MSEC every 3 months.
- Shelf life: all 10 MSEC doses of a production cycle are used within two years.
- Standard route for urinary incontinence: injection locally around the urethral sphincter (periurethral), in women and in men. It is given by an ANOVA IRM physician, a urologist, where needed with ultrasound guidance. This is intended to bring BMC or MSEC directly to the muscle that closes the urethra.
- Sedation: the injection is given under sedation by the ANOVA IRM anaesthetist.
- No intravenous alternative: BMC and MSEC are applied only locally, never into a vein.
Injections at the urethral sphincter are established urological procedures when performed by experienced physicians; your doctors discuss the procedure and its risks with you beforehand.
What does urinary incontinence treatment with BMC or MSEC cost?
BMC treatment for urinary incontinence costs approximately €8,000 to €9,000. MSEC treatment costs approximately €20,000–€36,000, depending on the number of doses (three to ten), and requires a two-day visit for tissue collection, followed by further visits. Both are billed according to the German Medical Fee Schedule (GOÄ). For MSEC, the base package — the mini-liposuction and the first three MSEC doses — costs approximately €20,000; each further dose costs approximately €2,250. Additional examinations, such as an MRI of the pelvic floor or the sphincter, and your sedation preferences also affect the total. You receive an individual written estimate before any treatment decision.
With MSEC, a double liposuction can be recommended for a lasting condition: it yields 20 doses from a single collection, which can be used over the current shelf life of two years. The cost is correspondingly higher and is shown in your individual estimate.
Our blog post on treatment cost explains what drives the cost of stem cell treatment in general. Travel, accommodation and other personal expenses, including those of an accompanying person, are not included. Treatment for urinary incontinence with BMC or MSEC is generally self-funded; you can still ask your insurer about possible reimbursement. All prices are subject to change.
Why does the cost of urinary incontinence treatment vary?
All treatments at ANOVA IRM are billed according to the German Medical Fee Schedule (Gebührenordnung für Ärzte, GOÄ). For urinary incontinence we administer BMC and MSEC locally around the urethral sphincter, because in our assessment they are most likely to act there: the sphincter is the muscle that closes the urethra. Within the ranges, the cost varies mainly with the product and, for MSEC, with the number of doses. The exact cost of your treatment plan is set out in your individual written cost estimate.
Frequently asked questions — eligibility, process and travel
Which types of urinary incontinence may be considered for stem cell treatment?
How are BMC and MSEC administered for urinary incontinence?
By injection locally around the urethral sphincter (periurethral), given by an ANOVA IRM physician, a urologist, under sedation and, where needed, with ultrasound guidance. BMC is injected on the second day of your stay in Offenbach, on the same day as the bone marrow collection; MSEC is given over several sessions once it has been produced. Both are applied only locally, never into a vein.
Can stem cells help with incontinence after prostate surgery?
This is still being researched; small external studies with fat-derived cells in men after prostate surgery reported less leakage in some of them.[16],[17] At ANOVA IRM, treatment after surgery for prostate cancer is possible at the earliest two years after the operation, and only if your PSA results show no sign of the cancer returning. We assess this together with the findings of your treating urologist.
How long does the whole urinary incontinence process take?
Usually two weeks to a few months from your first enquiry to the start of treatment, depending on how quickly your findings and appointments are available. With BMC, you travel only for the treatment itself, which takes two days in Offenbach. With MSEC, further visits for the applications of your plan follow, usually over about a year. Follow-up takes place by phone or video.
Does health insurance cover urinary incontinence stem cell therapy in Germany?
No. Health insurers do not ordinarily reimburse experimental BMC or MSEC treatment for urinary incontinence, so you should plan to pay privately. Pelvic floor training, continence aids and established operations remain covered as usual; for BMC or MSEC you can ask your insurer directly about an individual decision.
Should I stop my current urinary incontinence medication such as duloxetine, mirabegron or antimuscarinics?
No. The programme complements guideline-based care. Please continue to work with your treating urologist or gynaecologist throughout.
Should I continue my existing urinary incontinence treatment such as pelvic floor muscle training or a pessary?
Yes. Pelvic floor muscle training remains important before and after treatment with BMC or MSEC, and pessaries, continence aids and any medication your doctors prescribe continue as before. Nothing changes unless your treating physician recommends it.
How often do I need to travel to Germany for urinary incontinence stem cell treatment?
With BMC usually once, for two days in Offenbach, less than 20 minutes from Frankfurt Airport: the first day for the consultation and blood tests, the second for the bone marrow collection and the injection. With MSEC, the two-day visit for blood tests and the mini-liposuction is followed by further visits for the applications of your plan. The full sequence is described on our BMC page.
What medical records should I send for a urinary incontinence assessment?
Please send us your most recent documents; we will ask if we need anything else. Helpful are, for example, a bladder diary over three days, the results of a pad test or urodynamics, and reports on earlier operations. For men after prostate surgery, the operation report, the tissue findings and your PSA results since the operation help. A current medication list and any MRI or ultrasound findings are useful too.
Does ANOVA IRM treat international patients with urinary incontinence?
Yes. Women and men with urinary incontinence from other countries can start from home: we advise in English and carry out the first assessment by phone or video.
How continence works and fails, the standard of care, the rationale for BMC and MSEC and all references.
You are hereUrinary Incontinence: Clinical & Scientific Evidence
What happens in urinary incontinence (UI)?
Urinary incontinence is defined as any involuntary leakage of urine. Continence depends on two things: a bladder that stores urine at low pressure, and a urethra that stays closed when the pressure in the abdomen rises. The urethra is closed by the striated urethral sphincter (rhabdosphincter), smooth muscle, the soft lining of the urethra and the support of the pelvic floor.
In women, stress urinary incontinence (SUI) arises from too much mobility of the urethra when its support is weakened (urethral hypermobility), from a weak sphincter itself (intrinsic sphincter deficiency) or from both. In men, radical prostatectomy removes the prostate and the inner sphincter at the bladder neck, so continence then depends on the external sphincter alone. A shorter membranous urethra, the segment below the prostate that contains this sphincter, is linked with poorer recovery of continence after the operation.[7]
In a Norwegian survey of almost 28,000 women, 25% reported urinary incontinence; half of them had stress urinary incontinence, 36% mixed incontinence and 11% urge incontinence.[2] Severity is measured with the bladder diary, the pad test and questionnaires such as the ICIQ-UI Short Form.[9]
What causes urinary incontinence, and what are the risk factors?
Stress urinary incontinence usually has several contributing causes. What causes the leakage and what keeps it going are two different questions; the next section deals with the second.
- Pregnancy and vaginal birth: the effect of childbirth is strongest for stress urinary incontinence and in younger women.[3],[4]
- Overweight: a strong and independent risk factor; weight loss can reduce leakage.[5]
- Menopause and age: the tissue of the urethra and pelvic floor changes, and leakage becomes more common with age.[1]
- Prostate surgery: radical prostatectomy for cancer is the most common cause in men; incontinence after operations for a benign enlarged prostate, such as TURP, is less common.[6],[10]
- Radiotherapy of the pelvis: can damage the sphincter and its blood supply.[10]
- Neurological diseases: for example multiple sclerosis, stroke or spinal cord injury, which mainly cause urge incontinence or emptying problems.
- Other factors: chronic cough, heavy physical work, constipation and earlier operations in the pelvis.
What drives the progression of stress urinary incontinence?
Once the cause has acted, the course depends on how much sphincter function remains. During vaginal birth, the sphincter, its nerve supply and the supporting tissue can be stretched and injured. With age and after the menopause, the urethral tissue changes and the sphincter can weaken further.[1] After radical prostatectomy, continence often improves over the first year; leakage that persists beyond it seldom resolves on its own and is then treated surgically.[10] After radiotherapy, reduced blood supply and scarring of the tissue can be added.
This is where our programme aims — at the function of the remaining sphincter muscle and its surroundings, not at the original cause, and not at a cure.
What is the guideline-based standard of care for urinary incontinence?
For women, the European Association of Urology (EAU) guideline describes a stepwise approach.[9] Weight loss, treatment of constipation and supervised pelvic floor muscle training for at least three months come first. In a Cochrane review, women with stress urinary incontinence who did pelvic floor muscle training were about eight times more likely to report cure than women without training.[11] Vaginal pessaries and other devices can help during physical activity. Duloxetine is authorised in the EU for moderate to severe stress urinary incontinence in women, but side effects such as nausea often lead to stopping it.[15],[9]
If these measures are not enough, an operation is offered. With a mid-urethral sling, 62 to 98% of women reported cure in the first year, depending on the technique.[12] Alternatives are colposuspension and a sling made from the patient's own tissue (autologous fascial sling). Bulking agents injected into the urethral wall are less invasive, but the evidence for them is limited and repeat injections are often needed.[13]
For men after prostate surgery, pelvic floor muscle training is offered first, and continence often improves during the first year.[10] For persistent leakage, a male sling is an option in mild to moderate incontinence. The artificial urinary sphincter has been the reference treatment for moderate to severe incontinence for decades.[10],[14] Urge incontinence is treated with bladder training, antimuscarinic drugs or mirabegron, and if necessary with botulinum toxin or sacral neuromodulation.[9]
These treatments can make many people dry, but none of them restores a damaged sphincter muscle. Research into cell-based approaches is exploring this question; whether it is possible has not been shown. BMC and MSEC do not replace standard care.
How is urinary incontinence diagnosed, and what do we not do ourselves?
Urinary incontinence is diagnosed by your urologist or gynaecologist, not by us. The basic assessment includes the history, a bladder diary over three days, a urine test and a physical examination with a cough stress test.[9] Ultrasound measures the urine left in the bladder after voiding (post-void residual). Severity is recorded with a pad test and questionnaires such as the ICIQ-UI Short Form. Before an operation, urodynamic tests measure bladder pressure during filling (cystometry) and the closing pressure of the urethra. A cystoscopy can show narrowing or other changes of the urethra and bladder.
Imaging adds information on the anatomy. Ultrasound of the pelvic floor and dynamic MRI during straining show the movement of the bladder neck and the pelvic organs; European radiology societies have published joint recommendations for this MRI.[8] In men, MRI measures the length of the membranous urethra.[7]
We carry out MRI ourselves: with or without contrast, as dynamic MRI of the pelvic floor and as high-resolution MRI of the urethral sphincter. This takes place at the Institut für Bildgebende Diagnostik in the same building, which also belongs to Dr. Stehling. Where needed, the injection itself is guided by ultrasound by the ANOVA IRM physician who gives it. We do not perform urodynamics, cystoscopy or ultrasound of the pelvic floor, nor the urological or gynaecological diagnosis itself; please bring these findings from your doctors.
What is the scientific rationale for BMC and MSEC in urinary incontinence?
Bone marrow concentrate (BMC)
ANOVA IRM has not yet tested BMC or MSEC for urinary incontinence in a clinical study. BMC is concentrated from the patient’s own bone marrow on the day of collection. It contains haematopoietic and mesenchymal stem cells in their natural composition, together with growth factors and other signalling molecules. External laboratory and animal studies with mesenchymal stromal cells, including cells from bone marrow, reported better closure of an injured urethral sphincter in several animal models.[20]
In humans, mainly other cell products have been tested — cells from muscle or fat, not BMC. In a small external early clinical study in Japan (single-arm, without a control group), 13 men with incontinence after prostate surgery received an injection of their own fat-derived regenerative cells. In 10 of them, leakage fell on average by more than half and remained lower over a follow-up of about five to six years; no serious adverse events were reported.[16] In the external multicentre single-arm clinical trial ADRESU (45 men after prostatectomy), 37% met the study’s criterion for less leakage after one year. No serious adverse event was related to the cells.[17]
An external meta-analysis of 21 studies in 885 women with stress urinary incontinence found a response in almost two thirds after cell injections at the urethra, with mostly minor and temporary side effects.[19] The authors point out that most studies had no control group. The external phase 3 trial CELLEBRATE tested muscle-derived cells in 297 women. After one year, 52% of the treated women and 54% after placebo had at least 50% fewer stress leakage episodes; a benefit over placebo could not yet be demonstrated.[18]
MSC secretome (MSEC)
MSEC is a mesenchymal stromal cell secretome: the growth factors, cytokines (cell-to-cell messengers) and extracellular vesicles released by these cells, without the cells themselves. Mesenchymal stem cells and mesenchymal stromal cells are two names for the same cells (MSC); the International Society for Cell & Gene Therapy recommends “stromal” for cells grown in the laboratory.[22],[23]
In a rat model of stress urinary incontinence, exosomes from human fat-derived stem cells were injected around the urethra. The treated rats had a higher leak point pressure and more striated muscle and nerve fibres in the urethra than untreated rats.[21] We are not aware of a published clinical study of an MSC secretome injected at the sphincter in humans; animal results cannot show whether a treatment helps people.
What is the efficacy hypothesis behind BMC and MSEC in urinary incontinence?
In stress urinary incontinence, the striated sphincter muscle has fewer and weaker fibres, its nerves are damaged and its blood supply is reduced; after operations and radiotherapy, scar tissue can be added. The hypothesis is that the cells and growth factors in BMC, and the soluble factors of the mesenchymal stromal cell secretome, injected locally at the sphincter, influence this environment. In animal models, stem cells and the factors they release may support muscle fibres, nerve fibres and small vessels of the sphincter.[20],[21] Whether stem cells also settle in the tissue and form new muscle is discussed in animal studies; many researchers today assume that the released factors matter more.[20]
One limitation belongs with it: a sphincter that has been largely destroyed is not expected to be rebuilt. Our aim is to improve the function of the remaining sphincter muscle and to reduce leakage, not to cure incontinence.
Talk to us about current changes or additions to the programme. For several conditions ANOVA IRM also offers infusion therapies alongside the components described above.
Where does our own urinary incontinence evidence stand?
We do not currently publish our own outcome data for urinary incontinence. What we can say about BMC and MSEC in urinary incontinence therefore rests on the published literature and on the rationale described above.
Stem cell-based therapy for urinary incontinence remains experimental, and outcomes vary from patient to patient. Treatment goals are agreed individually and followed with a bladder diary, pad tests and questionnaires. Treatment cannot guarantee less leakage.
What is the realistic goal of urinary incontinence treatment?
Care for stress urinary incontinence aims to reduce leakage and its impact on daily life, and many people become dry with established treatment.[9] For BMC and MSEC, the aim is to support the function of the remaining sphincter muscle, not to rebuild a sphincter that has been destroyed.
Legal framework for BMC and MSEC in urinary incontinence
ANOVA IRM manufactures BMC, an advanced therapy medicinal product, under a collection (procurement) authorisation (Section 20b AMG) and a manufacturing authorisation under Section 13 AMG. MSEC, an autologous tissue preparation, is manufactured under the same collection authorisation and a manufacturing authorisation under Section 20c AMG. The authorisations were granted by the Darmstadt Regional Council, today the Hessian State Office for Health and Care (HLfGP), with the involvement of the Paul-Ehrlich-Institut; the HLfGP inspects the facility regularly. For urinary incontinence, both products are given as an individual treatment attempt (individueller Heilversuch), which concerns the administration only and follows informed consent; because they are used only for ANOVA IRM’s own patients, no authorisation under Section 4b(3) or approval under Section 21a AMG is required, as our regulatory status page explains.
Frequently asked questions — urinary incontinence, evidence and approval status
Is stem cell therapy approved for urinary incontinence anywhere?
Are stem cell studies evidence that BMC or MSEC works in stress urinary incontinence?
No. The published studies mainly used other cell products, from muscle or fat, and most had no control group. In the external phase 3 trial CELLEBRATE, a benefit of muscle-derived cells over placebo could not yet be demonstrated.[18] Proof would require a randomised controlled trial with BMC or MSEC itself, and none exists. See the scientific rationale.
What type of stem cell therapy does ANOVA use for urinary incontinence?
As our first choice, bone marrow concentrate (BMC) from your own pelvic bone, concentrated on the same day; it contains your own haematopoietic and mesenchymal stem cells together with growth factors. Alternatively, autologous mesenchymal stem cell secretome (MSEC), the cell-free factors released by mesenchymal stromal cells grown from your own fat tissue. Both are injected locally around the urethral sphincter.
How common is urinary incontinence (UI)?
Very common. In most studies, a quarter to almost half of adult women report some leakage of urine, and it becomes more common with age.[1] In a Norwegian survey of almost 28,000 women, 25% had urinary incontinence; half of them had stress urinary incontinence, 36% mixed and 11% urge incontinence.[2] In men, incontinence is less common and often follows prostate surgery. In the ProtecT trial, urinary leakage was more frequent after radical prostatectomy than after radiotherapy or active monitoring throughout six years.[6]
What are the symptoms of urinary incontinence (UI)?
The main symptom is the involuntary loss of urine. What triggers it and how much is lost differ between people and can change over time.
Stress leakage
- leakage when coughing, laughing, sneezing, lifting, running or jumping
- in men after prostate surgery, often when standing up or walking
Urge and other symptoms
- a sudden, strong urge to pass urine that is difficult to hold back (urgency)
- passing urine often during the day (frequency) and waking at night to pass urine (nocturia)
- dribbling after passing urine, or a feeling that the bladder is not empty
- the need for pads or other continence aids
Which forms of urinary incontinence (UI) are there, and how does it progress?
Urinary incontinence is grouped by the situation in which urine is lost, and its course depends on the cause.[9]
- Stress urinary incontinence (SUI): leakage on physical effort when the sphincter or its support is weak; the most common form in women and after prostate surgery.[2] It often stays stable or slowly increases with age.
- Urge incontinence: leakage with a sudden strong urge, often as part of an overactive bladder.
- Mixed incontinence: stress and urge incontinence together; common in older women.[2]
- Overflow incontinence: dribbling from a bladder that cannot empty, for example because of an obstruction or nerve damage.
- Incontinence after prostate surgery: usually stress incontinence; it often improves during the first year after the operation.[10]
What complications can urinary incontinence (UI) cause?
Urinary incontinence is rarely dangerous, but it can affect skin, health and quality of life considerably.
- Skin problems: irritation and inflammation of the skin from constant moisture (incontinence-associated dermatitis).
- Urinary tract infections: more frequent, especially when the bladder does not empty completely.
- Falls: older people who hurry to the toilet because of urgency fall more often.
- Quality of life: avoiding sport, travel and social contact; effects on sleep, sexuality and mood.
Important Pages
Questions people usually ask next. Each is answered in full on its own page.
- Who are we?
- Is ANOVA legal?
- Is stem cell therapy safe?
- What is MSC secretome (MSEC)?
- What is BMC (Bone Marrow Concentrate)?
- What are stem cells?
- What should I ask when looking for a stem cell treatment?
- Which conditions do we treat?
- Translational medicine — works in progress
- Erectile dysfunction — stem cell treatment programme
Affiliations of ANOVA
ANOVA IRM shares its premises in Offenbach with two further institutions owned by Dr. Stehling: the Institut für Bildgebende Diagnostik (IBDO), providing MRI and CT imaging, and the VITUS PRIVATKLINIK Prof. Dr. Stehling GmbH. Because imaging is carried out in the same building, condition-specific diagnostics — including dynamic MRI of the pelvic floor and high-resolution MRI of the urethral sphincter — can be performed in-house rather than referred elsewhere. See diagnostics at ANOVA IRM.
References — urinary incontinence literature
Literature specific to urinary incontinence is listed here. General literature on bone marrow is maintained on the BMC page, on MSC, secretome and extracellular vesicles on the MSC secretome page.
Urinary incontinence — frequency, causes and course
- [1] Milsom I, Gyhagen M. The prevalence of urinary incontinence. Climacteric. 2019;22(3):217–222. doi:10.1080/13697137.2018.1543263. PMID: 30572737.
- [2] Hannestad YS, Rortveit G, Sandvik H, et al. A community-based epidemiological survey of female urinary incontinence: the Norwegian EPINCONT study. Epidemiology of Incontinence in the County of Nord-Trøndelag. J Clin Epidemiol. 2000;53(11):1150–1157. doi:10.1016/s0895-4356(00)00232-8. PMID: 11106889.
- [3] Rortveit G, Hannestad YS, Daltveit AK, et al. Age- and type-dependent effects of parity on urinary incontinence: the Norwegian EPINCONT study. Obstet Gynecol. 2001;98(6):1004–1010. doi:10.1016/s0029-7844(01)01566-6. PMID: 11755545.
- [4] Lukacz ES, Lawrence JM, Contreras R, et al. Parity, mode of delivery, and pelvic floor disorders. Obstet Gynecol. 2006;107(6):1253–1260. doi:10.1097/01.AOG.0000218096.54169.34. PMID: 16738149.
- [5] Subak LL, Richter HE, Hunskaar S. Obesity and urinary incontinence: epidemiology and clinical research update. J Urol. 2009;182(6 Suppl):S2–S7. doi:10.1016/j.juro.2009.08.071. PMID: 19846133.
- [6] Donovan JL, Hamdy FC, Lane JA, et al. Patient-reported outcomes after monitoring, surgery, or radiotherapy for prostate cancer. N Engl J Med. 2016;375(15):1425–1437. doi:10.1056/NEJMoa1606221. PMID: 27626365.
- [7] Mungovan SF, Sandhu JS, Akin O, et al. Preoperative membranous urethral length measurement and continence recovery following radical prostatectomy: a systematic review and meta-analysis. Eur Urol. 2017;71(3):368–378. doi:10.1016/j.eururo.2016.06.023. PMID: 27394644.
Diagnostics and standard of care
- [8] El Sayed RF, Alt CD, Maccioni F, et al. Magnetic resonance imaging of pelvic floor dysfunction – joint recommendations of the ESUR and ESGAR Pelvic Floor Working Group. Eur Radiol. 2017;27(5):2067–2085. doi:10.1007/s00330-016-4471-7. PMID: 27488850.
- [9] Nambiar AK, Arlandis S, Bø K, et al. European Association of Urology guidelines on the diagnosis and management of female non-neurogenic lower urinary tract symptoms. Part 1: diagnostics, overactive bladder, stress urinary incontinence, and mixed urinary incontinence. Eur Urol. 2022;82(1):49–59. doi:10.1016/j.eururo.2022.01.045. PMID: 35216856.
- [10] Sandhu JS, Breyer B, Comiter C, et al. Incontinence after prostate treatment: AUA/SUFU guideline. J Urol. 2019;202(2):369–378. doi:10.1097/JU.0000000000000314. PMID: 31059663.
- [11] Dumoulin C, Cacciari LP, Hay-Smith EJC. Pelvic floor muscle training versus no treatment, or inactive control treatments, for urinary incontinence in women. Cochrane Database Syst Rev. 2018;(10):CD005654. doi:10.1002/14651858.CD005654.pub4. PMID: 30288727.
- [12] Ford AA, Rogerson L, Cody JD, et al. Mid-urethral sling operations for stress urinary incontinence in women. Cochrane Database Syst Rev. 2017;(7):CD006375. doi:10.1002/14651858.CD006375.pub4. PMID: 28756647.
- [13] Kirchin V, Page T, Keegan PE, et al. Urethral injection therapy for urinary incontinence in women. Cochrane Database Syst Rev. 2017;(7):CD003881. doi:10.1002/14651858.CD003881.pub4. PMID: 28738443.
- [14] Van der Aa F, Drake MJ, Kasyan GR, et al. The artificial urinary sphincter after a quarter of a century: a critical systematic review of its use in male non-neurogenic incontinence. Eur Urol. 2013;63(4):681–689. doi:10.1016/j.eururo.2012.11.034. PMID: 23219375.
- [15] European Medicines Agency. Yentreve (duloxetine): EPAR — medicine overview. Authorised in the EU since 11 August 2004 for women with moderate to severe stress urinary incontinence. Page last updated 9 July 2024. Accessed 21 October 2026. https://www.ema.europa.eu/en/medicines/human/EPAR/yentreve
Cell therapies in urinary incontinence — clinical studies (cells, other products than BMC or MSEC)
- [16] Gotoh M, Yamamoto T, Shimizu S, et al. Treatment of male stress urinary incontinence using autologous adipose-derived regenerative cells: long-term efficacy and safety. Int J Urol. 2019;26(3):400–405. doi:10.1111/iju.13886. PMID: 30557919.
- [17] Gotoh M, Shimizu S, Yamamoto T, et al. Regenerative treatment for male stress urinary incontinence by periurethral injection of adipose-derived regenerative cells: outcome of the ADRESU study. Int J Urol. 2020;27(10):859–865. doi:10.1111/iju.14311. PMID: 32729155.
- [18] Kaufman MR, Goldman HB, Chermansky CJ, et al. Iltamiocel autologous cell therapy for the treatment of female stress urinary incontinence: a double-blind, randomized, stratified, placebo-controlled trial. Neurourol Urodyn. 2024;43(8):2290–2299. doi:10.1002/nau.25588. PMID: 39282854. Phase 3 trial (CELLEBRATE), sponsored by the manufacturer (Cook MyoSite).
- [19] Mohammed Bahutair SN, Fathima S, Tayade KD, et al. Post-treatment response and safety of stem cell-based urethral injection therapy for female stress urinary incontinence: a systematic review and meta-analysis. J Clin Med. 2026;15(19):7737. doi:10.3390/jcm15197737. PMID: 42882197.
Mesenchymal stromal cells, their secretome and nomenclature — laboratory and animal studies
- [20] Klein G, Hart ML, Brinchmann JE, et al. Mesenchymal stromal cells for sphincter regeneration. Adv Drug Deliv Rev. 2015;82–83:123–136. doi:10.1016/j.addr.2014.10.026. PMID: 25451135.
- [21] Ni J, Li H, Zhou Y, et al. Therapeutic potential of human adipose-derived stem cell exosomes in stress urinary incontinence – an in vitro and in vivo study. Cell Physiol Biochem. 2018;48(4):1710–1722. doi:10.1159/000492298. PMID: 30077997.
- [22] Dominici M, Le Blanc K, Mueller I, et al. Minimal criteria for defining multipotent mesenchymal stromal cells. The International Society for Cellular Therapy position statement. Cytotherapy. 2006;8(4):315–317. doi:10.1080/14653240600855905. PMID: 16923606.
- [23] Viswanathan S, Shi Y, Galipeau J, et al. Mesenchymal stem versus stromal cells: International Society for Cell & Gene Therapy (ISCT®) Mesenchymal Stromal Cell committee position statement on nomenclature. Cytotherapy. 2019;21(10):1019–1024. doi:10.1016/j.jcyt.2019.08.002. PMID: 31526643.
Approval status
- [24] U.S. Food and Drug Administration. Approved Cellular and Gene Therapy Products. Content current as of 17 September 2026. Accessed 21 October 2026. https://www.fda.gov/vaccines-blood-biologics/cellular-gene-therapy-products/approved-cellular-and-gene-therapy-products
Patient Services at ANOVA Institute for Regenerative Medicine
- Located in the center of Germany, quick access by car or train from anywhere in Europe
- Simple access worldwide, less than 20 minutes from Frankfurt Airport
- Individualized therapy with state-of-the-art autologous stem cell products
- Individually planned diagnostic work-up which include world-class MRI and CT scans
- German high quality standard on safety and quality assurance
- Personal service with friendly, dedicated Patient Care Managers
- Continuous analysis of scientific data in the field of regenerative medicine