

Stem Cell Therapy for Joint and Back Pain
The ANOVA OA Stem Cell Treatment Programme Germany
An individualised treatment programme with autologous bone marrow concentrate (BMC) for adults with osteoarthritis (OA) of the knee, hip, shoulder, elbow, hand and ankle. BMC is injected into the affected joint (intra-articular). Offenbach, Germany. Experimental — fully legal — manufactured under German regulatory authorisation and official inspection since 2018.
Osteoarthritis is the most common joint disease and a leading cause of joint pain in older adults.[1] Beyond relieving symptoms, BMC is intended to reduce the inflammation in the joint and with it the pain, and to slow the progression of the disease. The aim is to postpone a joint replacement or to need fewer painkillers. The programme is offered alongside — never instead of — established treatment such as exercise and physiotherapy.
| Component | Detail |
|---|---|
| Two products | Bone Marrow Concentrate (BMC) and Mesenchymal Stem Cell Secretome (MSEC), each manufactured under official authorisation; no marketing authorisation (experimental) |
| Authorisations | BMC § 20b / § 13 AMG · MSEC § 20b / § 20c AMG (German Medicines Act) |
| Location | Offenbach am Main, Germany |

Osteoarthritis in brief, the joints we treat and the programme — the essentials at a glance.
You are hereIntroduction & Summary
What is osteoarthritis (OA), in brief?
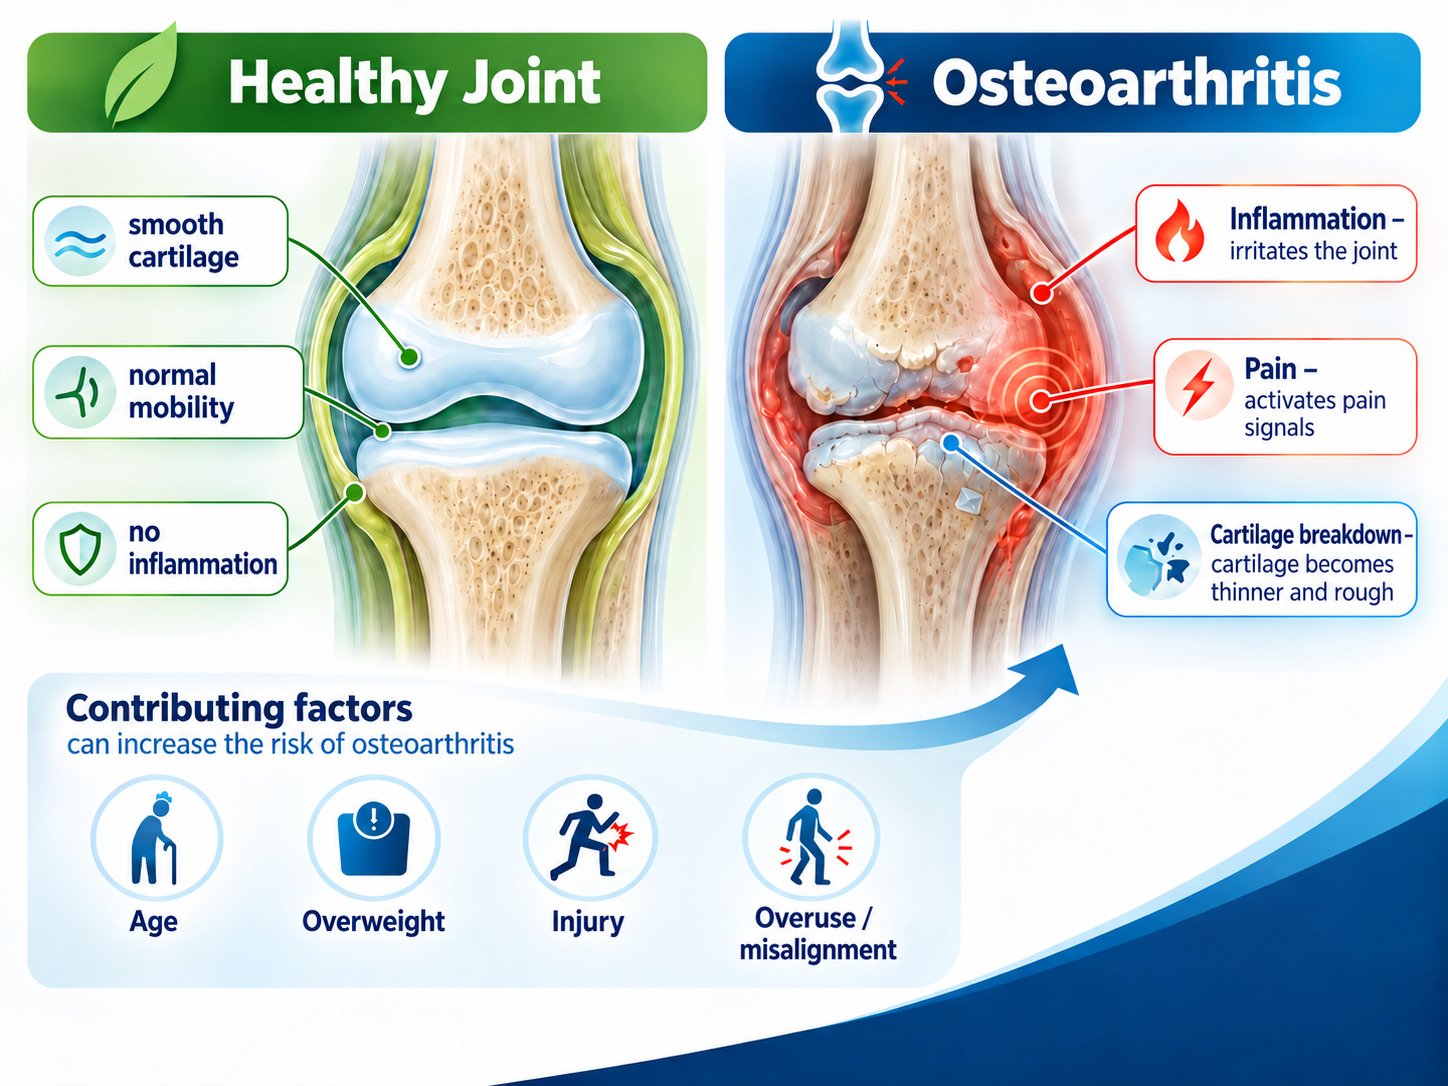
Osteoarthritis (OA), also called arthrosis or degenerative joint disease, is a disease of the whole joint. It affects the cartilage, the bone beneath it, the joint lining (synovium), the ligaments and the muscles around the joint. The cartilage gradually loses its smooth surface, and the joint becomes painful, stiff and less mobile. Osteoarthritis affected about 595 million people worldwide in 2020, and most people over 65 show signs of it on imaging.[1],[2]
Osteoarthritis is not the same as rheumatoid arthritis. Osteoarthritis starts with wear of the cartilage, and inflammation follows the damage. In rheumatoid arthritis (RA), the immune system attacks the joint lining first. Back and neck pain from the discs, vertebrae and facet joints is covered on our spine page.
Typical symptoms are:
- Pain on starting to move and under load, later also at rest
- Stiffness after rest, usually brief
- Swelling and warmth when the joint is inflamed
- Reduced mobility and, later, misalignment of the joint
Primary osteoarthritis develops without a recognisable cause, mainly with age; secondary osteoarthritis follows injuries, misalignment or inflammation. Doctors grade the severity on X-ray with the Kellgren–Lawrence scale. Age, excess weight and genes increase the risk.[3],[4] More details can be found below in our scientific section on osteoarthritis.
What is the ANOVA OA programme?
ANOVA offers autologous bone marrow concentrate (BMC) for osteoarthritis. The programme has two components: a diagnostic MRI and BMC injected into the affected joint (intra-articular). Each component is selected individually; the programme is not a fixed package.
A BMC treatment is intended to have two effects that build on one another. By modulating the underlying immune reaction, BMC is intended to reduce inflammation in the joint, which is often the main cause of pain. When the inflammation subsides, the joint can enter a resting phase in which the cartilage is less exposed to further damage. Further aims are to slow the progression of osteoarthritis and to postpone a joint replacement or to need fewer painkillers.
ANOVA IRM has not yet tested BMC for osteoarthritis in a clinical study. The current state of research is described in the clinical and scientific section below.
The ANOVA OA Programme — Components
Diagnostic MRI
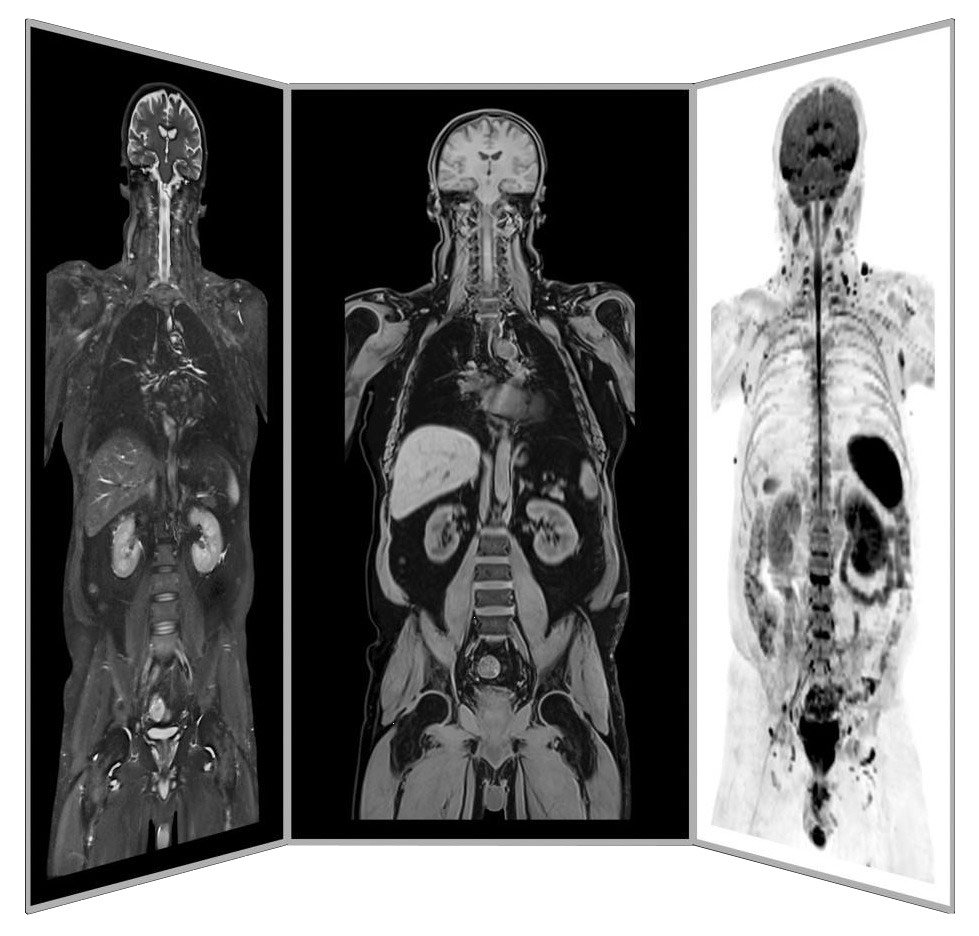
For osteoarthritis treated with BMC, an MRI is not a requirement, but it often helps. It shows the cartilage, the bone beneath it and the joint lining; with a non-radioactive contrast agent, it can also make active inflammation visible. From this we see how far the osteoarthritis has progressed and at which site of the joint BMC should be injected.
Bone marrow concentrate (BMC)
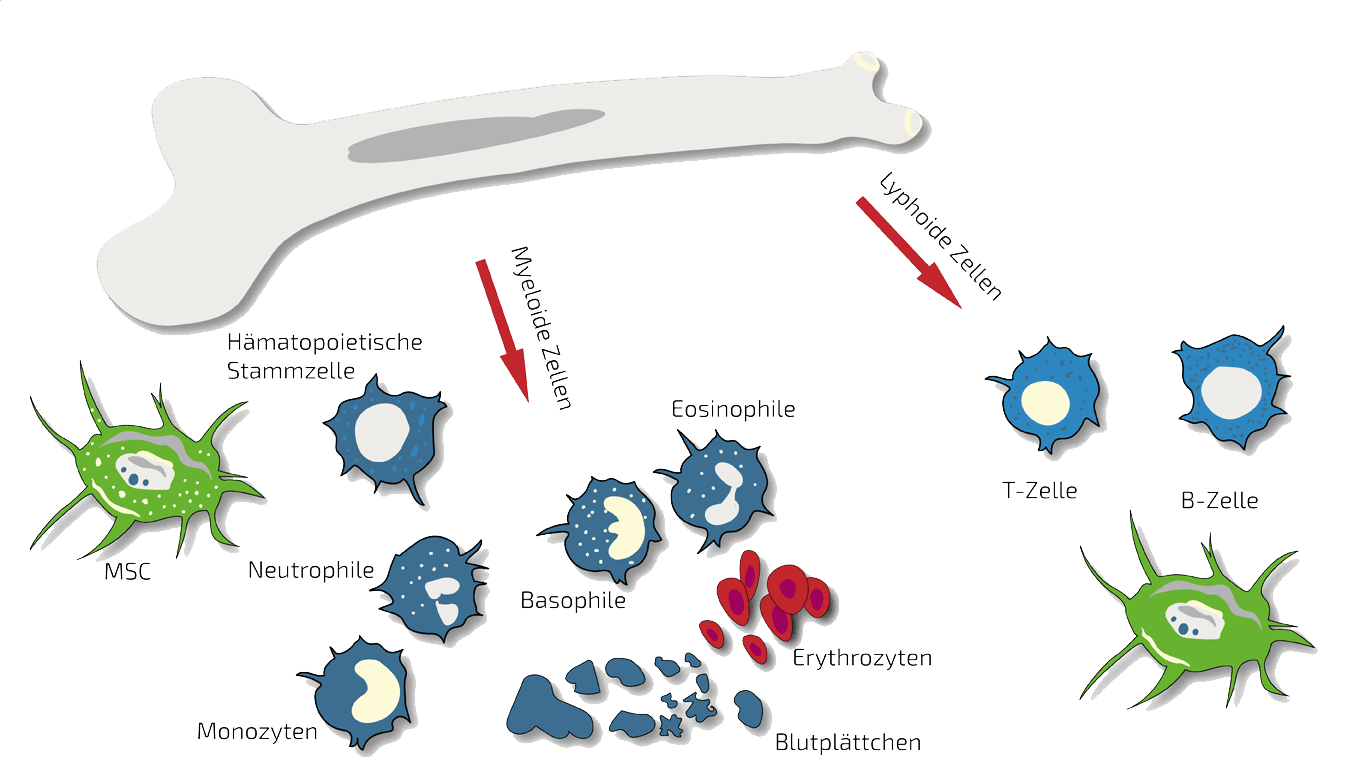
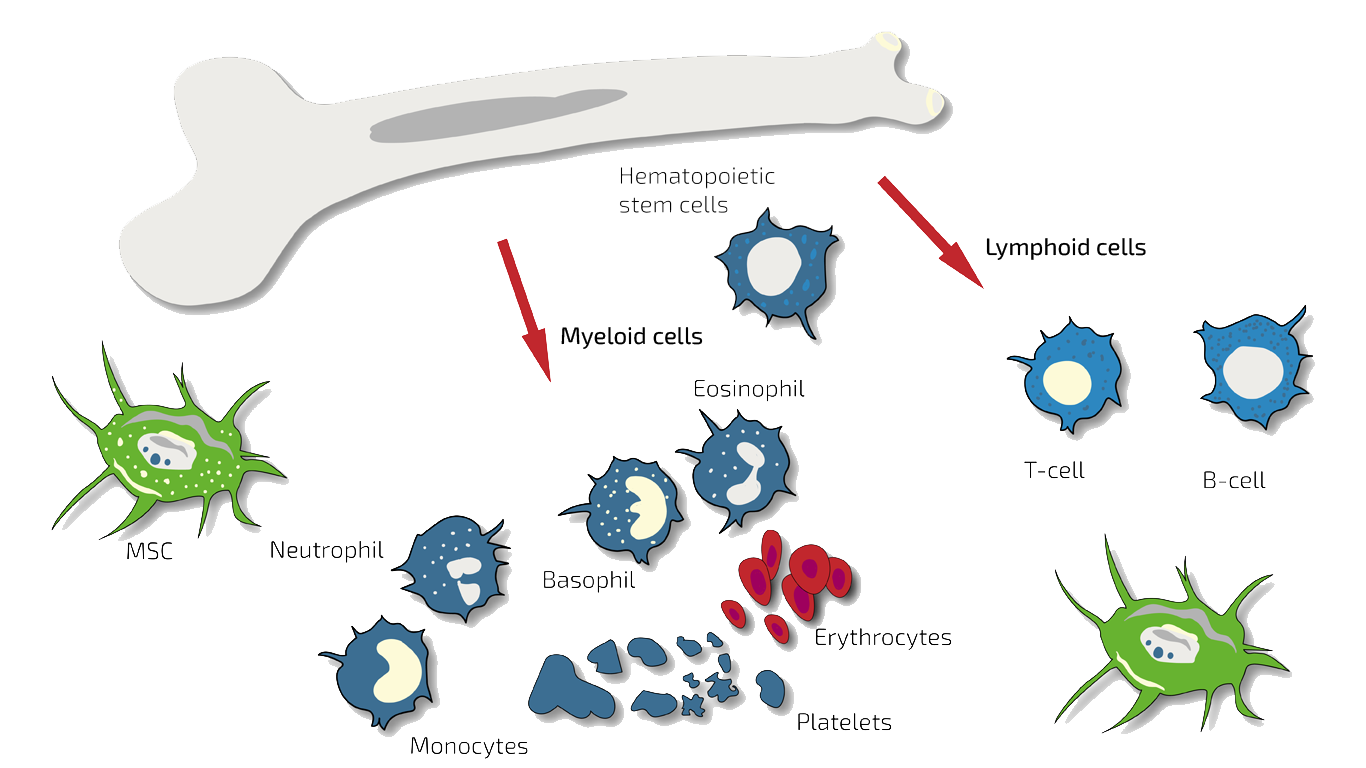
BMC is made from your own bone marrow and contains adult stem cells, haematopoietic and mesenchymal, in their natural composition, together with growth factors. It is collected from the pelvic bone (iliac crest) under brief sedation, concentrated, tested and injected on the same day, during a two-day visit. The cells are not multiplied in the laboratory, so a repeat treatment requires a new collection.
Small external studies reported less pain and better function after BMC in knees with osteoarthritis, and a recent review calls for larger controlled studies.[5],[6],[7] In two small external placebo-controlled studies, a benefit over saline could not yet be demonstrated.[8],[9]
Which joints with OA do we treat?
We treat osteoarthritis of the following joints with BMC, after a diagnostic work-up:
- Knee osteoarthritis (gonarthrosis)
- Hip osteoarthritis (coxarthrosis)
- Shoulder osteoarthritis (omarthrosis)
- Elbow osteoarthritis
- Osteoarthritis of the finger joints and of the base of the thumb (rhizarthrosis)
- Ankle and foot osteoarthritis
- Osteoarthritis of several joints (polyarthrosis); several joints can be treated during one visit
Injuries of the meniscus, ligaments, tendons and cartilage are covered on our joints and sport injuries page; osteoarthritis of the small joints of the spine is covered on our spine page.
Which diagnostics do we use for OA at ANOVA IRM?
We look for the cause of your pain. We work with the Prof. Dr. Stehling Institut für Bildgebende Diagnostik GmbH, which, like ANOVA IRM, belongs to Dr. Stehling and is located in the same building. There we use precision diagnostics such as MRI with non-radioactive contrast agents, which show the cartilage, the bone beneath it and active inflammation in the joint. This tells us how you should be treated and where BMC should be applied.
Which tests are used to diagnose OA?
Diagnosis starts with your medical history and a physical examination of the joint. X-ray shows the narrowing of the joint space and bony outgrowths (osteophytes); MRI also shows the cartilage, the bone marrow beneath it and the joint lining. Blood tests prepare the treatment and help to distinguish osteoarthritis from inflammatory joint diseases.
Research is investigating whether sex hormones influence osteoarthritis and the durability of joint replacements.[10],[11] If you additionally wish, we analyse hormone levels and immune factors in your blood; we do not offer hormone or immune therapy.
What do we review before OA treatment at ANOVA IRM?
Before any treatment decision we review how far the osteoarthritis has progressed, whether inflammation drives your pain and how many joints are affected. We also check whether you are fit for the brief sedation needed for the bone marrow collection.
With BMC:
- Standard: no MRI required.
- Optional, often useful: an MRI with contrast to show inflammation and the state of the cartilage.
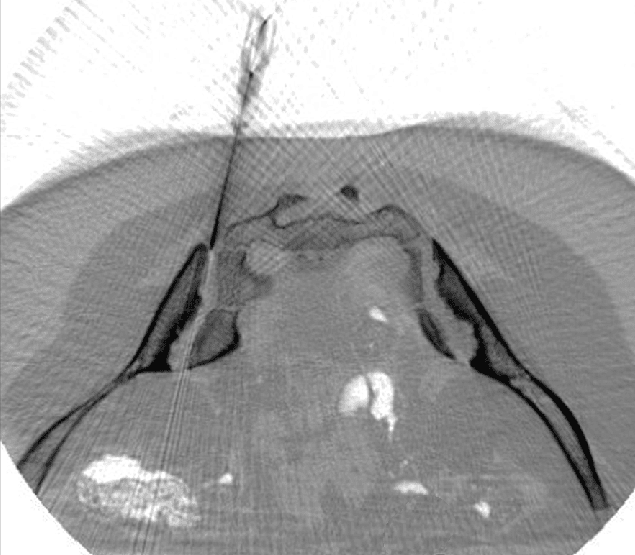
- Image-guided application: CT sometimes in the hip and shoulder, usually not in the knee.
Your own doctors at home can carry out these examinations; please send us the results. They can also be done in-house, where an MRI is often possible on the day of your appointment in Offenbach. If you would like existing findings assessed independently, we offer a second opinion. The full diagnostic pathway is described on our diagnostics page.
Why ANOVA IRM for OA?
Our approach starts with diagnostics. Imaging is led by radiologists, and BMC is placed with imaging support where needed, for example CT in the hip, into the joint at the site of inflammation. An anaesthesiologist looks after you during the bone marrow collection, with the aim of keeping it as pain-free as possible. ANOVA IRM has manufactured BMC in its own facility in Offenbach since 2018; why no marketing authorisation is needed is explained on our regulatory status page. We advise international patients in English.
What can you expect as a patient with OA?
First we ask for the information we need, such as X-ray, MRI or CT images, and explain how to send large image files. A counselling appointment with one of our physicians follows, by phone or video if you live abroad; our patient care team does not charge for this. For the treatment itself you come to Offenbach am Main, less than 20 minutes from Frankfurt Airport. Before you decide, you receive an individual written cost estimate.
Quick answers
Is there a cure for osteoarthritis (OA)?
No. Worn cartilage cannot yet be restored, so treatment aims to relieve pain, keep the joint mobile and slow progression. Exercise, weight reduction, physiotherapy, pain medication and injections come first; in advanced stages, a joint replacement is an option. BMC at ANOVA IRM is intended to calm inflammation in the joint and to slow the course of the disease.
Does stem cell therapy cure osteoarthritis?
No. Stem cell therapy is not a cure for osteoarthritis. BMC is intended to reduce inflammation in the arthritic joint, ease the pain and slow further wear, in addition to exercise and standard treatment.
Is OA stem cell therapy legal in Germany?
Yes, provided the manufacturer holds the official authorisations. For osteoarthritis, ANOVA IRM produces BMC under Section 20b AMG (procurement) and Section 13 AMG (manufacturing) and gives it as an individual treatment attempt; see our regulatory status page.
Is OA stem cell therapy safe?
Not without qualification. An injection into the joint and the bone marrow collection carry risks, which your doctor explains in advance. As BMC comes from your own bone marrow, no donor material is used. Safety depends above all on product quality: following the medicines authorities, products made under authorisation and official inspection are to be regarded as safer than those from unregulated providers. Ask every provider for its authorisations; see also unproven therapies.
What medication is used for osteoarthritis?
Non-steroidal anti-inflammatory drugs (NSAIDs) such as ibuprofen or diclofenac, as gel or tablets, are the most common medication for osteoarthritis; paracetamol and injections of cortisone or hyaluronic acid into the joint are also used. BMC is given in addition to these medicines and does not replace them.
Who qualifies, what the process actually involves, and what it costs — step by step.
You are hereOsteoarthritis (OA) Treatment: Eligibility, Process & Cost
BMC treatment for osteoarthritis at ANOVA IRM costs approximately €8,000–€9,000 and requires one two-day outpatient visit to Offenbach, Germany, for adults with symptomatic osteoarthritis in whom the diagnostic work-up points to inflammation in the joint.
What does the OA treatment timeline look like?
- 01
Remote assessment
Review of your medical history, current treatment and images by email, phone or video; usually two weeks to a few months, depending on available appointments.
- 02
Screening at home
Blood test and existing images before you travel, to avoid an unnecessary journey.
- 03
Day 1 in Offenbach
Consultation and consent, blood tests and, if you wish, an MRI with contrast; planning of the injection.
- 04
Day 2 in Offenbach
Bone marrow collection under brief sedation; BMC is concentrated, tested and injected into the joint the same day (about two to four hours).
- 05
Follow-up
Advice on exercise and rehabilitation; review of your progress by phone or video; a repeat treatment is possible after assessment.
Who qualifies for OA treatment, and what are the requirements?
BMC may be considered for adults with confirmed, symptomatic osteoarthritis and persistent pain or limitation despite standard treatment, after a full diagnostic work-up. Most suitable are patients whose imaging shows a joint that can be treated directly, and whose osteoarthritis is limited to one or a few joints. Requirements are fitness for the brief sedation used for the bone marrow collection and a visit to Offenbach. We ask you to continue your exercise programme and to have realistic expectations of the treatment.
What are the contraindications for OA treatment?
Our treatments are experimental. We treat only people for whom, after medical assessment, we consider the benefit-risk balance to support treatment.
Applies to all ANOVA treatments:
- Active cancer within the last two years
- Under the age of legal majority
- Pregnancy or breastfeeding
- Active infectious disease (hepatitis A, B, C, HIV, syphilis or other)
Specific to osteoarthritis:
- Infection of the joint or of the skin at the injection site
- Unable to breathe unaided, or difficulty breathing in the supine position (sedation for the bone marrow collection)
- Psychiatric disorder that would prevent informed consent or cooperation
A blood clotting disorder or blood-thinning medication is not a contraindication, but please tell us about it before your visit.
What does OA therapy at ANOVA IRM involve, step by step?
Treatment for osteoarthritis follows fixed phases. We begin with your medical history, your previous treatments and a first consultation on whether BMC may help you. Diagnostics, a discussion of all treatment options and a written plan with cost estimate follow. Finally, bone marrow is collected, BMC is prepared and tested, and it is injected into the joint.
What screening is needed before you travel for OA treatment?
A short screening in your home country helps you avoid a journey that would not lead to treatment. It usually consists of a blood test for infections and other reasons against treatment, plus your recent images and doctors’ letters.
What happens at your visit to Offenbach for OA?
You spend two consecutive days in Offenbach as an outpatient. On day one, your doctor explains the treatment, obtains your consent and takes blood; an MRI can be added if you wish. On day two, bone marrow is taken from the pelvic bone under brief sedation, and BMC is injected into the arthritic joint a few hours later.
How is your BMC produced and quality-controlled?
BMC is prepared on the day of collection in our own facility in Offenbach, under a manufacturing authorisation (Section 13 AMG) and good manufacturing practice (GMP). The bone marrow is concentrated but not multiplied in the laboratory. Key quality tests are completed before the injection; further tests follow afterwards.
How is BMC applied in OA?
BMC for osteoarthritis is given during one visit of two days, as with all BMC treatments. Osteoarthritis is a chronic disease; BMC is intended to modify its course (disease-modifying), not to cure it. The treatment may therefore need to be repeated. The schedule is set individually for each patient, for example:
- BMC: one application on the second day of the visit; a repeat after assessment requires a new bone marrow collection.
- Polyarthrosis: several arthritic joints can be injected during the same visit, usually with a double BMC.
- Route: into the arthritic joint (intra-articular), so that BMC reaches the inflamed joint lining and the cartilage directly.
- Image guidance: CT sometimes in the hip and shoulder, usually not needed in the knee.
- BMC is given only into the joint, never into a vein.
What does OA treatment with BMC cost?
BMC treatment for osteoarthritis costs approximately €8,000 to €9,000 and is billed according to the German Medical Fee Schedule (GOÄ). Where CT guides the injection, the cost is closer to €9,000, otherwise closer to €8,000; CT is sometimes used in the hip and shoulder, rarely in the knee. An MRI before treatment and your wishes regarding sedation also affect the total. Treating several joints in one visit usually requires a double BMC, which costs correspondingly more. Before any decision you receive an individual written estimate. Our blog post on treatment cost explains what drives the cost of stem cell treatment in general. Travel and accommodation are not included. All prices are subject to change.
How does the cost of OA treatment vary with the application route?
All treatments at ANOVA IRM are billed according to the German Medical Fee Schedule (Gebührenordnung für Ärzte, GOÄ). For osteoarthritis, the application route is always an injection into the joint; the cost depends mainly on whether CT guidance is needed, on the number of joints and on any MRI beforehand. Your written cost estimate shows the exact amount.
Frequently asked questions — eligibility, process and travel
How is BMC administered for osteoarthritis?
BMC is injected into the arthritic joint (intra-articular), guided by CT where needed. One of our physicians gives the injection on the second day in Offenbach, a few hours after the bone marrow has been collected.
How long does the whole OA process take?
From the first contact to treatment it usually takes about two weeks to a few months, depending on appointments; this part needs no travel. The treatment itself takes two consecutive days in Offenbach.
Does health insurance cover OA stem cell therapy in Germany?
No. Health insurers usually do not reimburse BMC for osteoarthritis because it is an experimental treatment, so patients pay for it themselves. You may still ask your insurer for an individual decision.
Should I stop my current osteoarthritis medication such as ibuprofen or diclofenac?
No. Please continue your medication as agreed with your treating doctor.
Should I continue my existing OA treatment such as exercise and physiotherapy?
Yes. Exercise, physiotherapy and weight management remain the basis of osteoarthritis treatment; BMC does not replace them or your medication. We advise against repeated cortisone injections into the joint. We are glad to coordinate with your family doctor or orthopaedic surgeon.
How often do I need to travel to Germany for osteoarthritis stem cell treatment?
Usually once, for two consecutive days in Offenbach, less than 20 minutes from Frankfurt Airport: bone marrow collection and injection into the joint take place during this visit. A repeat treatment means another visit. The full sequence is explained on our BMC page.
What medical records should I send for an osteoarthritis assessment?
Please send us your most recent documents; we will ask if we need anything else. Helpful are, for example, X-ray or MRI images of the affected joints, reports from your orthopaedic surgeon and a list of your current medication. We will explain how to transfer large image files.
Does ANOVA IRM treat international patients with osteoarthritis?
Yes. Patients from abroad with osteoarthritis are advised in English, and the first assessment is done by email, phone or video.
How osteoarthritis develops, the standard of care, the rationale for BMC and all references.
You are hereOsteoarthritis (OA): Clinical & Scientific Evidence
1. What happens in osteoarthritis (OA)?
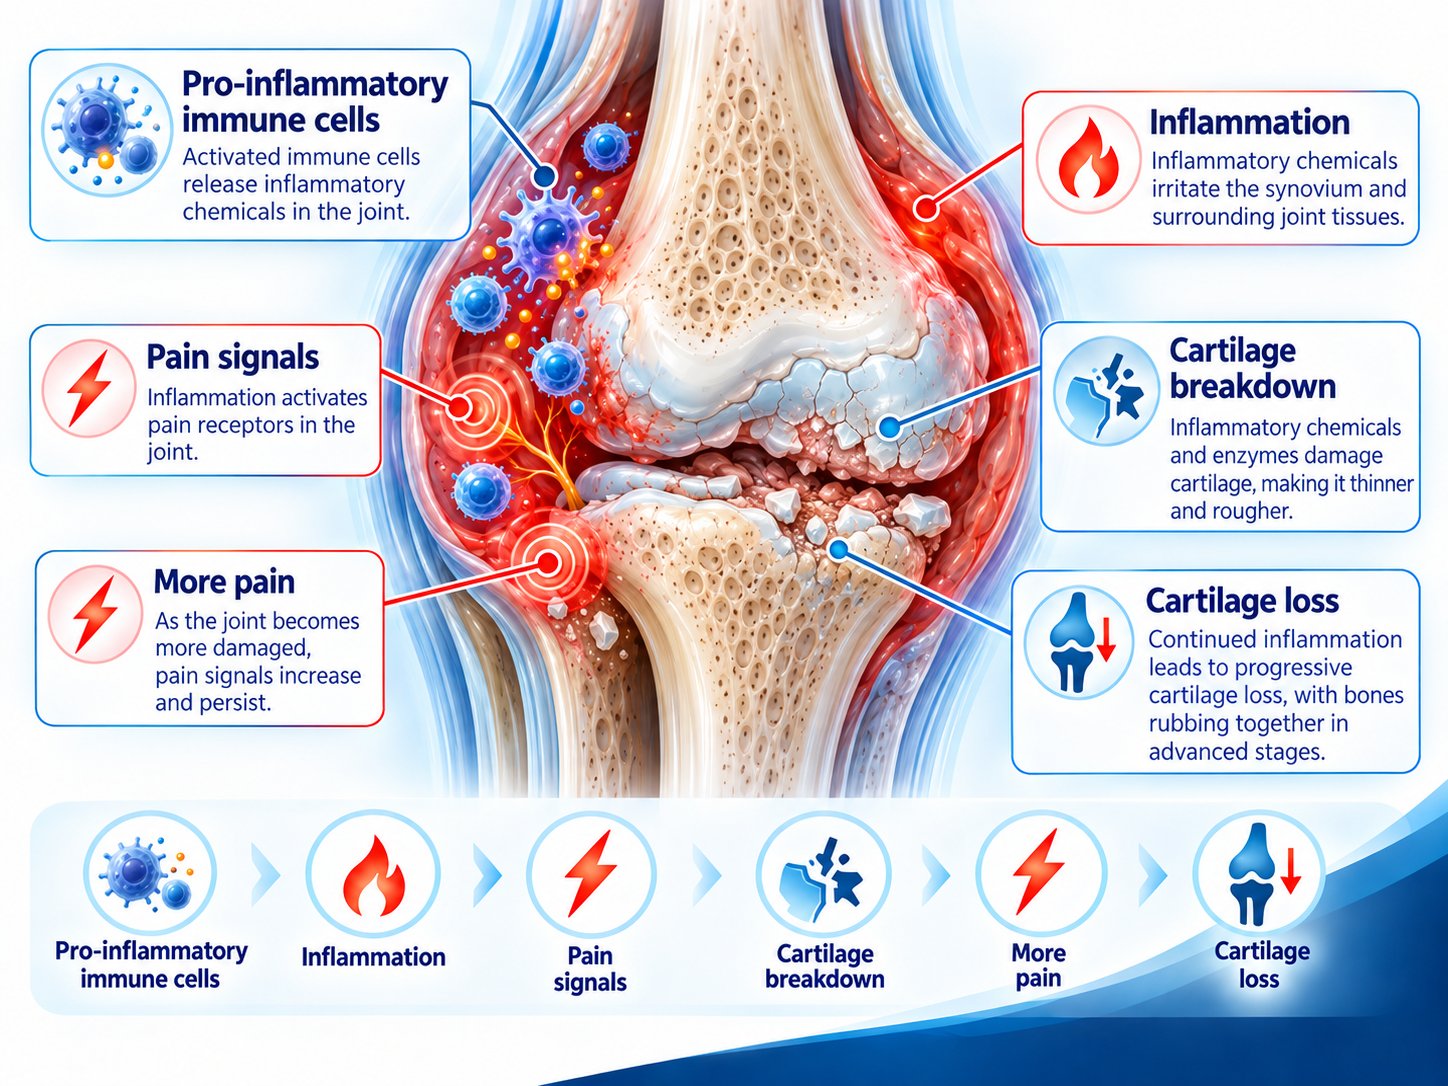
In osteoarthritis, the balance between the breakdown and the repair of cartilage is disturbed. The cartilage cells (chondrocytes) produce enzymes and inflammatory messengers that degrade the cartilage matrix. The bone beneath the cartilage thickens and forms bony outgrowths, and the joint lining becomes inflamed at times. The knee is affected most often, followed by the hip and the hand.[1]
Rheumatoid arthritis differs in cause, pattern and treatment. It is an autoimmune disease, usually affects the small joints of the hands and feet on both sides and shows rheumatoid factor or anti-CCP in the blood. It is treated with disease-modifying medication, which plays no role in osteoarthritis; details on our rheumatoid arthritis page.
Degeneration of the spine — discs, vertebral endplates, facet joints and nerve roots — is described on our spine page.
What causes OA, and what are the risk factors?
Primary osteoarthritis develops without a recognisable cause, mainly with age. Secondary osteoarthritis follows earlier joint injuries, misalignment, inflammation of the joint, overload or metabolic diseases. The main risk factors are:
- Older age
- Excess weight
- Earlier joint injuries, such as meniscus or cruciate ligament tears
- Misalignment and overload of the joint
- Hereditary factors
- Female sex, especially after the menopause
More on this in our blog article on osteoarthritis.
What drives the progression of OA?
The cause of osteoarthritis and what drives it forward are two separate questions. Once the cartilage is damaged, abnormal loading from misalignment, excess weight or an unstable joint keeps wearing it down. Phases of inflammation in the joint lining release messengers that further degrade the cartilage and cause pain, also in early stages.[1] Our programme is aimed at this inflammation and the course of the disease, not at its cause.
Can early detection of joint changes help to prevent osteoarthritis?
Possibly. For cancer, prevention through early detection of precursor lesions, such as colon polyps, has long been established; for osteoarthritis, the concept of “pre-osteoarthritis” is being discussed in expert circles. Modern imaging, especially MRI, can show early changes in the articular cartilage and the bone beneath it; optical coherence tomography (OCT) is being investigated for this purpose. Caught early, joint stress can be relieved, biomechanics improved and exercise adapted.
2. What is the guideline-based standard of care for OA?
According to international guidelines, the core treatment of osteoarthritis consists of education, structured exercise and, in knee osteoarthritis, weight management.[12] The standard of care also includes:
- Physiotherapy and supportive devices such as insoles, braces or a walking stick
- NSAIDs as gel on the knee; as tablets for a limited time, with caution in heart, kidney or stomach disease
- Pain relievers such as paracetamol and, rarely, opioid analogues
- Injections of cortisone into the joint, which relieve pain for a few weeks
- Injections of hyaluronic acid into the joint, with mixed results in studies
- In advanced osteoarthritis, joint replacement
In an external two-year randomised study in knee osteoarthritis, repeated cortisone injections led to more cartilage loss than saline, without less pain.[13]
Important: This is the established standard of care. ANOVA IRM’s programme is offered alongside — not in place of — appropriate established treatment.
How do common OA treatments compare in effect, risks and side effects?
| Treatment | Given as | Pain | Inflammation | Cartilage wear | Risks | Side effects |
|---|---|---|---|---|---|---|
| Cortisone | Injection into the joint, tablets | Reduced quickly, for a few weeks | Reduced | Not slowed; more cartilage loss with repeated injections | Joint infection (rare), cartilage loss | Rise in blood sugar, skin changes at the injection site |
| NSAIDs (COX-1/COX-2), e.g. ibuprofen, diclofenac | Tablets, gel | Reduced | Reduced | Not slowed | Stomach and bowel bleeding, kidney and heart disease | Stomach pain, high blood pressure |
| COX-2 inhibitors, e.g. celecoxib | Tablets | Reduced | Reduced | Not slowed | Heart attack and stroke | Fewer stomach problems than other NSAIDs |
| Pain relievers, e.g. paracetamol, opioid analogues | Tablets, drops | Reduced | Not reduced | Not slowed | Liver damage (paracetamol), dependence (opioids) | Nausea, constipation, drowsiness |
| Hyaluronic acid | Injection into the joint | Reduced in some patients | Little effect | No proven effect | Joint infection (rare) | Temporary swelling or pain |
What can you do yourself with OA: exercise, weight and nutrition?
Exercise is the most important measure you can take yourself. Physiotherapy, manual therapy and insoles help to stabilise the joint and correct misalignments. A physiotherapist can show you exercises that, done regularly, can improve strength and range of motion. Cycling with a correctly adjusted saddle is good for knee problems, as are walking and Nordic walking. Swimming is rather not recommended at first in knee osteoarthritis, because the knee cannot avoid twisting movements.
In overweight people, losing weight relieves the knee and hip. There are still few proven correlations for nutrition, but some approaches are being investigated. A diet low in meat and rich in vegetables may help, and alcohol and nicotine should be avoided. Supplements discussed for their anti-inflammatory effect include omega-3 fatty acids, turmeric, chondroitin sulfate, MSM and green-lipped mussel extract. We are happy to advise you on supplements and on infusion therapies.
When is a joint replacement needed, and what should you know before it?
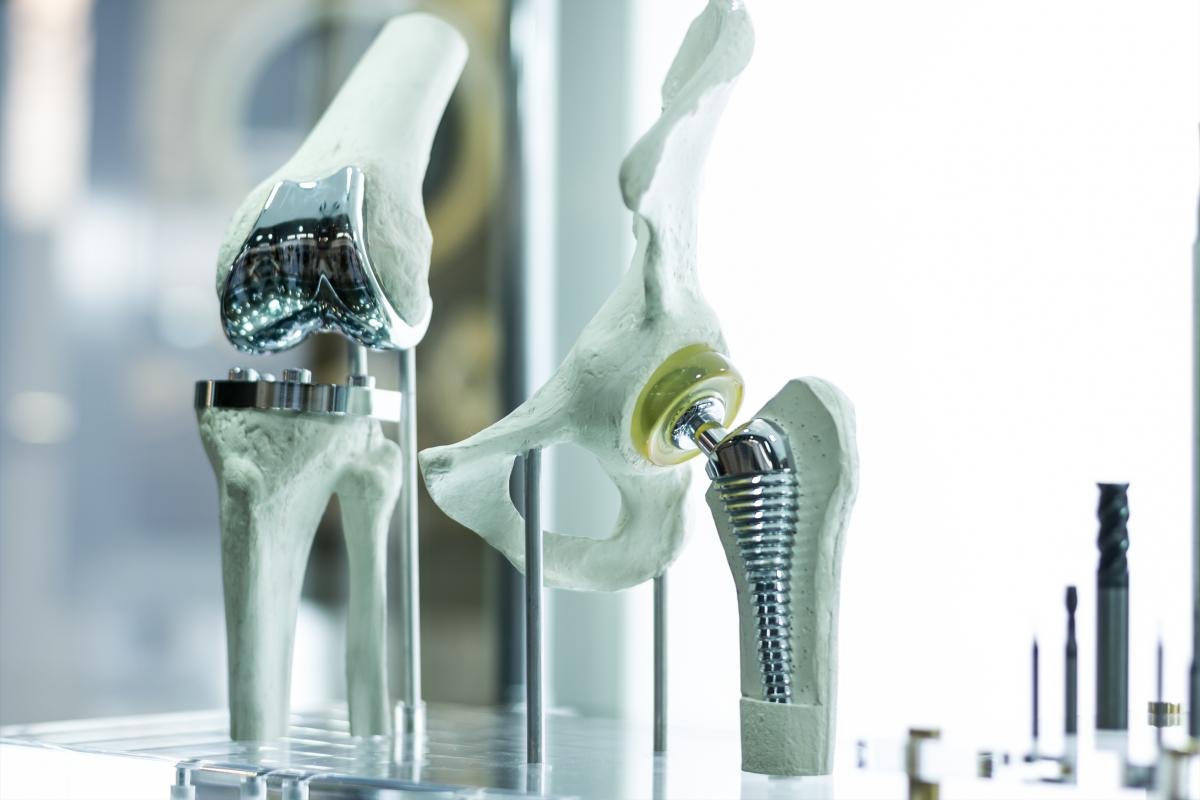
A joint replacement is considered in advanced osteoarthritis when pain and limitation persist despite all conservative treatment. In an external randomised study, knee replacement followed by non-surgical treatment led to greater improvement than non-surgical treatment alone, but also to more serious adverse events.[14] In national registries, about 90% of knee replacements and 70% of hip replacements were still in place after 20 years, and 82% and 58% after 25 years.[15],[16] Published data also show:
- Persistent pain after the operation affected 44% of patients after knee replacement and 27% after hip replacement in one study.[17]
- In the first two weeks after surgery, the risk of a heart attack was about 31 times higher after knee replacement and 25 times higher after hip replacement. In absolute terms, 0.21% and 0.51% of patients had a heart attack within six weeks.[18]
- In a US study, 34% of knee replacements were classified as inappropriate by a validated algorithm, and 22% as inconclusive.[19]
- Smokers had a higher risk of stroke, surgical site infection, pneumonia and death within one year after hip or knee replacement than non-smokers.[20]
Stem cell therapy is therefore an option some patients consider before joint replacement, with the aim of postponing it.
How is OA diagnosed, and what do we not do ourselves?
Osteoarthritis is diagnosed from the history, a physical examination and imaging. On X-ray, joint space narrowing, osteophytes and changes of the bone beneath the cartilage are graded from 0 to 4 on the Kellgren–Lawrence scale. MRI shows cartilage, bone marrow oedema and inflammation of the joint lining. Where a joint is swollen, a sample of joint fluid (joint aspiration) helps to exclude gout, infection or rheumatoid arthritis. Physiotherapy, arthroscopy, microfracture and joint replacement stay with your treating doctors and specialists. We carry out MRI and CT ourselves at the Institut für Bildgebende Diagnostik in the same building.
3. What is the scientific rationale for BMC in OA?
Bone marrow concentrate (BMC)
ANOVA IRM has not yet tested BMC for osteoarthritis in a clinical study. In an external retrospective study of 121 patients with advanced knee osteoarthritis (grade 3 and 4), pain fell from 8.3 to 4.5 on a scale of 0 to 10 after a single BMC injection. Function on the Oxford Knee Score rose from 20.2 to 32.3, after 6 to 30 months, without complications and without a control group.[5] In an external registry of patients with knee osteoarthritis, pain and function improved after BMC.[6]
In two small external placebo-controlled studies of 25 patients each, both knees improved, and a benefit of BMC over saline could not yet be demonstrated; MRI showed no cartilage regrowth after 12 months.[8],[9] A recent review describes inconsistent results due to differing preparation, patient selection and application, and calls for larger randomised studies.[7] To our knowledge, there is no phase 3 study of BMC in osteoarthritis.
What is the efficacy hypothesis behind BMC in OA?
Stem cells can communicate with the immune cells that drive inflammation, through messengers such as growth factors, cytokines, proteins, microRNAs and extracellular vesicles. They are thought to dampen the inflammation in the joint lining and the cartilage. BMC is not intended to form new cartilage directly. Injected into the joint, BMC is intended to reduce inflammation and pain first; in the resting phase that may follow, the cartilage is less exposed to further breakdown.
Mesenchymal stem cells and secretome — analogous evidence
Studies with cultured mesenchymal stem cells or their secretome, which are different products from BMC, point in the same direction. In an external laboratory and animal study in mice with osteoarthritis, the secretome of bone marrow-derived mesenchymal stem cells reduced pain and prevented cartilage damage.[21] In a small external phase 1/2 study, mesenchymal stem cells injected into knees with osteoarthritis improved function and reduced cartilage defects.[22]
Talk to us about current changes or additions to the osteoarthritis programme.
4. Where does our own OA evidence stand?
We have not yet evaluated our own data on osteoarthritis. Our experience so far suggests that pain is more likely to ease when it is caused by inflammation in the joint. Stem cells do not cure osteoarthritis, and improvements are always limited in time. These are unsystematic observations and allow no prediction for you.
Some patients describe their experience on our testimonials page; these are individual accounts.
How do we assess the course after OA treatment?
After treatment, we ask about and assess the following:
- Pain and stiffness
- Range of motion of the joint
- Walking distance and tolerance of load
- Function in everyday life and quality of life
- Use of pain medication
- Joint-specific scores, for example the Oxford Knee Score
- Imaging, where useful
What the published OA evidence does not yet tell us
- Most studies of BMC in osteoarthritis are small, and only a few have a control group.
- The bone marrow products studied were prepared and dosed differently from BMC at ANOVA IRM.
- In Germany and the EU, no stem cell-based treatment is approved as a standard treatment for osteoarthritis.
5. Legal framework for BMC in OA
For osteoarthritis, ANOVA IRM uses BMC, an advanced therapy medicinal product. It is manufactured under a procurement authorisation (Section 20b AMG) and a manufacturing authorisation (Section 13 AMG) of the Hessian State Office for Health and Care (HLfGP), which inspects the facility regularly. The injection into the joint is given as an individual treatment attempt (individueller Heilversuch), after full disclosure and with your informed consent. As BMC is used only for our own patients, it requires no authorisation under Section 4b, no marketing authorisation under Section 21 and no approval under Section 21a AMG. More on our regulatory status page.
6. Frequently asked questions — osteoarthritis, evidence and approval status
Is stem cell therapy approved for osteoarthritis anywhere?
Are MSC studies evidence that BMC works in osteoarthritis?
Can stem cell therapy help with osteoarthritis pain?
It may. BMC is intended to reduce the inflammation in the joint that often causes the pain. In our experience, pain reduction is more likely when the pain is inflammatory; any improvement is limited in time.
Can stem cell therapy delay or prevent a joint replacement in osteoarthritis?
Postponing a joint replacement is one of the aims of the treatment. Whether BMC can delay or prevent a joint replacement has not yet been investigated in controlled long-term studies.
Can advanced or “bone-on-bone” osteoarthritis be treated?
Yes, BMC can also be considered in advanced osteoarthritis, after individual assessment. The less cartilage is left, the more limited the expected effect; in end-stage osteoarthritis, a joint replacement is often the more suitable option.
Is success guaranteed with stem cell treatment for osteoarthritis?
No. Whether BMC helps in your osteoarthritis cannot be predicted. Your doctor weighs the possible benefit against the risks for you and recommends treatment only where the benefit is likely to outweigh them.
What is gonarthrosis?
Gonarthrosis is osteoarthritis of the knee joint, the most common form of osteoarthritis. The cartilage between the thigh bone, the shin bone and the kneecap wears down, causing pain on starting to move, under load and on climbing stairs. Osteoarthritis of the hip is called coxarthrosis.
Is osteoarthritis hereditary?
Partly. Depending on the joint, genes account for an estimated 35 to 65% of the risk: a twin study in women put the genetic share at about 40% for knee and 65% for hand osteoarthritis.[3] Siblings of people with a hip replacement for osteoarthritis had a several times higher risk of hip osteoarthritis.[4]
What is the difference between osteoporosis and osteoarthritis?
Osteoporosis is a loss of bone density that makes bones fragile and prone to fracture. Osteoarthritis is a disease of the joint, in which the cartilage wears down and the bone beneath it becomes denser. Both are common in older age and can occur together.
How does cortisone work in osteoarthritis?
An injection of cortisone into an arthritic knee or hip usually eases pain within days, but the effect wears off after a few weeks. In an external two-year study, repeated injections caused more cartilage loss than saline.[13]
What are NSAID, NSAP and NSAR in osteoarthritis?
All three abbreviations refer to non-steroidal anti-inflammatory drugs, the most widely used pain relievers in osteoarthritis. “Non-steroidal” means that they are not related to cortisone. Taken for long periods, they can harm the stomach lining, the kidneys and the heart; COX-2 inhibitors cause fewer stomach problems.
- NSAID: non-steroidal anti-inflammatory drug
- NSAP: non-steroidal anti-inflammatory product (German usage)
- NSAR: nichtsteroidales Antirheumatikum (German for non-steroidal anti-rheumatic drug)
Which anti-phlogistic drugs are used in osteoarthritis?
In osteoarthritis, the anti-inflammatory (anti-phlogistic) drugs used are mainly:
- Non-steroidal anti-inflammatory drugs (NSAIDs), including COX-2 inhibitors, as tablets or gel
- Glucocorticoids such as cortisone, mostly as an injection into the joint
Disease-modifying anti-rheumatic drugs (DMARDs), biologics and JAK inhibitors are used in rheumatoid arthritis, not in osteoarthritis.
Does ANOVA IRM perform microfracture for osteoarthritis?
No. In microfracture, small holes are drilled into the bone beneath a cartilage defect so that bone marrow cells form a replacement tissue (fibrocartilage). It is a surgical procedure performed by orthopaedic surgeons; ANOVA IRM does not perform it.
Do hormones play a role in osteoarthritis?
Research is investigating this. Osteoarthritis becomes more common in women after the menopause, and oestrogen and testosterone are discussed as influencing factors. In overweight men, lower levels of the hormone androstenedione were associated with a higher risk of knee or hip replacement.[10] Women taking hormone replacement therapy after a joint replacement needed a revision about 40% less often.[11]
These are associations, not proof of an effect. If you additionally wish, we analyse your hormone levels in the blood; we do not offer hormone therapy.
What type of stem cell therapy does ANOVA use for OA?
For osteoarthritis we use bone marrow concentrate (BMC) from your own pelvic bone, with mesenchymal and haematopoietic stem cells and growth factors in their natural composition. Details are on our BMC page.
How common is osteoarthritis (OA)?
What are the symptoms of osteoarthritis (OA)?
The main symptoms are pain, stiffness and restricted movement of the affected joint:
- Pain on starting to move (start-up pain) and under load
- Pain at rest and at night when inflammation is active
- Stiffness in the morning or after rest, usually brief
- Swelling, a feeling of warmth or fluid in the joint
- Grinding or cracking of the joint and, later, misalignment
Which forms of osteoarthritis (OA) are there, and how does it progress?
Osteoarthritis is classified by its cause, by the joint affected and by its severity on X-ray (Kellgren–Lawrence grades 0 to 4). It usually progresses slowly over years, often with alternating calm and inflamed phases.
- Primary osteoarthritis: without a recognisable cause, mainly with age.
- Secondary osteoarthritis: after injuries, misalignment, inflammation or metabolic diseases.
- Activated osteoarthritis: a phase with inflammation, swelling and pain at rest.
- Polyarthrosis: osteoarthritis of several joints, often of the finger joints.
What complications can osteoarthritis (OA) cause?
Persistent pain, loss of mobility and misalignment of the joint are possible. Pain-related lack of exercise can lead to weight gain and loss of muscle, which in turn burdens the joint. In end-stage osteoarthritis, a joint replacement is often needed.
Important Pages
Questions people usually ask next. Each is answered in full on its own page.
- Who are we?
- Is ANOVA legal?
- Is stem cell therapy safe?
- What is BMC (Bone Marrow Concentrate)?
- What are stem cells?
- What should I ask when looking for a stem cell treatment?
- Which conditions do we treat?
- Joint and back pain — overview
- Joints and sport injuries
- Rheumatoid arthritis
- Osteoarthritis treatment options — standard and emerging
Affiliations of ANOVA
ANOVA IRM shares its premises in Offenbach with two further institutions owned by Dr. Stehling: the Institut für Bildgebende Diagnostik (IBDO), providing MRI and CT imaging, and the VITUS PRIVATKLINIK Prof. Dr. Stehling GmbH. Because imaging is carried out in the same building, MRI with contrast and CT-guided injections into arthritic joints can be performed in-house. See diagnostics at ANOVA IRM.
References — osteoarthritis literature
General literature on joint and back pain is maintained on the pillar page, on joint injuries on the joints and sport injuries page and on bone marrow on the BMC page.
Osteoarthritis — disease, frequency and heredity
- [1] Hunter DJ, Bierma-Zeinstra S. Osteoarthritis. Lancet. 2019;393(10182):1745–1759. doi:10.1016/S0140-6736(19)30417-9. PMID: 31034380.
- [2] GBD 2021 Osteoarthritis Collaborators. Global, regional, and national burden of osteoarthritis, 1990–2020 and projections to 2050: a systematic analysis for the Global Burden of Disease Study 2021. Lancet Rheumatol. 2023;5(9):e508–e522. doi:10.1016/S2665-9913(23)00163-7. PMID: 37675071.
- [3] Spector TD, Cicuttini F, Baker J, et al. Genetic influences on osteoarthritis in women: a twin study. BMJ. 1996;312(7036):940–943. doi:10.1136/bmj.312.7036.940. PMID: 8616305.
- [4] Lanyon P, Muir K, Doherty S, et al. Assessment of a genetic contribution to osteoarthritis of the hip: sibling study. BMJ. 2000;321(7270):1179–1183. doi:10.1136/bmj.321.7270.1179. PMID: 11073507.
Bone marrow concentrate (BMC) in osteoarthritis
- [5] Themistocleous GS, Chloros GD, Kyrantzoulis IM, et al. Effectiveness of a single intra-articular bone marrow aspirate concentrate (BMAC) injection in patients with grade 3 and 4 knee osteoarthritis. Heliyon. 2018;4(10):e00871. doi:10.1016/j.heliyon.2018.e00871. PMID: 30364761.
- [6] Centeno C, Pitts J, Al-Sayegh H, et al. Efficacy of autologous bone marrow concentrate for knee osteoarthritis with and without adipose graft. Biomed Res Int. 2014;2014:370621. doi:10.1155/2014/370621. PMID: 25276781.
- [7] Park D, Koh HS, Choi YH, et al. Bone marrow aspirate concentrate (BMAC) for knee osteoarthritis: a narrative review of clinical efficacy and future directions. Medicina (Kaunas). 2025;61(5):853. doi:10.3390/medicina61050853. PMID: 40428811.
- [8] Shapiro SA, Kazmerchak SE, Heckman MG, et al. A prospective, single-blind, placebo-controlled trial of bone marrow aspirate concentrate for knee osteoarthritis. Am J Sports Med. 2017;45(1):82–90. doi:10.1177/0363546516662455. PMID: 27566242.
- [9] Shapiro SA, Arthurs JR, Heckman MG, et al. Quantitative T2 MRI mapping and 12-month follow-up in a randomized, blinded, placebo controlled trial of bone marrow aspiration and concentration for osteoarthritis of the knees. Cartilage. 2019;10(4):432–443. doi:10.1177/1947603518796142. PMID: 30160168.
Sex hormones and osteoarthritis
- [10] Hussain SM, Cicuttini FM, Giles GG, et al. Relationship between circulating sex steroid hormone concentrations and incidence of total knee and hip arthroplasty due to osteoarthritis in men. Osteoarthritis Cartilage. 2016;24(8):1408–1412. doi:10.1016/j.joca.2016.04.008. PMID: 27084353.
- [11] Prieto-Alhambra D, Javaid MK, Judge A, et al.; COASt Study Group. Hormone replacement therapy and mid-term implant survival following knee or hip arthroplasty for osteoarthritis: a population-based cohort study. Ann Rheum Dis. 2015;74(3):557–563. doi:10.1136/annrheumdis-2013-204043. PMID: 24451241.
Standard of care: guidelines and cortisone
- [12] Bannuru RR, Osani MC, Vaysbrot EE, et al. OARSI guidelines for the non-surgical management of knee, hip, and polyarticular osteoarthritis. Osteoarthritis Cartilage. 2019;27(11):1578–1589. doi:10.1016/j.joca.2019.06.011. PMID: 31278997.
- [13] McAlindon TE, LaValley MP, Harvey WF, et al. Effect of intra-articular triamcinolone vs saline on knee cartilage volume and pain in patients with knee osteoarthritis: a randomized clinical trial. JAMA. 2017;317(19):1967–1975. doi:10.1001/jama.2017.5283. PMID: 28510679.
Joint replacement — durability, outcomes and risks
- [14] Skou ST, Roos EM, Laursen MB, et al. A randomized, controlled trial of total knee replacement. N Engl J Med. 2015;373(17):1597–1606. doi:10.1056/NEJMoa1505467. PMID: 26488691.
- [15] Evans JT, Walker RW, Evans JP, et al. How long does a knee replacement last? A systematic review and meta-analysis of case series and national registry reports with more than 15 years of follow-up. Lancet. 2019;393(10172):655–663. doi:10.1016/S0140-6736(18)32531-5. PMID: 30782341.
- [16] Evans JT, Evans JP, Walker RW, et al. How long does a hip replacement last? A systematic review and meta-analysis of case series and national registry reports with more than 15 years of follow-up. Lancet. 2019;393(10172):647–654. doi:10.1016/S0140-6736(18)31665-9. PMID: 30782340.
- [17] Wylde V, Hewlett S, Learmonth ID, et al. Persistent pain after joint replacement: prevalence, sensory qualities, and postoperative determinants. Pain. 2011;152(3):566–572. doi:10.1016/j.pain.2010.11.023. PMID: 21239114.
- [18] Lalmohamed A, Vestergaard P, Klop C, et al. Timing of acute myocardial infarction in patients undergoing total hip or knee replacement: a nationwide cohort study. Arch Intern Med. 2012;172(16):1229–1235. doi:10.1001/archinternmed.2012.2713. PMID: 22826107.
- [19] Riddle DL, Jiranek WA, Hayes CW. Use of a validated algorithm to judge the appropriateness of total knee arthroplasty in the United States: a multicenter longitudinal cohort study. Arthritis Rheumatol. 2014;66(8):2134–2143. doi:10.1002/art.38685. PMID: 24974958.
- [20] Singh JA, Houston TK, Ponce BA, et al. Smoking as a risk factor for short-term outcomes following primary total hip and total knee replacement in veterans. Arthritis Care Res (Hoboken). 2011;63(10):1365–1374. doi:10.1002/acr.20555. PMID: 21770042.
Mesenchymal stem cells and secretome — analogous evidence, not BMC itself
- [21] Khatab S, van Osch GJVM, Kops N, et al. Mesenchymal stem cell secretome reduces pain and prevents cartilage damage in a murine osteoarthritis model. Eur Cell Mater. 2018;36:218–230. doi:10.22203/eCM.v036a16. PMID: 30398288.
- [22] Jo CH, Lee YG, Shin WH, et al. Intra-articular injection of mesenchymal stem cells for the treatment of osteoarthritis of the knee: a proof-of-concept clinical trial. Stem Cells. 2014;32(5):1254–1266. doi:10.1002/stem.1634. PMID: 24449146.
Approval status
- [23] Ministry of Food and Drug Safety (MFDS), Republic of Korea. Bio & Cosmetics — Manufactures: CARTISTEM (human umbilical cord blood-derived mesenchymal stem cells), approved by MFDS in January 2012 for knee articular cartilage defects in patients with osteoarthritis. https://mfds.go.kr/eng/brd/m_30/view.do?seq=69798 (accessed 7 October 2026).