

Stem Cell Therapy for Neurological and Neurodegenerative Diseases
The ANOVA Stroke Stem Cell Secretome Treatment Programme Germany
Autologous, adipose tissue-derived MSC secretome (MSEC) therapy for people after a stroke, also called a cerebrovascular accident (CVA) or brain attack. Offenbach, Germany. Experimental — fully legal — manufactured under German regulatory authorisation and official inspection since 2018.
You have tried a lot. Perhaps you have been told there is nothing more to be done. We listen first, examine thoroughly, and then tell you honestly whether a stem cell-based therapy, one of our programmes or another option could be right for you. Each option is discussed as an addition to your current treatment, never as a replacement.
| Component | Detail |
|---|---|
| Two products | Bone Marrow Concentrate (BMC) and Mesenchymal Stem Cell Secretome (MSEC), each manufactured under official authorisation; no marketing authorisation (experimental) |
| Authorisations | BMC § 20b / § 13 AMG · MSEC § 20b / § 20c AMG (German Medicines Act) |
| Location | Offenbach am Main, Germany |

the essentials at a glance.
You are hereIntroduction & Summary
What is a stroke, in brief?
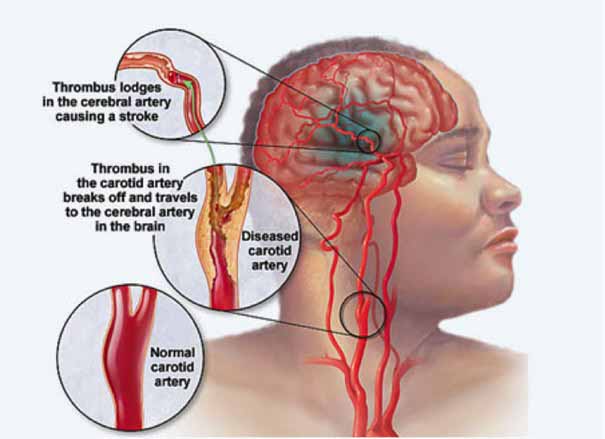
A stroke happens when the blood supply to part of the brain is suddenly interrupted. Deprived of oxygen, brain cells in the affected area begin to die within minutes. Depending on where this happens, movement, sensation, speech, vision, swallowing or thinking can be affected. Stroke is one of the leading causes of death and of lasting disability worldwide.[1]
Most strokes are ischaemic strokes, caused by a blood clot that blocks an artery; the others are haemorrhagic strokes, caused by bleeding into or around the brain.[1] A transient ischaemic attack (TIA) causes stroke symptoms that disappear again, and it is an important warning sign. Doctors distinguish the acute phase in the first days, the subacute phase of the following months and the chronic phase from about six months after the stroke.[4] The diagnosis rests on an emergency brain scan, CT or MRI, together with a neurological examination. To date no cure is known for the lasting consequences of a stroke.
Common symptoms include sudden one-sided weakness or numbness, slurred speech or difficulty finding words, loss of vision and loss of balance; afterwards paralysis (hemiparesis), spasticity, aphasia, swallowing difficulties, fatigue and depression. Anyone with sudden stroke symptoms should call the emergency services immediately.
More details can be found below in our scientific section on stroke.
What is the ANOVA stroke programme?
ANOVA offers autologous mesenchymal stem cell secretome (MSEC) therapy for people after a stroke, in addition to their rehabilitation and the medication their doctors prescribe. The programme combines a diagnostic MRI with repeated applications of MSEC into the cerebrospinal fluid. Each component is selected individually; the programme is not a fixed package.
Stem cells are thought to act mainly through soluble factors, together called the secretome, which includes exosomes and many other factors. After a stroke, the damaged area is surrounded by tissue in which inflammation, a leaky blood–brain barrier and glial scarring can continue for weeks to months. At the same time, the brain tries to reorganise its remaining networks. MSEC is intended to potentially influence this environment and the brain’s capacity to adapt; it is not intended to replace nerve cells that have already died.
ANOVA IRM has not yet tested MSEC in a clinical study. The current state of research is described in the clinical and scientific section below.

The ANOVA Stroke Programme — Components
Diagnostic MRI
An MRI of the brain, with contrast where needed, shows where the stroke occurred, how large the damaged area is and whether there are further changes, such as disease of the small blood vessels. It helps to plan treatment with MSEC.
MSC secretome (MSEC)
MSEC is the cell-free mixture of signalling molecules released by your own mesenchymal stromal cells from fat tissue, given intrathecally into the cerebrospinal fluid. External laboratory and animal studies suggest that such factors may dampen inflammation after a stroke and support the growth of blood vessels and nerve connections.[36],[37] Small external clinical studies with related MSC products after a stroke are summarised in the clinical and scientific section below.
Physiotherapy, occupational therapy and speech therapy are not part of our programme; they continue with your own therapists at home.
Which diagnostics do we use for stroke at ANOVA IRM?
Which tests are used to diagnose a stroke?
A stroke is diagnosed in hospital as an emergency, with a neurological examination and a scan of the brain. CT shows within minutes whether an artery is blocked or a vessel is bleeding; MRI, with contrast where needed, also shows small fresh infarcts. Further tests look for the cause, for example heart rhythm monitoring and ultrasound of the neck arteries and the heart.
What do we review before stroke treatment at ANOVA IRM?
Before any treatment decision we review your hospital discharge letters, your brain imaging, the time since the stroke and your rehabilitation so far. We look at your current medication, in particular blood thinners, and check that you are fit for the brief sedation required for tissue collection.
- Standard: an MRI of the abdominal wall to exclude a hernia is required before the liposuction, taken no more than four weeks beforehand. It can be done at home or at ANOVA IRM.
- Optional: CT guidance for the intrathecal application at ANOVA IRM, used while the dose is given.
- Optional: further MRI scans of the brain, with or without contrast, where your situation after the stroke calls for them. Examples are documenting the damaged area before treatment or following up a finding on an earlier scan.
Imaging can be carried out in-house; all examinations can also be done by your own doctors. The full diagnostic pathway is described on our diagnostics page.
Why ANOVA IRM for stroke?
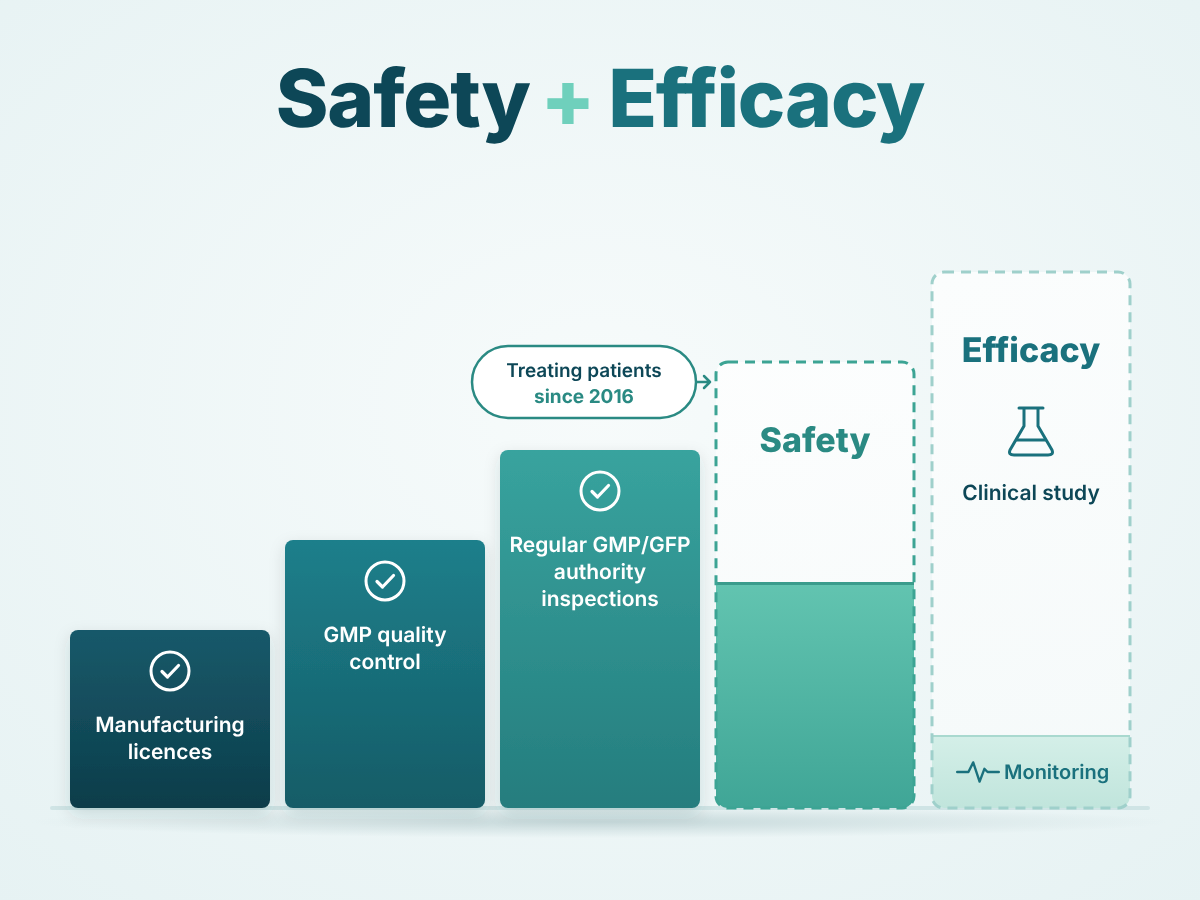
Dr. mult. Stehling and ANOVA IRM have been treating people with neurological and neurodegenerative diseases since 2016; 188 people so far. Of these, 14 had a stroke; we treated the first in 2016 (as of October 2026).
ANOVA IRM has made MSEC in its own facility in Offenbach since 2018 (see our regulatory status). Applications into the cerebrospinal fluid are given with CT guidance from the radiology in the same building where the anatomy requires it. Your neurologist and your rehabilitation team remain the basis of care after a stroke.
What can you expect as a patient after a stroke?
The first assessment can take place remotely, by phone or video, before any journey to Germany; a relative can join the call. Treatment itself takes place in person in Offenbach am Main, less than 20 minutes from Frankfurt Airport. Before you decide, you receive an individual written cost estimate; the services of our patient care team are free of charge. If you would like existing findings assessed independently, we also offer a second opinion.
Quick answers
Is there a cure for stroke?
Not for the damage that remains. In the first hours, clot-dissolving medication (thrombolysis) or removal of the clot (thrombectomy) can limit the damage, but tissue that has already died cannot be restored.[17],[18] Recovery then relies on rehabilitation and the prevention of a further stroke, and experimental approaches such as mesenchymal stem cell secretome (MSEC) and other cell-based therapies are being explored.[19],[28]
Does stem cell therapy cure stroke?
No. Stem cell therapy is not a cure for stroke. The use of MSEC at ANOVA IRM aims to influence inflammation and the environment of the damaged brain tissue, and it is given alongside rehabilitation and stroke prevention, never instead of them.
Is stroke stem cell therapy legal in Germany?
Yes, as long as the product is made under official authorisations. ANOVA IRM manufactures MSEC under a collection (procurement) authorisation (Section 20b AMG) and a manufacturing authorisation under Section 20c AMG, granted by the Darmstadt Regional Council, today the Hessian State Office for Health and Care (HLfGP), with the involvement of the Paul-Ehrlich-Institut. After a stroke, MSEC is given as an individual therapeutic attempt (individueller Heilversuch); the legal basis is explained on our regulatory status page.
Is stroke stem cell therapy safe?
Not without qualification. The fat collection, the brief sedation and the lumbar puncture carry risks, which your doctor explains before treatment; after a stroke, blood-thinning medication needs particular attention. Manufacturing under an official authorisation adds a layer of safety. The competent authority inspects the facility every two years and must be told of every change to the process and every new material. Providers without an authorisation are not subject to this control.
Since 2016, Dr. mult. Stehling and ANOVA IRM have produced MSEC with an unchanged process, since 2018 under an authorisation according to Section 20c AMG, and they have treated 355 people with it (as of October 2026). To date, no serious adverse event has been caused by the product. Safety is first examined in phase 1/2 studies with roughly 10 to 100 patients; ANOVA IRM has not run such a study, but has treated well above that number. Ask every provider which authorisations it holds; what regulators warn about is summarised under unproven therapies.
What medication is used for stroke?
To prevent a further ischaemic stroke, antiplatelet drugs such as aspirin or clopidogrel are used, or anticoagulants if atrial fibrillation is the cause, together with statins and blood pressure treatment.[19] In the acute phase, alteplase or tenecteplase can dissolve the clot.[17] Mesenchymal stem cell secretome (MSEC) at ANOVA IRM is added to this medication and does not replace it.
the essentials at a glance.
You are hereStroke Treatment: Eligibility, Process & Cost
In this section you will find everything about treatment after a stroke (cerebrovascular accident, CVA) at ANOVA IRM: who is eligible, the process step by step and the cost.
What does the stroke treatment timeline look like?
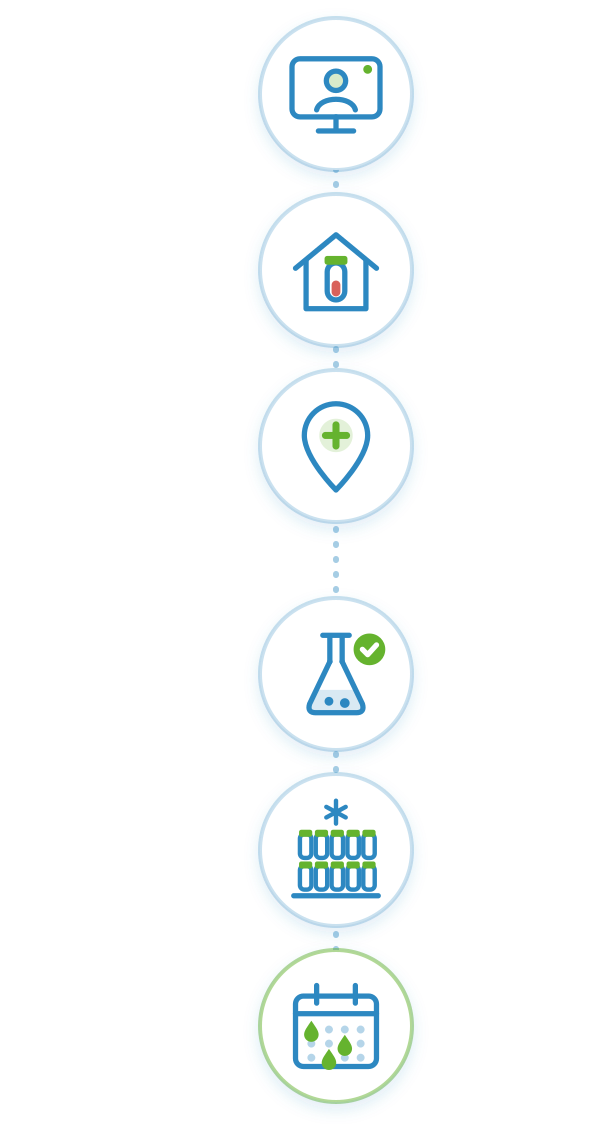
- 01
Initial evaluation
Remote, by phone or video — typically 2 weeks to a few months
- 02
Preliminary screening
In your home country, to avoid an unnecessary journey
- 03
First visit — bloodwork and tissue collection
Two-day outpatient visit to Offenbach: bloodwork first, then — if the results are in order — mini-liposuction under brief sedation
- 04
Production and quality control
Approximately 4 weeks; yields 10 doses per production cycle
- 05
Storage
Up to 2 years, allowing an extended personalised schedule
- 06
Application schedule
Set individually: all 10 doses over the medium term, for example over about three months — weekly single doses if you live close by, otherwise two doses per visit about every two to three weeks
Who qualifies for stroke treatment, and what are the requirements?
We consider adults after an ischaemic or haemorrhagic stroke whose acute hospital treatment is complete and whose condition is medically stable. People in the subacute phase and in the chronic phase, including years after the stroke, may be considered; we recommend starting as soon as possible after the acute phase. Whether treatment makes sense is weighed individually. You need to be well enough for mini-liposuction under brief sedation and able to breathe independently and comfortably while lying down. You also need to be able to travel to Offenbach for repeated applications, if necessary with a companion. Every treatment recommendation follows a full clinical evaluation in which the treating physician weighs benefit and risk, and realistic expectations are part of that decision. Applying for an evaluation does not mean that treatment will be offered.
What are the contraindications for stroke treatment?
Our treatments are experimental. We treat only people for whom, after medical assessment, we consider the benefit-risk balance to support treatment.
Applies to all ANOVA treatments:
- Active cancer within the last two years
- Under the age of legal majority
- Pregnancy or breastfeeding
- Active infectious disease (hepatitis A, B, C, HIV, syphilis or other)
Specific to stroke:
- Unable to breathe unaided, or requiring a ventilator
- Difficulty breathing in the supine position
- Severe dysphagia with a high risk of aspiration during sedation
- Psychiatric disorder that would prevent informed consent or cooperation
- Aphasia (impaired understanding or production of language)
- Raised intracranial pressure or a space-occupying infarct
- Recent intracranial bleeding
- Anticoagulation that cannot be paused for the lumbar puncture
Blood-thinning medication is not a contraindication in itself. Whether it needs to be paused for the fat collection and the lumbar puncture is decided with your treating doctors; please never stop it on your own.

What does stroke therapy at ANOVA IRM involve, step by step?
What screening is needed before you travel for stroke treatment?
Before you travel, a preliminary screening in your home country — usually a blood test for HIV, hepatitis A, B or C, syphilis and other active infections — helps you avoid an unnecessary journey. Together with your discharge letters and brain imaging, it also shows whether medical factors would already rule out treatment.
What happens at your first visit to Offenbach after a stroke?
The first treatment visit takes about two days in Offenbach, on an outpatient basis. On the first day, bloodwork is repeated at ANOVA IRM as German medical rules require, and the physician completes the final assessment, including your blood-thinning medication. If the results are in order, a small amount of abdominal fat tissue is collected the next day by mini-liposuction under brief sedation. From this point to the first secretome application is usually four to six weeks.
How is your MSEC for stroke produced and quality-controlled?
Mesenchymal stromal cells are isolated from the collected tissue and expanded in our own facility in Offenbach. This takes place under official authorisation and officially inspected good professional practice (GFP, gute fachliche Praxis; similar to Good Tissue Practice, GTP, in the US, but more than GTP). These cells are then used to produce your MSEC preparation — the signalling molecules they release, not the living cells. Production and quality control take approximately four weeks and yield 10 doses per production cycle. Each patient batch is tested with methods validated according to the European Pharmacopoeia (Ph. Eur.) and GMP, and released under a documented procedure; the released secretome is stored at −80 °C and keeps for up to two years.
How often is MSEC applied after a stroke?
The consequences of a stroke are often long-lasting, and there is currently no cure for them. We therefore recommend using all 10 doses produced over the medium term, for example over about three months, rather than a single application, and starting as soon as possible after the acute phase; see the timeline above.
The schedule is set individually for each patient, for example:
- At the start: two intrathecal doses.
- If you live close by: a single MSEC dose about once a week.
- If you live further away: two doses per visit about every two to three weeks — about five visits over about three months for the 10 doses produced.
- Standard route for stroke: intrathecal, by lumbar puncture into the cerebrospinal fluid. This is intended to bring the secretome closer to the brain than an infusion into the bloodstream, which would have to cross the blood–brain barrier.
- Individual alternative: intravenous, if you specifically wish it or if systemic treatment is medically necessary.
The applications are planned around your rehabilitation, which continues at home. All doses must be used within the two-year shelf life of the stored MSEC; a later further course requires a new tissue collection and production cycle. Intrathecal applications are standard procedures when performed by experienced physicians; where the anatomy requires it, ANOVA IRM uses CT guidance from its in-house radiology. The benefit-risk assessment of intrathecal administration is set out on a separate page.
What does stroke treatment with MSEC cost?
MSEC treatment costs approximately €20,000–€36,000, depending on the number of doses (three to ten), and requires a two-day visit for tissue collection, followed by further visits. It is billed according to the German Medical Fee Schedule (GOÄ). The base package — the mini-liposuction and the first three MSEC doses — costs approximately €20,000; each further dose is charged separately at approximately €2,250 to €2,350 depending on the application route. Because we recommend using all 10 doses over the medium term after a stroke, most treatment plans reach the upper end of this range.
If a further course is planned later, a double liposuction can be recommended: it yields 20 doses, which can be used over the current shelf life of two years from a single collection. The cost is correspondingly higher and is shown in your individual estimate.
Further examinations and your sedation preferences also affect the total, and you receive an individual written estimate before any treatment decision. Our blog post on treatment cost explains what drives the cost of stem cell treatment in general. Travel, accommodation and other personal expenses, including those of an accompanying person, are not included. MSEC treatment after a stroke is generally self-funded; you can still ask your insurer about possible reimbursement. All prices are subject to change.

Why does the cost of stroke treatment vary with the application route?
All treatments at ANOVA IRM are billed according to the German Medical Fee Schedule (Gebührenordnung für Ärzte, GOÄ); within it, the cost varies mainly with the route of application. After a stroke we mainly administer MSEC intrathecally, because in our assessment it is most likely to act there: the cerebrospinal fluid is a small, closed compartment in direct contact with the brain. We use intravenous administration only if you specifically wish it or if systemic treatment is medically necessary. The exact cost of your treatment plan is set out in your individual written cost estimate.
Frequently asked questions — eligibility, process and travel
How is MSEC administered for stroke?
By intrathecal injection: our physicians in Offenbach give MSEC by lumbar puncture into the cerebrospinal fluid, with CT guidance where the anatomy requires it. After two doses at the start, the 10 doses are given over about three months: about once a week if you live nearby, otherwise two doses per visit about every two to three weeks. An infusion into a vein is used only at your request or if it is medically necessary.
How long does the whole stroke treatment process take?
Plan for roughly four to eight months from your first enquiry to the last dose. Gathering your discharge letters and brain scans for the remote assessment can take from two weeks to several months. After the two-day visit for tissue collection and about four weeks of production, the applications extend over about three months, within the two-year shelf life of the stored MSEC.
Does health insurance cover stroke stem cell therapy in Germany?
No. Health insurers do not ordinarily reimburse experimental MSEC treatment after a stroke, so you should plan to pay privately. Rehabilitation and stroke prevention remain covered as usual; for MSEC you can ask your insurer directly about an individual decision.
Should I stop my current stroke medication such as antiplatelet drugs, anticoagulants or statins?
No. The programme complements guideline-based care. Please continue to work with your treating neurologist throughout.
Should I continue my existing stroke treatment such as rehabilitation?
Yes. Physiotherapy, occupational and speech therapy and your medication continue as your doctors direct. MSEC is added to them and changes nothing unless your treating physician recommends a change.
How often do I need to travel to Germany for stroke stem cell treatment?
Usually about six times over about four months, if possible with a companion: once for about two days for bloodwork and tissue collection in Offenbach, less than 20 minutes from Frankfurt Airport, and then about five times for the applications. If you live close by, a single dose about once a week means more but shorter trips. The full sequence is described on the MSC secretome page.
What medical records should I send for a stroke assessment?
Please send us your most recent documents; we will ask if we need anything else. Helpful are, for example, your hospital discharge letters, the CT or MRI reports and images from the time of the stroke and afterwards, and reports from your rehabilitation. Results of heart rhythm monitoring, ultrasound of the neck arteries and echocardiography also help, as does a current medication list including blood thinners. Our patient care team will tell you how to send large image files.
Does ANOVA IRM treat international patients after a stroke?
Yes. After a stroke you can begin without leaving home: the first assessment takes place in English by phone or video, and a family member can take part.
step by step.
You are hereStroke: Clinical & Scientific Evidence
What happens in the brain during and after a stroke?
In an ischaemic stroke, a blocked artery cuts off the blood supply to a region of the brain. In its centre, the core, cells die within minutes. Around it lies the penumbra, tissue that is still alive but at risk; it can be saved if the blood flow is restored in time. In an untreated stroke of a large artery, about 1.9 million nerve cells are lost every minute.[11] In a haemorrhagic stroke, a ruptured vessel bleeds into the brain (intracerebral haemorrhage, ICH) or into the space around it (subarachnoid haemorrhage, SAH).[1]
Ischaemic strokes are grouped by their cause according to the TOAST classification.[3] It distinguishes large artery atherosclerosis, cardioembolism (most often from atrial fibrillation), small vessel occlusion (lacunar stroke), other determined causes and strokes of undetermined cause, also called cryptogenic strokes. Recovery is described in phases: hyperacute (first 24 hours), acute (up to seven days), early subacute (up to three months), late subacute (up to six months) and chronic (after six months).[4] Severity and outcome are measured with the NIH Stroke Scale (NIHSS), the modified Rankin Scale (mRS), the Barthel Index and, for arm and leg movement, the Fugl-Meyer Assessment.
What causes a stroke, and what are the risk factors?
Ischaemic strokes are caused by a clot from the heart, by narrowing of the large arteries supplying the brain or by disease of the small vessels deep in the brain. Intracerebral haemorrhages are most often caused by long-standing high blood pressure, subarachnoid haemorrhages by a ruptured aneurysm. What causes the stroke and what drives the damage afterwards are two different questions; the next section deals with the damage. In an international case-control study, ten modifiable risk factors together accounted for about 90% of the risk of stroke.[5]
- High blood pressure: the most important single risk factor.[1],[5]
- Heart disease: above all atrial fibrillation, which allows clots to form in the heart.
- Metabolic factors: high blood sugar and diabetes, high LDL cholesterol and obesity.[1]
- Lifestyle: smoking, physical inactivity, unhealthy diet, heavy alcohol consumption and psychosocial stress.[5]
- Environment: air pollution.[1]
- Age and history: the risk rises with age and after a previous stroke or TIA.
What drives the damage after a stroke?
The damage does not end when the stroke itself is over. Within hours, a cascade of excess glutamate (excitotoxicity), oxidative stress and cell death spreads from the core into the penumbra.[12] Over days to weeks, the brain’s own immune cells (microglia) and immune cells entering from the blood maintain inflammation, and the blood–brain barrier becomes leaky.[12] A glial scar forms around the damaged area. Over months, nerve cells can also be lost in brain regions connected to it (secondary neurodegeneration).[13]
At the same time, the brain reorganises: undamaged areas take over functions, and new connections form. This plasticity is greatest in the first weeks to months and is the basis of rehabilitation.[4],[14] This is where our programme aims — at the environment of the damaged tissue and the course of recovery, not at the cause of the stroke, and not at a cure.
What is the guideline-based standard of care for stroke?
Acute treatment follows guidelines such as those of the European Stroke Organisation (ESO) and the American Heart Association (AHA).[17],[18] The German guideline on acute ischaemic stroke expired in May 2026; a successor has not yet been published.[16] People with an acute stroke are treated on a specialised stroke unit. Within 4.5 hours of onset, the clot can be dissolved with alteplase or tenecteplase given into a vein (intravenous thrombolysis). In selected patients, for example after a stroke during sleep, this is possible later if imaging shows tissue that can still be saved.[18] A clot in a large artery can be removed with a catheter (mechanical thrombectomy), in selected patients up to 24 hours after onset.[18] After an intracerebral haemorrhage, the blood pressure is lowered, blood thinners are reversed and, in selected cases, surgery is performed.
Secondary prevention lowers the risk of a further stroke. It includes antiplatelet drugs such as aspirin or clopidogrel, oral anticoagulants in atrial fibrillation, statins and blood pressure treatment. For a narrowed neck artery, surgery or a stent can be added (carotid endarterectomy or stenting).[19] Rehabilitation with physiotherapy, occupational therapy and speech and language therapy supports recovery. In an external phase 3 trial, very early, high-dose mobilisation within 24 hours led to fewer favourable outcomes than usual care.[20]
These treatments limit the damage in the first hours and prevent further strokes, but none of them restores brain tissue that has already died. That gap is what research into cell-based approaches is exploring; MSEC does not replace standard care.

How is a stroke diagnosed, and what do we not do ourselves?
Stroke is diagnosed and treated in hospital, not by us. The emergency work-up includes CT with CT angiography and, where needed, CT perfusion, or MRI with diffusion-weighted imaging (DWI) and other sequences. The NIHSS scores the deficit. The search for the cause includes blood tests, an ECG and longer rhythm monitoring for atrial fibrillation, duplex ultrasound of the neck arteries and transthoracic or transoesophageal echocardiography.[19]
What we do ourselves is imaging: MRI of the brain with or without contrast, and CT guidance for an intrathecal application. This is carried out at the Prof. Dr. Stehling Institut für Bildgebende Diagnostik GmbH in the same building, which also belongs to Dr. Stehling. We do not perform emergency stroke care, heart rhythm monitoring, echocardiography or the neurological diagnosis itself; please bring these findings from your doctors. Anyone with acute stroke symptoms must call the emergency services.
What is the scientific rationale for MSEC after a stroke?
MSC secretome (MSEC)
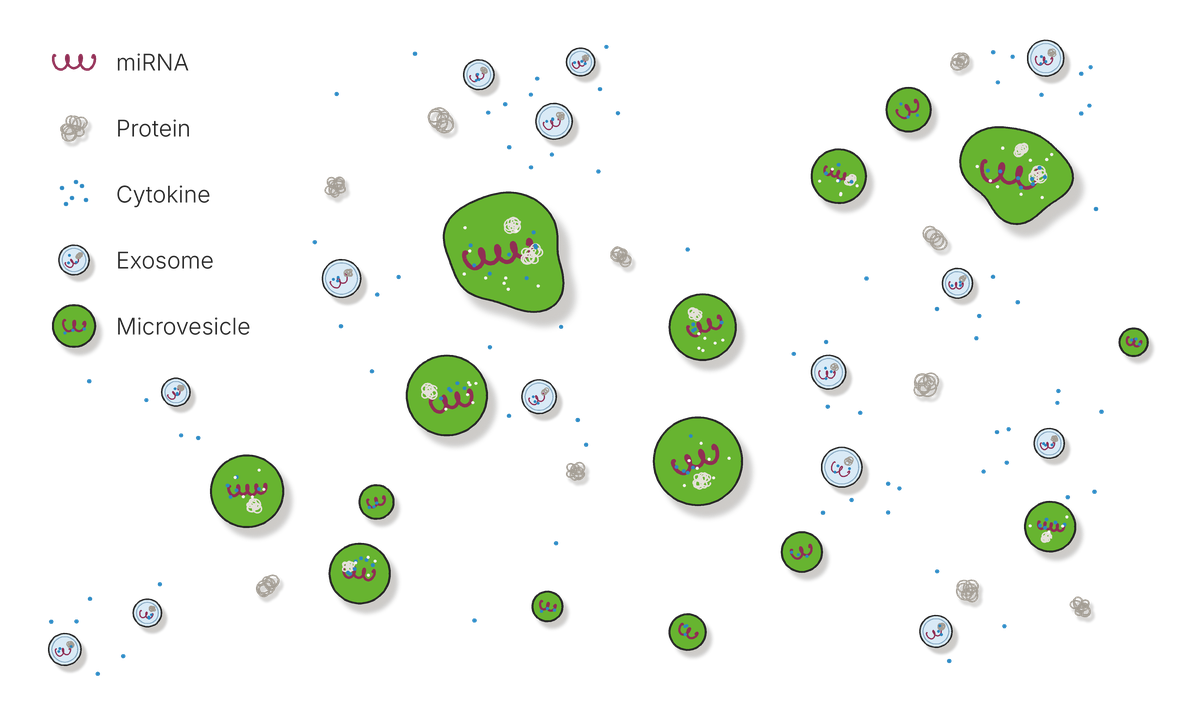
ANOVA IRM has not yet tested MSEC in a clinical study. MSEC is a mesenchymal stromal cell secretome: the growth factors, cytokines and extracellular vesicles released by these cells, without the cells themselves. Mesenchymal stem cells and mesenchymal stromal cells are two names for the same cells (MSC); the International Society for Cell & Gene Therapy recommends “stromal” for cells grown in the laboratory.[34],[35]
In an external animal study in rats after a stroke, exosomes from MSC given into a vein improved recovery of function and increased the growth of nerve fibres, new nerve cells and new blood vessels.[36] In a direct comparison in mice, extracellular vesicles from MSC were not inferior to the cells themselves; they protected brain tissue in the long term and improved motor coordination.[37] In rats with a stroke of the deep white matter, extracellular vesicles from fat-derived MSC, the cell source of MSEC, given into a vein improved function and the connectivity of nerve fibre tracts, even at a low dose.[41] Microvesicles from MSC also reduced inflammation and improved function in rats after a stroke; vesicles from MSC exposed to brain extract worked better.[42] An external systematic review of animal studies found smaller infarcts and better neurological scores after extracellular vesicles. It also found signs of publication bias, and few studies used animals with the accompanying diseases typical of stroke patients.[38]
Small external clinical studies have tested MSC and related cell products — cells, not secretome — after a stroke. In a small external randomised pilot study, five patients received their own bone marrow MSC into a vein. They managed everyday activities (Barthel Index) better at three and six months than 25 controls, but not at twelve months.[21] In a small external phase 1/2 study, donor MSC were given into a vein to 36 people in the chronic phase. There were no treatment-related serious adverse events, and everyday function improved over one year; there was no control group.[22] In a small external phase 1/2a study of 18 people with chronic stroke, modified MSC implanted into the brain were followed by improvements in movement scores, also without a control group.[23]
In the small external randomised phase 2 trial ISIS-HERMES, 31 people received their own bone marrow MSC into a vein in the subacute phase. Everyday function did not differ from the control group, but movement scores improved more.[29] In a small external randomised phase 2 trial, 32 people with lasting consequences of an ischaemic stroke received donor umbilical cord MSC twice, either into the cerebrospinal fluid or into a vein, alongside rehabilitation. There were no serious treatment-related adverse events. After twelve months both groups had improved more than 16 matched, non-randomised controls with rehabilitation alone. A direct comparison of the two routes showed no significant difference; minor side effects such as headache and pain at the puncture site were more frequent after intrathecal administration.[30] Two recent small external phase 1 studies with donor umbilical cord MSC given into a vein in the acute or subacute phase found no serious adverse events; they had no control group.[31],[32]
The external phase 2/3 trial TREASURE tested donor bone marrow progenitor cells (multipotent adult progenitor cells) in 206 patients in Japan, given 18 to 36 hours after an ischaemic stroke. A better outcome after 90 days could not yet be demonstrated.[26] In the small external randomised phase 2 trial MASTERS with the same cell product, the main goal could not yet be demonstrated either.[24] The same applies to the external phase 3 trial STARTING-2 with the patients’ own MSC in 54 patients.[25] A newer external meta-analysis of 17 randomised trials with 999 patients found slightly better independence and lower mortality, but no effect on the neurological deficit; the effect on disability did not hold up in all sensitivity analyses.[33] An earlier Cochrane review of seven small randomised trials found a small improvement in the neurological deficit, but no clear effect on independence in daily life; the certainty of this evidence is low.[27]
To our knowledge, the only external clinical study with cell-free MSC vesicles after a stroke is a small external pilot study in five patients. Exosomes injected into the brain caused no serious adverse events; the study examined safety only.[39] An external case report also describes one patient with an acute ischaemic stroke who received a secretome from donor amniotic membrane MSC into a vein for four weeks; the authors reported clinical improvement.[40] A single case does not allow conclusions about an effect. To our knowledge, no study has yet tested an MSC secretome given into the cerebrospinal fluid after a stroke.
What is the efficacy hypothesis behind MSC secretome after a stroke?
After a stroke, activated microglia, immune cells from the blood and a leaky blood–brain barrier maintain inflammation around the damaged area for weeks, and a glial scar forms around it.[12] The hypothesis is that the soluble factors of the mesenchymal stromal cell secretome, given into the cerebrospinal fluid, influence this environment. They may dampen the inflammation and support the growth of blood vessels and nerve connections, and with them the reorganisation that rehabilitation builds on.[36],[37]
Two limitations belong with it. Many treatments that protected the brain in animal models of stroke have not shown a benefit in patients.[15] And brain tissue that has already died is not expected to be replaced. Our aim is to influence the course of recovery, not to cure the stroke or its consequences.
Talk to us about current changes or additions to the programme. For a number of conditions ANOVA IRM also offers infusion therapies alongside the components described above.
Where does our own stroke evidence stand?
We do not currently publish our own outcome data for stroke. What we can say about MSEC after a stroke therefore rests on the published literature and on the rationale described above. Personal accounts from patients are collected in our testimonials; they are individual reports, not outcome data.
Stem cell-based therapy after a stroke remains experimental, and outcomes vary from patient to patient. Treatment goals are agreed individually and followed with clinical and functional measures, such as movement, speech, everyday activities and quality of life.
What is the realistic goal of stroke treatment?
After the acute phase, stroke care aims to regain as much function as possible through rehabilitation and to prevent a further stroke.[19] For MSEC, too, the aim is to influence the course of recovery, not to restore brain tissue that has died. Research into cell-based approaches continues, but a cure cannot be promised.
Legal framework for MSEC after a stroke
MSEC is an autologous tissue preparation, which ANOVA IRM manufactures from the patient’s own fat tissue under a collection (procurement) authorisation (Section 20b AMG) and a manufacturing authorisation under Section 20c AMG, granted in 2018 by the Darmstadt Regional Council, today the Hessian State Office for Health and Care (HLfGP), with the involvement of the Paul-Ehrlich-Institut; the HLfGP inspects the facility regularly. After a stroke, MSEC is given as an individual therapeutic attempt (individueller Heilversuch), which concerns the administration only and follows full disclosure and informed consent. Because the product is used only for ANOVA IRM’s own patients, no authorisation under Section 4b, no marketing authorisation under Section 21 and no approval under Section 21a AMG is required. The full derivation is on our regulatory status page.
Frequently asked questions — stroke, evidence and approval status
Is stem cell therapy approved for stroke anywhere?
No. To our knowledge, no stem cell therapy is approved for stroke anywhere; the US list of approved cell and gene therapies contains none for stroke.[43] In Japan, two cell products hold conditional, time-limited approvals for neighbouring conditions: spinal cord injury[44] and, according to the manufacturer, paralysis after traumatic brain injury[45]; neither is approved for stroke. At ANOVA IRM, MSEC is given after a stroke as an individual therapeutic attempt.
Are MSC studies evidence that MSEC works after a stroke?
No. Laboratory, animal and small clinical studies with MSC and related cell products give a rationale, not proof, and they tested cells rather than a secretome. In the external phase 2/3 trial TREASURE, a benefit of donor progenitor cells given after a stroke could not yet be demonstrated.[26] Proof would require a randomised controlled phase 3 trial with MSEC itself, and none exists yet. See the scientific rationale.
What type of stem cell therapy does ANOVA use for stroke?
ANOVA uses MSEC, an autologous mesenchymal stem cell secretome. It is produced in Offenbach from mesenchymal stromal cells grown from your own abdominal fat tissue and contains their signalling molecules, but no living cells. After a stroke it is given mainly into the cerebrospinal fluid; nothing is implanted into the brain.
Is it too late for stem cell therapy years after a stroke?
Not necessarily, but the evidence is limited. Most spontaneous recovery takes place in the first three months, yet the brain keeps some capacity to reorganise for much longer.[4],[14] Small external clinical studies with cell products have also included people months to years after their stroke[22],[23]; a benefit has not been proven by clinical studies. ANOVA IRM also treats people long after a stroke, but we recommend starting as soon as possible. Whether treatment makes sense in your case is assessed individually.
How common is stroke?
Very common. In 2021 there were about 11.9 million new strokes worldwide, and 93.8 million people were living after a stroke.[1] With 7.3 million deaths, stroke was the third most common cause of death worldwide, after ischaemic heart disease and COVID-19.[1] In Germany, about 270,000 strokes occur every year, almost 200,000 of them first strokes, and about 1.8 million people live with the consequences.[2] The risk rises with age, but since 2015 strokes have become more frequent in people under 70.[1]
What are the symptoms of stroke?
The symptoms of a stroke begin suddenly and depend on which part of the brain is affected. Every sudden symptom of this kind is an emergency, even if it disappears again.
Warning signs (BE FAST)
- Balance: sudden dizziness, loss of balance or coordination
- Eyes: sudden loss of vision in one eye, double vision or loss of half of the visual field
- Face: one side of the face droops
- Arm: sudden weakness or numbness of an arm or leg, usually on one side
- Speech: slurred speech, difficulty finding words or understanding
- Time: call the emergency services immediately
Lasting consequences
- paralysis or weakness on one side of the body (hemiparesis) and muscle stiffness (spasticity)
- language disorders (aphasia) and slurred speech (dysarthria)
- swallowing difficulties (dysphagia)
- problems with memory, attention and planning
- visual field loss and neglect of one side of the body
- fatigue, depression and anxiety
Which forms of stroke are there, and how does it progress?
Strokes are divided into ischaemic and haemorrhagic forms, and their course into an acute, a subacute and a chronic phase.[1],[4]
- Ischaemic stroke: about 65% of new strokes worldwide; a clot blocks an artery. By cause, the TOAST classification distinguishes large artery atherosclerosis, cardioembolism, small vessel occlusion (lacunar stroke), other causes and cryptogenic stroke.[1],[3]
- Intracerebral haemorrhage (ICH): about 29% of new strokes; a vessel bleeds into the brain tissue.[1]
- Subarachnoid haemorrhage (SAH): about 6% of new strokes; bleeding into the space around the brain, often from a ruptured aneurysm.[1]
- Transient ischaemic attack (TIA): stroke symptoms that disappear completely; it signals a high risk of a stroke in the following days and needs urgent assessment.
How a stroke progresses
- Hyperacute and acute phase (first seven days): the damaged area is defined, and complications such as brain swelling can occur.[4]
- Early subacute phase (up to three months): the period of greatest plasticity, in which most spontaneous recovery takes place.[4],[14]
- Late subacute and chronic phase (from three and six months): improvement continues more slowly, mainly through training and rehabilitation.[4]
- Risk of a further stroke: in German insurance data, 7.4% of patients had a further stroke within one year and 19.4% within five years.[6]
What complications can a stroke cause?
Many people live with complications after a stroke, and several of them can be treated. They depend on the size and location of the damaged area.
- Spasticity: muscle stiffness in about a quarter of patients, and in about 40% of those left with paralysis after a first stroke.[9]
- Swallowing problems (dysphagia): in about half of patients on clinical testing, with a roughly threefold risk of pneumonia.[8]
- Depression: in about one in three people after a stroke.[7]
- Dementia: about one in ten people develop dementia soon after a first stroke, and more than a third after a recurrent stroke.[10]
- Further complications: epileptic seizures, falls, pain, fatigue and a further stroke.
Important Pages
Questions people usually ask next. Each is answered in full on its own page.
- Who are we?
- Is ANOVA legal?
- Is stem cell therapy safe?
- What is MSC secretome (MSEC)?
- What is BMC (Bone Marrow Concentrate)?
- What are stem cells?
- What should I ask when looking for a stem cell treatment?
- Which conditions do we treat?
- Neurological and neurodegenerative diseases — overview
- Benefit-risk assessment of intrathecal administration
- Does the secretome pass the blood–brain barrier?
Affiliations of ANOVA
ANOVA IRM shares its premises in Offenbach with two further institutions owned by Dr. Stehling: the Institut für Bildgebende Diagnostik (IBDO), providing MRI and CT imaging, and the VITUS PRIVATKLINIK Prof. Dr. Stehling GmbH. Because imaging is carried out in the same building, condition-specific diagnostics — including MRI of the brain and CT guidance for intrathecal applications after a stroke — can be performed in-house rather than referred elsewhere. See diagnostics at ANOVA IRM.
References — stroke literature
Literature specific to stroke is listed here. General literature on MSC, secretome and extracellular vesicles is maintained on the MSC secretome page.
Stroke — frequency, forms and course
- [1] GBD 2021 Stroke Risk Factor Collaborators. Global, regional, and national burden of stroke and its risk factors, 1990–2021: a systematic analysis for the Global Burden of Disease Study 2021. Lancet Neurol. 2024;23(10):973–1003. doi:10.1016/S1474-4422(24)00369-7. PMID: 39304265.
- [2] Deutsche Schlaganfall-Gesellschaft. Factsheet Schlaganfall. 25 August 2025. Accessed 21 October 2026. https://www.dsg-info.de/wp-content/uploads/2025/09/250825_Factsheet_Schlaganfall.pdf
- [3] Adams HP Jr, Bendixen BH, Kappelle LJ, et al. Classification of subtype of acute ischemic stroke. Definitions for use in a multicenter clinical trial. TOAST. Trial of Org 10172 in Acute Stroke Treatment. Stroke. 1993;24(1):35–41. doi:10.1161/01.str.24.1.35. PMID: 7678184.
- [4] Bernhardt J, Hayward KS, Kwakkel G, et al. Agreed definitions and a shared vision for new standards in stroke recovery research: the Stroke Recovery and Rehabilitation Roundtable taskforce. Int J Stroke. 2017;12(5):444–450. doi:10.1177/1747493017711816. PMID: 28697708.
- [5] O’Donnell MJ, Chin SL, Rangarajan S, et al. Global and regional effects of potentially modifiable risk factors associated with acute stroke in 32 countries (INTERSTROKE): a case-control study. Lancet. 2016;388(10046):761–775. doi:10.1016/S0140-6736(16)30506-2. PMID: 27431356.
- [6] Stahmeyer JT, Stubenrauch S, Geyer S, et al. The frequency and timing of recurrent stroke: an analysis of routine health insurance data. Dtsch Arztebl Int. 2019;116(42):711–717. doi:10.3238/arztebl.2019.0711. PMID: 31711561.
- [7] Hackett ML, Pickles K. Part I: frequency of depression after stroke: an updated systematic review and meta-analysis of observational studies. Int J Stroke. 2014;9(8):1017–1025. doi:10.1111/ijs.12357. PMID: 25117911.
- [8] Martino R, Foley N, Bhogal S, et al. Dysphagia after stroke: incidence, diagnosis, and pulmonary complications. Stroke. 2005;36(12):2756–2763. doi:10.1161/01.STR.0000190056.76543.eb. PMID: 16269630.
- [9] Zeng H, Chen J, Guo Y, et al. Prevalence and risk factors for spasticity after stroke: a systematic review and meta-analysis. Front Neurol. 2020;11:616097. doi:10.3389/fneur.2020.616097. PMID: 33551975.
- [10] Pendlebury ST, Rothwell PM. Prevalence, incidence, and factors associated with pre-stroke and post-stroke dementia: a systematic review and meta-analysis. Lancet Neurol. 2009;8(11):1006–1018. doi:10.1016/S1474-4422(09)70236-4. PMID: 19782001.
Disease mechanisms and recovery
- [11] Saver JL. Time is brain — quantified. Stroke. 2006;37(1):263–266. doi:10.1161/01.STR.0000196957.55928.ab. PMID: 16339467.
- [12] Iadecola C, Anrather J. The immunology of stroke: from mechanisms to translation. Nat Med. 2011;17(7):796–808. doi:10.1038/nm.2399. PMID: 21738161.
- [13] Ong LK. Beyond the primary infarction: focus on mechanisms related to secondary neurodegeneration after stroke. Int J Mol Sci. 2022;23(24):16024. doi:10.3390/ijms232416024. PMID: 36555665.
- [14] Murphy TH, Corbett D. Plasticity during stroke recovery: from synapse to behaviour. Nat Rev Neurosci. 2009;10(12):861–872. doi:10.1038/nrn2735. PMID: 19888284.
- [15] O’Collins VE, Macleod MR, Donnan GA, et al. 1,026 experimental treatments in acute stroke. Ann Neurol. 2006;59(3):467–477. doi:10.1002/ana.20741. PMID: 16453316.
Standard of care
- [16] Ringleb P, Köhrmann M, Jansen O, et al. Akuttherapie des ischämischen Schlaganfalls, S2e-Leitlinie, 2022. In: Deutsche Gesellschaft für Neurologie (Hrsg.), Leitlinien für Diagnostik und Therapie in der Neurologie. AWMF-Registernummer 030-046. Validity extended until 9 May 2026; listed as expired in the AWMF register (accessed 29 October 2026). https://register.awmf.org/de/leitlinien/detail/030-046
- [17] Berge E, Whiteley W, Audebert H, et al. European Stroke Organisation (ESO) guidelines on intravenous thrombolysis for acute ischaemic stroke. Eur Stroke J. 2021;6(1):I–LXII. doi:10.1177/2396987321989865. PMID: 33817340.
- [18] Prabhakaran S, Gonzalez NR, Zachrison KS, et al. 2026 Guideline for the early management of patients with acute ischemic stroke: a guideline from the American Heart Association/American Stroke Association. Stroke. 2026;57(8):e316–e436. doi:10.1161/STR.0000000000000513. PMID: 41582814.
- [19] Kleindorfer DO, Towfighi A, Chaturvedi S, et al. 2021 Guideline for the prevention of stroke in patients with stroke and transient ischemic attack: a guideline from the American Heart Association/American Stroke Association. Stroke. 2021;52(7):e364–e467. doi:10.1161/STR.0000000000000375. PMID: 34024117.
- [20] AVERT Trial Collaboration group. Efficacy and safety of very early mobilisation within 24 h of stroke onset (AVERT): a randomised controlled trial. Lancet. 2015;386(9988):46–55. doi:10.1016/S0140-6736(15)60690-0. PMID: 25892679.
Mesenchymal stem cells and other cell products after stroke — clinical studies (other products than MSEC)
- [21] Bang OY, Lee JS, Lee PH, et al. Autologous mesenchymal stem cell transplantation in stroke patients. Ann Neurol. 2005;57(6):874–882. doi:10.1002/ana.20501. PMID: 15929052.
- [22] Levy ML, Crawford JR, Dib N, et al. Phase I/II study of safety and preliminary efficacy of intravenous allogeneic mesenchymal stem cells in chronic stroke. Stroke. 2019;50(10):2835–2841. doi:10.1161/STROKEAHA.119.026318. PMID: 31495331.
- [23] Steinberg GK, Kondziolka D, Wechsler LR, et al. Clinical outcomes of transplanted modified bone marrow-derived mesenchymal stem cells in stroke: a phase 1/2a study. Stroke. 2016;47(7):1817–1824. doi:10.1161/STROKEAHA.116.012995. PMID: 27256670 (industry-sponsored).
- [24] Hess DC, Wechsler LR, Clark WM, et al. Safety and efficacy of multipotent adult progenitor cells in acute ischaemic stroke (MASTERS): a randomised, double-blind, placebo-controlled, phase 2 trial. Lancet Neurol. 2017;16(5):360–368. doi:10.1016/S1474-4422(17)30046-7. PMID: 28320635.
- [25] Chung JW, Chang WH, Bang OY, et al. Efficacy and safety of intravenous mesenchymal stem cells for ischemic stroke. Neurology. 2021;96(7):e1012–e1023. doi:10.1212/WNL.0000000000011440. PMID: 33472925. (phase 3; NCT01716481)
- [26] Houkin K, Osanai T, Uchiyama S, et al. Allogeneic stem cell therapy for acute ischemic stroke: the phase 2/3 TREASURE randomized clinical trial. JAMA Neurol. 2024;81(2):154–162. doi:10.1001/jamaneurol.2023.5200. PMID: 38227308.
- [27] Boncoraglio GB, Ranieri M, Bersano A, et al. Stem cell transplantation for ischemic stroke. Cochrane Database Syst Rev. 2019;5(5):CD007231. doi:10.1002/14651858.CD007231.pub3. PMID: 31055832.
- [28] Kvistad CE, Kråkenes T, Gjerde C, et al. Safety and clinical efficacy of mesenchymal stem cell treatment in traumatic spinal cord injury, multiple sclerosis and ischemic stroke — a systematic review and meta-analysis. Front Neurol. 2022;13:891514. doi:10.3389/fneur.2022.891514. PMID: 35711260.
- [29] Jaillard A, Hommel M, Moisan A, et al. Autologous mesenchymal stem cells improve motor recovery in subacute ischemic stroke: a randomized clinical trial. Transl Stroke Res. 2020;11(5):910–923. doi:10.1007/s12975-020-00787-z. PMID: 32462427.
- [30] Nguyen LT, Nguyen TTN, Nguyen KT, et al. Intrathecal versus intravenous umbilical cord mesenchymal stem cells for ischemic stroke sequelae. Stem Cells Transl Med. 2025;14(12):szaf063. doi:10.1093/stcltm/szaf063. PMID: 41277536.
- [31] Cui L, Xiao M, Zhang Q, et al. Intravenous human umbilical cord-derived mesenchymal stem cell transplantation for ischemic stroke (MERIT): a phase 1 trial. Cell Rep Med. 2026;7(6):102836. doi:10.1016/j.xcrm.2026.102836. PMID: 42208543. (industry-affiliated)
- [32] Chan L, Chen JH, Hong CT, et al. A phase I, open-label, dose-escalation study to evaluate the safety and tolerability of intravenous UMC119-06 in patients with acute ischemic stroke. Int J Med Sci. 2026;23(2):576–584. doi:10.7150/ijms.124255. PMID: 41583506.
- [33] de Wilde D, Saemann A, Guzman R. Efficacy and safety of stem cell therapy in ischemic stroke patients: a systematic review and meta-analysis of randomised controlled trials. Stroke Vasc Neurol. 2026;11(5):539–553. doi:10.1136/svn-2025-004796. PMID: 41617224.
Mesenchymal stromal cell secretome and extracellular vesicles
- [34] Dominici M, Le Blanc K, Mueller I, et al. Minimal criteria for defining multipotent mesenchymal stromal cells. The International Society for Cellular Therapy position statement. Cytotherapy. 2006;8(4):315–317. doi:10.1080/14653240600855905. PMID: 16923606.
- [35] Viswanathan S, Shi Y, Galipeau J, et al. Mesenchymal stem versus stromal cells: International Society for Cell & Gene Therapy (ISCT®) Mesenchymal Stromal Cell committee position statement on nomenclature. Cytotherapy. 2019;21(10):1019–1024. doi:10.1016/j.jcyt.2019.08.002. PMID: 31526643.
- [36] Xin H, Li Y, Cui Y, et al. Systemic administration of exosomes released from mesenchymal stromal cells promote functional recovery and neurovascular plasticity after stroke in rats. J Cereb Blood Flow Metab. 2013;33(11):1711–1715. doi:10.1038/jcbfm.2013.152. PMID: 23963371.
- [37] Doeppner TR, Herz J, Görgens A, et al. Extracellular vesicles improve post-stroke neuroregeneration and prevent postischemic immunosuppression. Stem Cells Transl Med. 2015;4(10):1131–1143. doi:10.5966/sctm.2015-0078. PMID: 26339036.
- [38] Thomas JM, Cunningham CJ, Lawrence CB, et al. Therapeutic potential of extracellular vesicles in preclinical stroke models: a systematic review and meta-analysis. BMJ Open Sci. 2020;4(1):e100047. doi:10.1136/bmjos-2019-100047. PMID: 35047689.
- [39] Dehghani L, Khojasteh A, Soleimani M, et al. Safety of intraparenchymal injection of allogenic placenta mesenchymal stem cells derived exosome in patients undergoing decompressive craniectomy following malignant middle cerebral artery infarct, a pilot randomized clinical trial. Int J Prev Med. 2022;13:7. doi:10.4103/ijpvm.ijpvm_441_21. PMID: 35281985.
- [40] Lin FH, Yang YX, Wang YJ, et al. Amniotic membrane mesenchymal stromal cell-derived secretome in the treatment of acute ischemic stroke: a case report. World J Clin Cases. 2023;11(27):6543–6550. doi:10.12998/wjcc.v11.i27.6543. PMID: 37900223.
- [41] Otero-Ortega L, Laso-García F, Frutos MCG, et al. Low dose of extracellular vesicles identified that promote recovery after ischemic stroke. Stem Cell Res Ther. 2020;11(1):70. doi:10.1186/s13287-020-01601-1. PMID: 32075692.
- [42] Lee JY, Kim E, Choi SM, et al. Microvesicles from brain-extract-treated mesenchymal stem cells improve neurological functions in a rat model of ischemic stroke. Sci Rep. 2016;6:33038. doi:10.1038/srep33038. PMID: 27609711.
Approval status
- [43] U.S. Food and Drug Administration. Approved Cellular and Gene Therapy Products. Updated 17 September 2026. Accessed 21 October 2026. https://www.fda.gov/vaccines-blood-biologics/cellular-gene-therapy-products/approved-cellular-and-gene-therapy-products
- [44] Cyranoski D. Japan’s approval of stem-cell treatment for spinal-cord injury concerns scientists. Nature. 2019;565(7741):544–545. doi:10.1038/d41586-019-00178-x. PMID: 30696963.
- [45] SanBio Co., Ltd. Press release on AKUUGO (vandefitemcel), conditional and time-limited approval in Japan for chronic motor paralysis after traumatic brain injury (31 July 2024). February 2025. Accessed 21 October 2026. https://sanbio.com/wp/wp-content/uploads/2025/02/PR_EN.pdf
Patient Services at ANOVA Institute for Regenerative Medicine
- Located in the center of Germany, quick access by car or train from anywhere in Europe
- Simple access worldwide, less than 20 minutes from Frankfurt Airport
- Individualized therapy with state-of-the-art autologous stem cell products
- Individually planned diagnostic work-up which include world-class MRI and CT scans
- German high quality standard on safety and quality assurance
- Personal service with friendly, dedicated Patient Care Managers
- Continuous analysis of scientific data in the field of regenerative medicine