

Translational Medicine — Works in Progress
The ANOVA Lyme Disease Stem Cell Treatment Programme Germany
An individualised treatment programme with autologous bone marrow concentrate (BMC) or cell-free MSC secretome (MSEC) for adults with Lyme disease, also known as Lyme borreliosis, including persistent symptoms after treatment (post-treatment Lyme disease syndrome, PTLDS). The product is chosen case by case. Offenbach, Germany. Experimental — fully legal — manufactured under German regulatory authorisation and official inspection since 2018.
You have tried a lot. Perhaps you have been told there is nothing more to be done. We listen first, examine thoroughly, and then tell you honestly whether a stem cell-based therapy, one of our programmes or another option could be right for you. Each option is discussed as an addition to your current treatment, never as a replacement.
| Component | Detail |
|---|---|
| Two products | Bone Marrow Concentrate (BMC) and Mesenchymal Stem Cell Secretome (MSEC), each manufactured under official authorisation; no marketing authorisation (experimental) |
| Authorisations | BMC § 20b / § 13 AMG · MSEC § 20b / § 20c AMG (German Medicines Act) |
| Location | Offenbach am Main, Germany |

Lyme disease in brief, the programme and its components — the essentials at a glance.
You are hereIntroduction & Summary
What is Lyme disease, in brief?
Lyme disease, or Lyme borreliosis, is an infection with bacteria of the Borrelia burgdorferi group. It is transmitted by the bite of an infected tick.[1] Doctors distinguish three forms. Early localised Lyme disease affects the skin around the bite; early disseminated Lyme disease can reach the nerves, the heart or other skin areas; late Lyme disease mainly affects the joints, months after the bite.[1]
A typical skin rash is diagnosed by its appearance; otherwise the diagnosis rests on symptoms, a blood test for antibodies and, if the nerves are affected, a test of the spinal fluid.[7],[8],[9] Antibiotics cure the infection in most people.[7] Some people keep symptoms after treatment, a condition called post-treatment Lyme disease syndrome (PTLDS) and sometimes described as “chronic Lyme”.[5],[6] For PTLDS, no cure is known to date.
Common symptoms include an expanding red rash around the bite (erythema migrans), tiredness, fever, headache, nerve pain, facial palsy and swollen knees.
More details can be found below in our scientific section on Lyme disease.
What is the ANOVA Lyme disease programme?
ANOVA offers autologous bone marrow concentrate (BMC) or mesenchymal stem cell secretome (MSEC) for adults with Lyme disease; the product is chosen case by case. The programme combines a review of your diagnosis and previous treatment with BMC or MSEC, given into a vein or, for joint problems, into the joint. Each component is selected individually; the programme is not a fixed package.
Stem cells are thought to act mainly through soluble factors, together called the secretome, which includes exosomes and many other factors. In some people, an inflammatory reaction in the joints or the nervous system continues after the bacteria have been treated.[12],[14] BMC and MSEC are intended to potentially influence this persisting inflammation; they are not intended to fight the bacteria.
ANOVA IRM has not yet tested BMC or MSEC for Lyme disease in a clinical study. The current state of research is described in the clinical and scientific section below.

The ANOVA Lyme Disease Programme — Components
Review of diagnosis and previous treatment
Before any application, we review how your Lyme disease was diagnosed and which treatment you have received so far; previous antibiotic treatment is not a requirement. We also look for other causes of your symptoms and for signs of an active infection, which your doctor assesses individually. Neither BMC nor MSEC is a substitute for antibiotics.
Bone marrow concentrate (BMC)
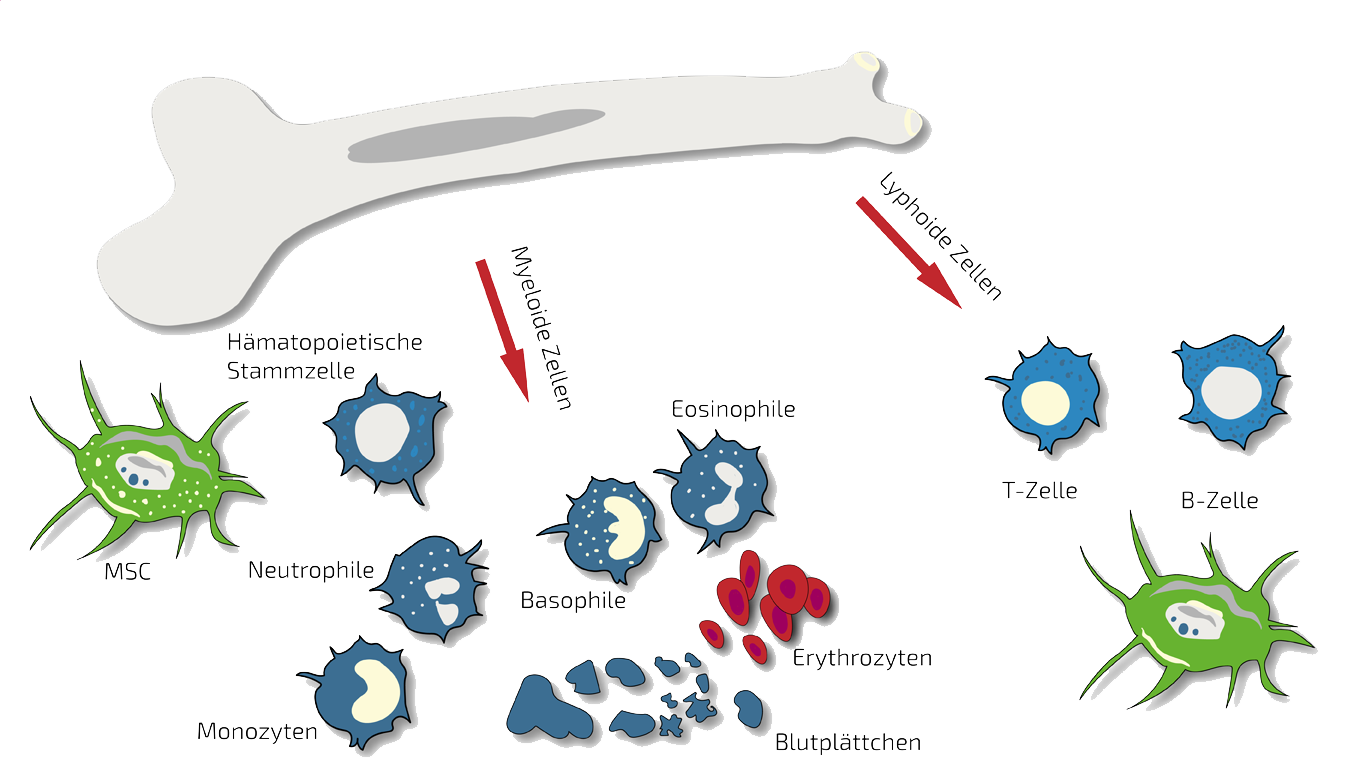
BMC is made from your own bone marrow and contains haematopoietic and mesenchymal stem cells in their natural composition. Bone marrow is collected from the pelvic bone (iliac crest) under brief sedation, concentrated, tested and given on the same day, during a two-day visit: into a vein or, for joint problems, into the joint. The current state of research is set out in the clinical and scientific section below.
MSC secretome (MSEC)
MSEC is the cell-free mixture of signalling molecules released by your own mesenchymal stromal cells from fat tissue, given as an infusion into a vein or, for joint problems, into the joint. In an external animal study of Lyme arthritis, mesenchymal stem cells injected into the joint reduced joint swelling and inflammation without increasing the number of bacteria.[17] These were donor cells, not secretome; the details are summarised in the clinical and scientific section below.
Antibiotics, physiotherapy, pain treatment and the care of your neurologist, rheumatologist or GP are not part of our programme; they continue at home.
Which diagnostics do we use for Lyme disease at ANOVA IRM?
Which tests are used to diagnose Lyme disease?
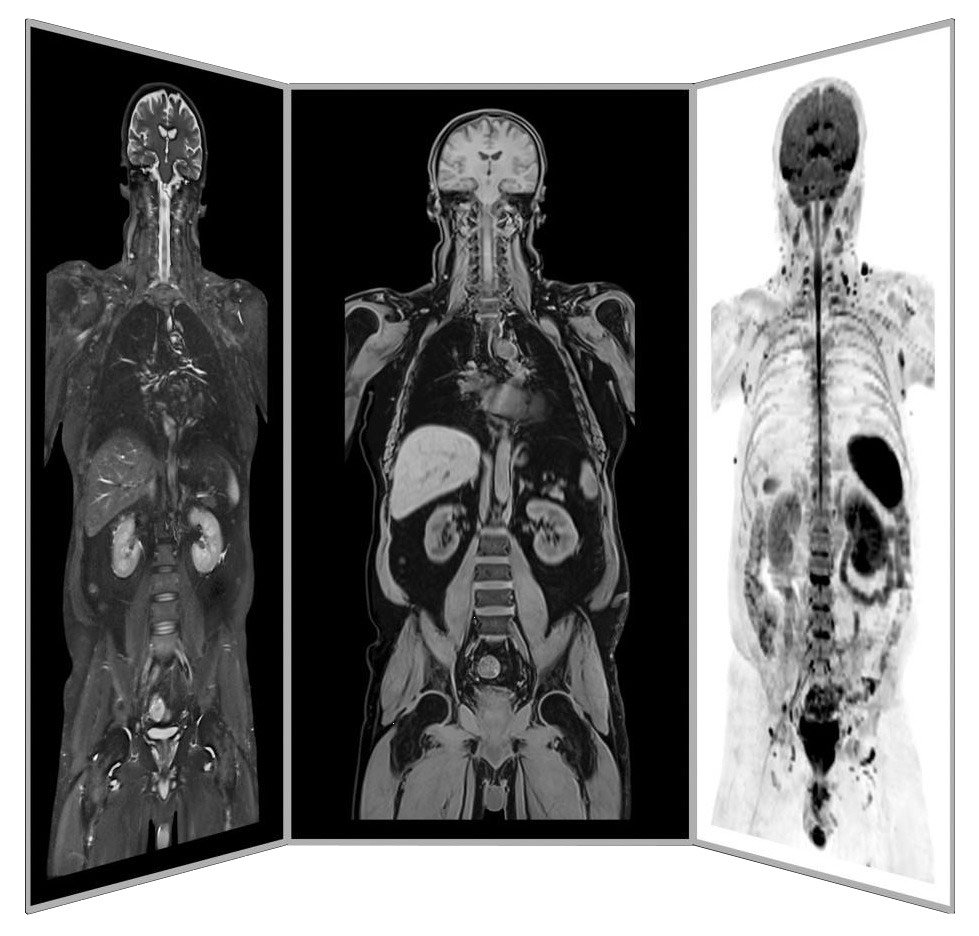
A typical erythema migrans is diagnosed by its appearance alone, without a blood test.[9] In all other forms, a two-step blood test looks for antibodies against Borrelia: a screening test (ELISA) followed by a confirmatory test (immunoblot).[7] If the nerves are affected, a lumbar puncture shows inflammation in the spinal fluid and antibodies produced there.[8] Lyme arthritis can be confirmed by testing joint fluid for bacterial DNA (PCR). An MRI with contrast of the head, spine or joint helps to exclude other causes.
What do we review before Lyme disease treatment at ANOVA IRM?
Before any treatment decision we review how your Lyme disease was diagnosed, including blood and spinal fluid results, and which treatment you have received so far, including any antibiotics. We ask which symptoms you have and since when, and which other causes have been looked for. We check your heart rhythm with an ECG if your heart was affected, and check that you are fit for the brief sedation required for tissue collection.
With BMC:
- Standard: no MRI required.
- Optional: an MRI with contrast of an affected joint, to show inflammation before an injection into the joint.
- Optional: CT guidance at ANOVA IRM for an injection into a joint that is hard to reach.
With MSEC:
- Standard: an MRI of the abdominal wall to exclude a hernia is required before the liposuction, taken no more than four weeks beforehand. It can be done at home or at ANOVA IRM.
- Optional: further MRI scans, with or without contrast, where your Lyme disease situation calls for them — for example of an affected knee or of the spine after neuroborreliosis.
Imaging can be carried out in-house; all examinations can also be done by your own doctors. The full diagnostic pathway is described on our diagnostics page.
Why ANOVA IRM for Lyme disease?
We make BMC and MSEC ourselves in Offenbach, in-house since 2018 (see our regulatory status). Imaging, the review of your previous findings and the applications, including CT-guided injections into a joint, take place in one building. Your treating physicians at home remain the basis of your care.
What can you expect as a patient with Lyme disease?
You can start with a remote assessment, by phone or video, so no journey to Germany is needed at first. Treatment itself takes place in person in Offenbach am Main, less than 20 minutes from Frankfurt Airport. Before you decide, you receive an individual written cost estimate; the services of our patient care team are free of charge. If you would like your existing findings reviewed independently, we also offer a second opinion.
Quick answers
Is there a cure for Lyme disease?
Yes, for the infection itself in most cases. Antibiotics such as doxycycline, amoxicillin or ceftriaxone clear the bacteria, and early treatment usually prevents later stages.[7],[8] For symptoms that persist after treatment (PTLDS), no cure is known; longer antibiotic courses did not help in external randomised trials.[10],[11] Experimental approaches such as bone marrow concentrate (BMC) or mesenchymal stem cell secretome (MSEC) are being explored for this situation.
Is Lyme disease stem cell therapy legal in Germany?
Yes, if the products are made under the required official authorisations. ANOVA IRM produces BMC under a collection (procurement) authorisation (Section 20b AMG) and a manufacturing authorisation under Section 13 AMG, and MSEC under Section 20b and a manufacturing authorisation under Section 20c AMG. The authorisations were granted by the Darmstadt Regional Council, today the Hessian State Office for Health and Care (HLfGP), with the involvement of the Paul-Ehrlich-Institut; the HLfGP inspects the facility regularly. For Lyme disease, BMC or MSEC is given as an individual therapeutic attempt (individueller Heilversuch). Our regulatory status page explains the legal basis.
Is Lyme disease stem cell therapy safe?
Not without qualification. Like any medical treatment, it carries risks from tissue collection, brief sedation and the application itself, into a vein or into a joint, which your doctor explains before treatment. Because BMC and MSEC may influence immune activity, your doctor checks for an active infection and decides individually whether it must be treated first.
An official authorisation for manufacturing provides an additional safeguard. The competent authority inspects the facility every two years and must be informed of every change to the process and every new material. Providers without such an authorisation are not subject to this oversight.
Dr. mult. Stehling and ANOVA IRM have manufactured MSEC with the same process since 2016, under an authorisation according to Section 20c AMG since 2018, and have treated 355 people with it (as of October 2026). They have manufactured BMC with the same process since 2012. After a pause from 2017 because of a change in German law, they have made it again since 2019 under an authorisation according to Section 13 AMG and have treated 153 people with it. To date, no serious adverse event has been caused by the product. Long-term data are not yet available. In clinical research, safety is first examined in phase 1/2 studies with roughly 10 to 100 patients. ANOVA IRM has not conducted such a study, but the number of people treated is well above that. Ask any provider for its authorisations; what regulators warn about is summarised under unproven therapies.
What medication is used for Lyme disease?
Antibiotics: doxycycline or amoxicillin by mouth for the skin rash, doxycycline by mouth or ceftriaxone into a vein when the nerves are affected, and a four-week course for Lyme arthritis.[7],[8],[9] If arthritis continues after antibiotics, anti-inflammatory drugs such as methotrexate may be added.[7],[12] Bone marrow concentrate (BMC) or MSC secretome (MSEC) at ANOVA IRM does not replace this treatment.
Who qualifies, what the process actually involves, and what it costs — step by step.
You are hereLyme Disease Treatment: Eligibility, Process & Cost
In this section you will find everything about treatment for Lyme disease (Lyme borreliosis) at ANOVA IRM, including persistent symptoms after treatment: who is eligible, the process step by step and the cost.
What does the Lyme disease treatment timeline look like?
- 01
Initial evaluation
Remote, by phone or video — typically 2 weeks to a few months
- 02
Preliminary screening
In your home country, to avoid an unnecessary journey
- 03
- 04
Production and quality control
With BMC: on the day of collection, given the same day. With MSEC: approximately 4 weeks; yields 10 doses
- 05
Storage
With MSEC: up to 2 years, allowing an extended personalised schedule. BMC is not stored
- 06
Application schedule
With BMC: one application on the day of collection. With MSEC: set individually: one dose every 4–6 weeks, or two doses every 3 months
Who qualifies for Lyme disease treatment, and what are the requirements?
We consider adults with Lyme disease (Lyme borreliosis) whose symptoms affect daily life. This includes post-treatment Lyme disease syndrome (PTLDS) with fatigue, pain or problems with concentration, and symptoms described as chronic Lyme disease. It also includes nerve damage after Lyme neuroborreliosis and Lyme arthritis with joint problems, for which BMC or MSEC can be given into the joint. There is no minimum duration of symptoms, and previous antibiotic treatment is not a requirement. Other causes of your symptoms should have been examined. You need to be well enough for brief sedation for tissue collection and able to travel to Offenbach, with MSEC for repeated applications. Every treatment recommendation follows a full clinical evaluation in which the treating physician weighs benefit and risk. Applying for an evaluation does not mean that treatment will be offered.
What are the contraindications for Lyme disease treatment?
Our treatments are experimental. We treat only people for whom, after medical assessment, we consider the benefit-risk balance to support treatment.
Applies to all ANOVA treatments:
- Active cancer within the last two years
- Under the age of legal majority
- Pregnancy or breastfeeding
- Active infectious disease (hepatitis A, B, C, HIV, syphilis or other)
Specific to Lyme disease:
- Lyme carditis with a disturbance of the heart rhythm that has not yet resolved
- Another untreated tick-borne infection
- Infection of a joint, or of the skin at the injection site or at the site of bone marrow or fat collection
Previous antibiotic treatment is not a requirement, and there is no minimum interval after the last antibiotic dose.
What does Lyme disease therapy at ANOVA IRM involve, step by step?
What screening is needed before you travel for Lyme disease treatment?
A preliminary screening in your home country helps you avoid an unnecessary journey. It usually consists of a blood test for HIV, hepatitis A, B or C, syphilis and other active infections. Together with your Lyme disease test results and the record of your previous treatment, it shows early whether medical factors would rule out treatment.
What happens at your first visit to Offenbach for Lyme disease?
The first treatment visit takes about two days in Offenbach and is outpatient. On the first day, bloodwork is repeated at ANOVA IRM as German medical rules require. The physician then completes the final assessment, including a check for signs of active infection and your fitness for sedation. With BMC, bone marrow is taken from the pelvic bone on day two under brief sedation and given the same day, into a vein or into the affected joint. With MSEC, a small amount of abdominal fat tissue is collected on day two by mini-liposuction under brief sedation; the first secretome application usually follows four to six weeks later.
How are your BMC and MSEC for Lyme disease produced and quality-controlled?
BMC: BMC is prepared on the day of collection in our own facility, under a manufacturing authorisation (Section 13 AMG) and good manufacturing practice (GMP). The bone marrow is concentrated but not multiplied and is not frozen; key quality tests are completed before it is given.
MSEC: In our own facility in Offenbach, mesenchymal stromal cells are isolated from the collected fat tissue and expanded. This takes place under official authorisation and officially inspected good professional practice (GFP, gute fachliche Praxis; similar to Good Tissue Practice, GTP, in the US, but more than GTP). From these cells we obtain your MSEC — the signalling molecules they release, not the living cells. Production and quality control take approximately four weeks and yield 10 doses per production cycle. Every patient batch is tested with methods validated according to the European Pharmacopoeia (Ph. Eur.) and GMP and released under a documented procedure. The released secretome is stored at −80 °C and keeps for up to two years.
How are BMC and MSEC applied for Lyme disease?
Persistent symptoms after Lyme disease can last for months or years, and there is currently no cure for them. With MSEC, we therefore recommend a longer-term treatment using all 10 doses produced rather than a single application; see the timeline above.
The schedule is set individually for each patient, for example:
- With BMC: one application on the day of bone marrow collection, into a vein or, for joint problems, into the affected joint, with CT guidance where needed; a repeat requires a new collection.
- With MSEC, at the start: two doses.
- If you live close by: a single MSEC dose every 4 to 6 weeks.
- If you live further away: a double dose every 3 months.
- Route for Lyme disease: an infusion into a vein, under medical supervision in Offenbach. The symptoms often involve several parts of the body, and an infusion is intended to reach joints, nerves and other tissues alike through the bloodstream. For joint problems, BMC or MSEC is injected into the affected joint (intra-articular).
All MSEC doses must be used within the two-year shelf life of the stored MSEC; continuing after that requires a new tissue collection and production cycle. An infusion into a vein and an injection into a joint are established, everyday procedures.
What does Lyme disease treatment with BMC or MSEC cost?
Treatment for Lyme disease costs approximately €8,000 to €36,000, depending on the product: BMC approximately €8,000 to €9,000. MSEC treatment costs approximately €20,000–€36,000, depending on the number of doses (three to ten), and requires a two-day visit for tissue collection, followed by further visits. Both are billed according to the German Medical Fee Schedule (GOÄ). With BMC, the cost is closer to €9,000 where CT guides an injection into a joint, otherwise closer to €8,000. For MSEC, the base package — the mini-liposuction and the first three doses — costs approximately €20,000; each further dose, into a vein or a joint, costs approximately €2,250. Because we recommend using all 10 MSEC doses over a longer period, most MSEC treatment plans reach the upper part of this range.
With MSEC, a double liposuction can be recommended when symptoms are expected to last: it yields 20 doses, which can be used over the current shelf life of two years from a single collection. The cost is correspondingly higher and is shown in your individual estimate.
Further examinations and your sedation preferences also affect the total, and you receive an individual written estimate before any treatment decision. Our blog post on treatment cost explains what drives the cost of stem cell treatment in general. Travel, accommodation and other personal expenses, including those of an accompanying person, are not included. Treatment for Lyme disease is generally self-funded; you can still ask your insurer about possible reimbursement. All prices are subject to change.
Why does the cost of Lyme disease treatment vary with the product and the application route?
All treatments at ANOVA IRM are billed according to the German Medical Fee Schedule (Gebührenordnung für Ärzte, GOÄ); within it, the cost depends mainly on the product and the route of application. BMC is a single application on the day of collection, into a vein or into a joint, with CT guidance where needed. MSEC is charged per dose and is mainly given into a vein, because the symptoms often involve several organs and the bloodstream reaches them all; for joint problems it is injected into the joint. The exact cost of your treatment plan is set out in your individual written cost estimate.
Frequently asked questions — eligibility, process and travel
How are BMC and MSEC administered for Lyme disease?
BMC is given once, on the day of bone marrow collection, into a vein or, for joint problems, into the affected joint, guided by CT where needed. MSEC is usually given as an infusion into a vein in Offenbach, under medical supervision, and into the joint for joint problems. Two MSEC doses are given at the start; then a single dose every 4 to 6 weeks if you live nearby, or a double dose every 3 months.
Which types of Lyme disease may be considered for treatment?
Lyme disease in adults, including post-treatment Lyme disease syndrome (PTLDS), symptoms described as chronic Lyme disease, lasting nerve damage after Lyme neuroborreliosis and Lyme arthritis with joint problems. Previous antibiotic treatment is not a requirement. Each form is assessed differently: in PTLDS, other causes of fatigue and pain are looked for first; in arthritis, a rheumatologist is usually involved, and BMC or MSEC can be injected into the joint. Neither BMC nor MSEC replaces antibiotics where your doctor recommends them.
How long does the whole Lyme disease treatment process take?
With MSEC, about one and a half years from the first contact to the last dose; BMC is completed in two consecutive days in Offenbach. The remote assessment takes from about two weeks to several months, depending on how quickly your previous results and reports are available. With MSEC, the tissue collection takes about two days, followed by approximately four weeks of production and quality control. The applications then extend over about a year and must be completed within the two-year shelf life of the stored MSEC.
Does health insurance cover Lyme disease stem cell therapy in Germany?
No. Experimental BMC or MSEC treatment for Lyme disease is not normally reimbursed by health insurers, so please plan to pay for it yourself. Antibiotics, physiotherapy and your regular medical check-ups remain covered as usual; you can still ask your insurer for an individual decision on BMC or MSEC.
Should I stop my current Lyme disease medication such as doxycycline, amoxicillin or ceftriaxone?
No. The programme complements guideline-based care. Please continue to work with your treating physician throughout.
Should I continue my existing Lyme disease treatment such as physiotherapy and pain management?
How often do I need to travel to Germany for Lyme disease stem cell treatment?
With BMC usually once, for two days. With MSEC, usually about six times over about a year if you live further away. The first trip of about two days is for bloodwork and tissue collection in Offenbach, less than 20 minutes from Frankfurt Airport. The further trips are for the applications: two doses at the start, then a double dose every 3 months. Living close by means more frequent but shorter visits, for a single dose every 4 to 6 weeks. The full sequence is described on our BMC page and our MSC secretome page.
What medical records should I send for a Lyme disease assessment?
Please send us your most recent documents; we will ask if we need anything else. Helpful are, for example, your Lyme disease blood test results (ELISA and immunoblot) and, if done, spinal fluid findings. A list of any antibiotics you received, with dates and duration, also helps. Reports from your neurologist or rheumatologist, MRI or ultrasound images of affected joints, joint fluid results and a current medication list complete the picture.
Does ANOVA IRM treat international patients with Lyme disease?
Yes. People with Lyme disease from other countries can begin from home: we advise in English and carry out the first assessment by phone or video.
What happens in the body after the infection, the standard of care, the rationale for BMC and MSEC and all references.
You are hereLyme Disease: Clinical & Scientific Evidence
What happens in the body in Lyme disease (Lyme borreliosis)?
Lyme disease, also called Lyme borreliosis, is caused by spirochetes of the Borrelia burgdorferi sensu lato complex. In Europe, Borrelia afzelii and Borrelia garinii predominate; in North America, Borrelia burgdorferi sensu stricto. The bacteria are transmitted by Ixodes ticks, in Europe mainly Ixodes ricinus.[1] Depending on the region, about 3–38% of adult ticks and 5–12% of nymphs carry Borrelia.[8]
Doctors distinguish early localised, early disseminated and late Lyme disease.[1] In an external population-based study in Germany, erythema migrans accounted for 89% of early manifestations.[9] Neurological involvement (Lyme neuroborreliosis) occurs in about 3–15% of infections in Europe.[8] Lyme arthritis is more common in North America, and acrodermatitis chronica atrophicans, a late skin form, mainly in Europe.[1],[9]
About 14.5% of people worldwide have antibodies against Borrelia, with the highest proportion, 20.7%, in Central Europe.[2] In Germany, 221 per 100,000 people with statutory health insurance were newly diagnosed in 2024.[4] After guideline-based treatment, persistent symptoms were found in 27.2% of patients in an external Dutch cohort study, compared with 21.2% in the general population.[5] The difference of six percentage points suggests that part of these symptoms is related to Lyme disease.
What causes Lyme disease, and what are the risk factors?
Lyme disease is caused by the infection itself; persistent symptoms after treatment have different, not fully understood causes. What causes Lyme disease and what keeps symptoms going are two different questions; the next section deals with the second.
- Tick bites: the risk depends on how long the tick is attached; early removal lowers it.[1],[8]
- Season and region: most infections occur in the warmer months, when ticks are active; in Germany, rates are highest in Saxony, Thuringia, Bavaria and Brandenburg.[1],[4]
- Outdoor exposure: forestry and farm work, gardening, hiking and contact with pets that carry ticks.[1]
- Delayed treatment: late diagnosis increases the risk of disseminated and late forms.[1],[7]
- Persistent symptoms: why some people develop PTLDS is not known; external studies point to immune activation that continues after treatment.[5],[14]
What drives persistent symptoms after Lyme disease?
In Lyme arthritis, joint inflammation can continue after the bacteria have been cleared, called antibiotic-refractory or post-infectious Lyme arthritis. External studies link this to an excessive immune response and autoimmune reactions in the joint lining.[12] Fragments of the bacterial cell wall (peptidoglycan) were found in joint fluid of patients months after antibiotic treatment and may keep the inflammation going.[13]
In PTLDS, raised levels of the immune messenger CCL19 one month after treatment were associated with persistent symptoms in an external cohort study.[14] A small external imaging pilot study found signs of activated immune cells in the brain (glial activation) in people with PTLDS.[15] After Lyme neuroborreliosis, about 28% of treated patients report residual symptoms.[8] This is where our programme aims — at persisting inflammation, not at the infection, and not at a cure.
What is the guideline-based standard of care for Lyme disease?
In Germany, the S3 guideline on Lyme neuroborreliosis and the S2k guideline on cutaneous Lyme borreliosis describe diagnosis and treatment. In the United States, the joint guideline of IDSA, AAN and ACR applies.[7],[8],[9] All recommend antibiotics. Erythema migrans is treated with doxycycline or amoxicillin by mouth for one to two weeks.[7],[9] Lyme neuroborreliosis is treated with doxycycline by mouth or ceftriaxone into a vein for 14 days, or for 14 to 21 days in late disease; both work equally well.[8]
Lyme arthritis is treated with oral antibiotics for 28 days. If it persists, a second course or intravenous ceftriaxone follows; after that, rheumatological treatment with anti-inflammatory drugs such as methotrexate, or removal of the inflamed joint lining (synovectomy).[7],[12] Lyme carditis is monitored and treated with antibiotics, if necessary in hospital.[7] Acrodermatitis chronica atrophicans is treated for 21 to 28 days.[7]
For PTLDS, the guidelines advise against further antibiotics. In an external randomised trial with 280 patients, 12 weeks of additional antibiotics did not improve quality of life compared with placebo; earlier external trials came to the same result.[10],[11] Treatment is directed at the symptoms, for example with physiotherapy and pain management.[8]
These treatments cure the infection in most people, but none of them reliably resolves symptoms that persist after it. BMC and MSEC do not replace standard care.
How is Lyme disease diagnosed, and what do we not do ourselves?
Lyme disease is diagnosed by your GP, dermatologist, neurologist or rheumatologist, not by us. A typical erythema migrans needs no test.[9] Otherwise, two-tier serology is used: an enzyme immunoassay (ELISA) followed by an immunoblot, or a second ELISA in the modified two-tier test.[7] Antibodies can remain for years after successful treatment and do not prove an active infection.[8]
Lyme neuroborreliosis is confirmed by lymphocytic pleocytosis in the cerebrospinal fluid and a Borrelia-specific antibody index of 1.5 or more; the chemokine CXCL13 can help in early cases.[8] Lyme arthritis is supported by PCR of synovial fluid, and Lyme carditis by an ECG showing atrioventricular block.[7] PCR and culture are not used for screening.[8]
What we do ourselves is imaging: MRI with or without contrast and CT guidance for an injection into a joint where needed, carried out at the Prof. Dr. Stehling Institut für Bildgebende Diagnostik GmbH in the same building, which also belongs to Dr. Stehling. We do not make the diagnosis of Lyme disease, carry out lumbar punctures for diagnosis or prescribe your antibiotic treatment; please bring these findings from your doctors.
What is the scientific rationale for BMC and MSEC in Lyme disease?
Bone marrow concentrate (BMC)
ANOVA IRM has not yet tested BMC or MSEC for Lyme disease in a clinical study. To our knowledge, BMC itself has not been studied in Lyme disease. The only related study used donor mesenchymal stem cells from umbilical cord, injected into the joints of mice with Lyme arthritis.[17] These cells were multiplied in the laboratory and differ from BMC, which contains your own bone marrow cells in their natural composition.
MSC secretome (MSEC)
MSEC is a mesenchymal stromal cell secretome: the growth factors, cytokines (cell-to-cell messengers) and extracellular vesicles released by these cells, without the cells themselves. Most of their effects are thought to come from these released factors, which can modulate the activity of immune cells.[16]
The mesenchymal stem cell secretome, or MSC secretome, is also called the mesenchymal stromal cell secretome. Mesenchymal stem cells and mesenchymal stromal cells are two names for the same cells (MSC); the International Society for Cell & Gene Therapy recommends “stromal” for cells expanded in the laboratory.[18],[19]
In an external animal study, mice with Lyme arthritis received human umbilical cord mesenchymal stem cells injected into the ankle joint. Joint swelling, the number of immune cells in the joint and the inflammatory messengers IL-6 and TNF-α were reduced. The number of bacteria in the tissue did not change significantly.[17] This last point matters, because a treatment that dampens the immune response could in principle allow bacteria to persist.
The study used donor cells injected into the joint, not your own BMC or secretome. To our knowledge, no clinical study of mesenchymal stem cells, bone marrow concentrate, secretome or extracellular vesicles in Lyme disease or PTLDS has been published, and none is registered.
What is the efficacy hypothesis behind BMC and MSC secretome in Lyme disease?
In antibiotic-refractory Lyme arthritis and possibly in PTLDS, inflammation appears to continue after the bacteria have been treated.[12],[13],[14] The hypothesis is that BMC and the soluble factors of the mesenchymal stromal cell secretome may moderate this immune activity, given into a vein or, for joint problems, into the joint. In an external animal study of Lyme arthritis, mesenchymal stem cells reduced joint inflammation.[17]
Two limitations belong with it. Neither BMC nor MSEC has an antibacterial effect, and neither replaces antibiotics. And whether the findings in mice apply to people with PTLDS or nerve damage is not known; our aim is to influence persisting inflammation, not to cure Lyme disease.
Talk to us about current changes or additions to the programme. For several conditions, ANOVA IRM also offers infusion therapies alongside the components described above.
Where does our own Lyme disease evidence stand?
We do not currently publish our own outcome data for Lyme disease. What we can say about BMC and MSEC for Lyme disease therefore rests on the published literature and on the rationale described above. Some patients describe their experience on our testimonials page; these are individual accounts, not evidence that a treatment works.
Stem cell-based therapy for Lyme disease remains experimental, and outcomes vary from patient to patient. Treatment goals are agreed individually and followed with the symptoms you report, standard questionnaires on fatigue and pain, and, in arthritis, the joint examination. Treatment cannot guarantee relief of pain, fatigue or nerve damage.
What is the realistic goal of Lyme disease treatment?
Care for Lyme disease aims to clear the infection early and to prevent late forms.[7],[8] After that, the aim is to relieve symptoms and help you regain everyday function. For BMC and MSEC, too, the aim is to influence persisting inflammation, not to treat the infection or to cure.
Legal framework for BMC and MSEC in Lyme disease
ANOVA IRM manufactures BMC, an advanced therapy medicinal product (Section 4b(1) AMG), under a collection (procurement) authorisation (Section 20b AMG) and a manufacturing authorisation under Section 13 AMG. MSEC, an autologous tissue preparation, is made under a collection (procurement) authorisation (Section 20b AMG) and a manufacturing authorisation under Section 20c AMG. All authorisations were granted by the Darmstadt Regional Council, today the Hessian State Office for Health and Care (HLfGP), with the involvement of the Paul-Ehrlich-Institut; the HLfGP inspects the facility regularly. As both products are used only for ANOVA IRM’s own patients, no authorisation under Section 4b(3) and no approval under Section 21a AMG is required; see our regulatory status page.
Frequently asked questions — Lyme disease, evidence and approval status
Is stem cell therapy approved for Lyme disease anywhere?
No. To our knowledge, no stem cell therapy is approved for Lyme disease or for persistent symptoms after it in any country. The US list of approved cell and gene therapies contains no product for this condition.[22] At ANOVA IRM, BMC or MSEC is given for Lyme disease as an individual therapeutic attempt.
Are MSC studies evidence that BMC or MSEC works for Lyme disease?
No. The only study we know of is an external animal study with donor mesenchymal stem cells injected into the joints of mice.[17] It provides a rationale, but no proof. Proof would require a randomised controlled trial in people with BMC or MSEC itself, and none exists. See the scientific rationale.
What type of stem cell therapy does ANOVA use for Lyme disease?
Two autologous products, chosen case by case. Bone marrow concentrate (BMC) comes from your pelvic bone and contains mesenchymal and haematopoietic stem cells in their natural composition. MSC secretome (MSEC) is produced from mesenchymal stromal cells from your own abdominal fat tissue; it is cell-free and contains no living cells. Details are on our BMC page and our mesenchymal stem cell secretome page.
Is “chronic Lyme disease” the same as PTLDS?
Not exactly. Post-treatment Lyme disease syndrome (PTLDS) describes symptoms such as fatigue, pain or problems with concentration that persist for at least six months after a confirmed and treated infection.[7] The term “chronic Lyme disease” is used more loosely, often without proof of a previous infection; experts advise against it as a diagnosis.[6],[8] Longer or repeated antibiotic courses have not helped people with persistent symptoms in external randomised trials.[10],[11] At ANOVA IRM we consider adults with Lyme disease after an individual assessment, whether their symptoms are called PTLDS or chronic Lyme disease, and whether or not they have received antibiotics.
Is there a vaccine against Lyme disease?
Not yet. To date, no vaccine against Lyme disease is approved for humans.[21] According to the manufacturers’ press releases, a vaccine candidate was tested in an external phase 3 trial (VALOR) with 9,437 participants aged five years and older. It reached an efficacy of about 73% in a pre-specified analysis, but its primary statistical criterion was not met; fewer cases occurred than expected.[20] An application for approval has been under review by the European Medicines Agency since August 2026.[21] Until then, the best protection is to avoid tick bites and to remove ticks early.
How common is Lyme disease?
Common. Lyme disease is the most frequent tick-borne infection in Europe and North America.[1] In Germany, 138,107 people with statutory health insurance were newly diagnosed in 2024, or 221 per 100,000; rates range from 116 in North Rhine to 361 in Saxony.[4] In the United States, about 476,000 people are diagnosed and treated each year.[3] Worldwide, about 14.5% of people have antibodies against Borrelia, a sign of a past infection.[2] About one in four treated patients reports persistent symptoms, compared with about one in five people without Lyme disease.[5]
What are the symptoms of Lyme disease?
The symptoms depend on the stage, and many people only ever have the skin rash. None of the symptoms alone proves Lyme disease.[1],[9]
Early localised (days to weeks after the bite)
- an expanding red rash around the bite, at least 5 cm across (erythema migrans)
- tiredness, fever, headache and aching muscles or joints
Early disseminated (weeks to months)
- several rashes at once (multiple erythema migrans)
- severe nerve root pain, often worse at night (Bannwarth syndrome)
- facial palsy and other cranial nerve palsies; meningitis
- palpitations, dizziness or shortness of breath in Lyme carditis
- a bluish-red swelling of the earlobe or nipple (borrelial lymphocytoma)
Late (months to years)
- swollen, painful large joints, most often the knee (Lyme arthritis)
- thinning, bluish-red skin on the hands or feet (acrodermatitis chronica atrophicans)
- rarely, chronic inflammation of the brain or spinal cord with problems walking, with the bladder or with memory
After treatment
- fatigue, pain and problems with concentration that persist (PTLDS)
Which forms of Lyme disease are there, and how does it progress?
Lyme disease is divided into stages by the time since the bite and the organs affected; most people have only the early localised form.[1],[9]
- Early localised Lyme disease: erythema migrans at the site of the bite, days to weeks after it. With antibiotics, it heals in almost all cases.[9]
- Early disseminated Lyme disease: spread through the blood to other skin areas, the nervous system (Lyme neuroborreliosis), or the heart (Lyme carditis).[1],[8]
- Late Lyme disease: Lyme arthritis, acrodermatitis chronica atrophicans and, rarely, late neuroborreliosis, months to years after the bite.[1]
- Post-treatment Lyme disease syndrome (PTLDS): symptoms that persist after treatment, without signs of an active infection.[5],[7]
- Course: without treatment, the infection can progress to later stages; with treatment, most people recover fully, though recovery from nerve damage can take months.[7],[8]
What complications can Lyme disease cause?
Most complications arise when the infection is not treated early; some remain after treatment.[1],[8]
- Nerves: lasting facial palsy, nerve pain or weakness after Lyme neuroborreliosis.
- Heart: atrioventricular block in Lyme carditis, which may require a temporary pacemaker.
- Joints: arthritis that persists after antibiotics, with damage to cartilage in rare cases.
- Skin: lasting thinning of the skin in acrodermatitis chronica atrophicans.
- After treatment: persistent fatigue, pain and problems with concentration (PTLDS).
Important Pages
Questions people usually ask next. Each is answered in full on its own page.
Affiliations of ANOVA
ANOVA IRM shares its premises in Offenbach with two further institutions owned by Dr. Stehling: the Institut für Bildgebende Diagnostik (IBDO), providing MRI and CT imaging, and the VITUS PRIVATKLINIK Prof. Dr. Stehling GmbH. Because imaging is carried out in the same building, the MRI required before the tissue collection and CT guidance for an injection into a joint can be performed in-house rather than referred elsewhere. See diagnostics at ANOVA IRM.
References — Lyme disease literature
Literature specific to Lyme disease is listed here. General literature on MSC, secretome and extracellular vesicles is maintained on the MSC secretome page, bone marrow literature on the BMC page.
Lyme disease — definition, frequency, forms and course
- [1] Steere AC, Strle F, Wormser GP, et al. Lyme borreliosis. Nat Rev Dis Primers. 2016;2:16090. doi:10.1038/nrdp.2016.90. PMID: 27976670.
- [2] Dong Y, Zhou G, Cao W, et al. Global seroprevalence and sociodemographic characteristics of Borrelia burgdorferi sensu lato in human populations: a systematic review and meta-analysis. BMJ Glob Health. 2022;7(6):e007744. doi:10.1136/bmjgh-2021-007744. PMID: 35697507.
- [3] Kugeler KJ, Schwartz AM, Delorey MJ, et al. Estimating the frequency of Lyme disease diagnoses, United States, 2010–2018. Emerg Infect Dis. 2021;27(2):616–619. doi:10.3201/eid2702.202731. PMID: 33496229.
- [4] Zentralinstitut für die kassenärztliche Versorgung in Deutschland (Zi). 2024 über 138.000 Borreliose-Neudiagnosen in Deutschland. Grafik des Monats, June 2026. Accessed 22 October 2026. https://www.zi.de/fileadmin/Downloads/Service/Medien/Grafik_des_Monats/2026/GdM_Borreliose_06-26.pdf Institute data (not peer-reviewed).
- [5] Ursinus J, Vrijmoeth HD, Harms MG, et al. Prevalence of persistent symptoms after treatment for Lyme borreliosis: a prospective observational cohort study. Lancet Reg Health Eur. 2021;6:100142. doi:10.1016/j.lanepe.2021.100142. PMID: 34557833.
- [6] Feder HM Jr, Johnson BJB, O’Connell S, et al.; Ad Hoc International Lyme Disease Group. A critical appraisal of “chronic Lyme disease”. N Engl J Med. 2007;357(14):1422–1430. doi:10.1056/NEJMra072023. PMID: 17914043.
Guidelines and standard of care
- [7] Lantos PM, Rumbaugh J, Bockenstedt LK, et al. Clinical practice guidelines by the Infectious Diseases Society of America (IDSA), American Academy of Neurology (AAN), and American College of Rheumatology (ACR): 2020 guidelines for the prevention, diagnosis and treatment of Lyme disease. Clin Infect Dis. 2021;72(1):e1–e48. doi:10.1093/cid/ciaa1215. PMID: 33417672.
- [8] Rauer S, Kastenbauer S, Dersch R, et al.; Consensus group. Guidelines for diagnosis and treatment in neurology – Lyme neuroborreliosis. Ger Med Sci. 2025;23:Doc13. doi:10.3205/000349. PMID: 41195425. S3 guideline, AWMF register no. 030-071.
- [9] Hofmann H, Fingerle V, Rauer S, et al.; Consensus group. Cutaneous Lyme borreliosis: guideline of the German Dermatology Society. Ger Med Sci. 2025;23:Doc12. doi:10.3205/000348. PMID: 41195426. S2k guideline, AWMF register no. 013-044.
- [10] Klempner MS, Hu LT, Evans J, et al. Two controlled trials of antibiotic treatment in patients with persistent symptoms and a history of Lyme disease. N Engl J Med. 2001;345(2):85–92. doi:10.1056/NEJM200107123450202. PMID: 11450676.
- [11] Berende A, ter Hofstede HJM, Vos FJ, et al. Randomized trial of longer-term therapy for symptoms attributed to Lyme disease. N Engl J Med. 2016;374(13):1209–1220. doi:10.1056/NEJMoa1505425. PMID: 27028911.
Disease mechanisms after treatment
- [12] Lochhead RB, Strle K, Arvikar SL, et al. Lyme arthritis: linking infection, inflammation and autoimmunity. Nat Rev Rheumatol. 2021;17(8):449–461. doi:10.1038/s41584-021-00648-5. PMID: 34226730.
- [13] Jutras BL, Lochhead RB, Kloos ZA, et al. Borrelia burgdorferi peptidoglycan is a persistent antigen in patients with Lyme arthritis. Proc Natl Acad Sci U S A. 2019;116(27):13498–13507. doi:10.1073/pnas.1904170116. PMID: 31209025.
- [14] Aucott JN, Soloski MJ, Rebman AW, et al. CCL19 as a chemokine risk factor for posttreatment Lyme disease syndrome: a prospective clinical cohort study. Clin Vaccine Immunol. 2016;23(9):757–766. doi:10.1128/CVI.00071-16. PMID: 27358211.
- [15] Coughlin JM, Yang T, Rebman AW, et al. Imaging glial activation in patients with post-treatment Lyme disease symptoms: a pilot study using [11C]DPA-713 PET. J Neuroinflammation. 2018;15(1):346. doi:10.1186/s12974-018-1381-4. PMID: 30567544.
Mesenchymal stromal cells and their secretome — definitions, laboratory and animal studies
- [16] Galipeau J, Sensébé L. Mesenchymal stromal cells: clinical challenges and therapeutic opportunities. Cell Stem Cell. 2018;22(6):824–833. doi:10.1016/j.stem.2018.05.004. PMID: 29859173.
- [17] Ma W, Kong J, Zhang M, et al. Mesenchymal stem cells reduce inflammation in a mouse model of Lyme arthritis. Stem Cells Int. 2025;2025:4363386. doi:10.1155/sci/4363386. PMID: 40761339. PMCID: PMC12321430. Manufacturer involvement: two of the authors are affiliated with Yunnan Health Cell Biotechnology Ltd.
- [18] Dominici M, Le Blanc K, Mueller I, et al. Minimal criteria for defining multipotent mesenchymal stromal cells. The International Society for Cellular Therapy position statement. Cytotherapy. 2006;8(4):315–317. doi:10.1080/14653240600855905. PMID: 16923606.
- [19] Viswanathan S, Shi Y, Galipeau J, et al. Mesenchymal stem versus stromal cells: International Society for Cell & Gene Therapy (ISCT®) Mesenchymal Stromal Cell committee position statement on nomenclature. Cytotherapy. 2019;21(10):1019–1024. doi:10.1016/j.jcyt.2019.08.002. PMID: 31526643.
Vaccine and approval status
- [20] Pfizer Inc., Valneva SE. Pfizer and Valneva announce Lyme disease vaccine candidate demonstrates strong efficacy in phase 3 VALOR trial. Press release, 23 March 2026. Accessed 22 October 2026. https://valneva.com/press-release/pfizer-and-valneva-announce-lyme-disease-vaccine-candidate-demonstrates-strong-efficacy-in-phase-3-valor-trial/
- [21] Pfizer Inc., Valneva SE. Pfizer and Valneva’s Lyme disease vaccine candidate marketing authorization application validated by European Medicines Agency. Press release, 14 August 2026. Accessed 22 October 2026. https://s206.q4cdn.com/795948973/files/doc_news/Pfizer-and-Valnevas-Lyme-Disease-Vaccine-Candidate-Marketing-Authorization-Application-Validated-by-European-Medicines-Agency-2026.pdf
- [22] U.S. Food and Drug Administration. Approved Cellular and Gene Therapy Products. Accessed 22 October 2026. https://www.fda.gov/vaccines-blood-biologics/cellular-gene-therapy-products/approved-cellular-and-gene-therapy-products