

Translational Medicine — Works in Progress
The ANOVA COPD Stem Cell Secretome Treatment Programme Germany
Autologous, adipose tissue-derived MSC secretome (MSEC) therapy for people living with chronic obstructive pulmonary disease (COPD), including emphysema and chronic bronchitis. Offenbach, Germany. Experimental — fully legal — manufactured under German regulatory authorisation and official inspection since 2018.
You have tried a lot. Perhaps you have been told there is nothing more to be done. We listen first, examine thoroughly, and then tell you honestly whether a stem cell-based therapy, one of our programmes or another option could be right for you. Each option is discussed as an addition to your current treatment, never as a replacement.
| Component | Detail |
|---|---|
| Two products | Bone Marrow Concentrate (BMC) and Mesenchymal Stem Cell Secretome (MSEC), each manufactured under official authorisation; no marketing authorisation (experimental) |
| Authorisations | BMC § 20b / § 13 AMG · MSEC § 20b / § 20c AMG (German Medicines Act) |
| Location | Offenbach am Main, Germany |

COPD in brief, the programme and its components — the essentials at a glance.
You are hereIntroduction & Summary
What is COPD, in brief?
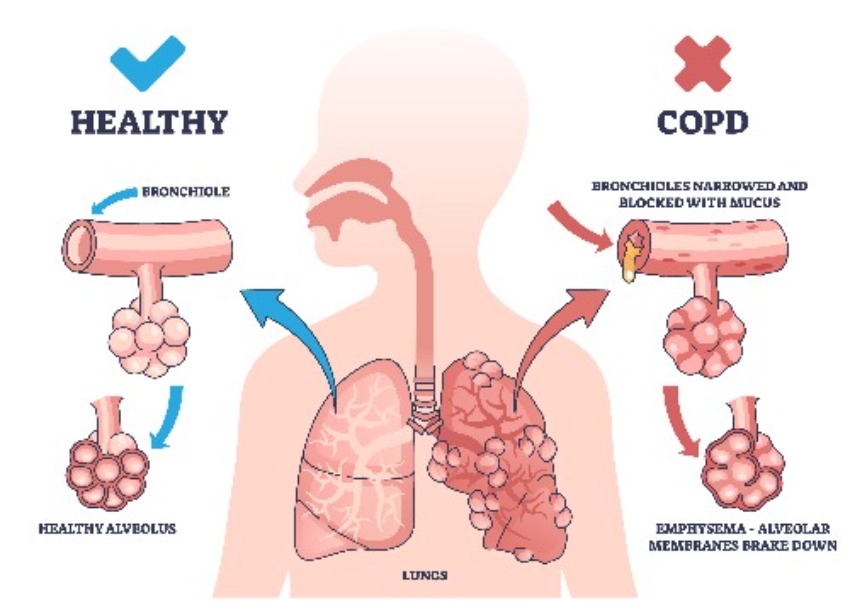
Chronic obstructive pulmonary disease (COPD) is a long-term lung disease in which the airways are narrowed and the air sacs (alveoli) can be damaged, so that air cannot flow out of the lungs freely. Two forms often occur together: chronic bronchitis, a long-lasting inflammation of the airways with cough and mucus, and emphysema, the destruction of the walls between the air sacs. A long-standing inflammation of the airways, mostly caused by tobacco smoke (hence the term “smoker’s lung”), drives both.[1]
The diagnosis rests on spirometry, a breathing test. It compares the air breathed out in the first second (FEV1) with the total air breathed out (FVC); a ratio below 0.7 after an inhaler that opens the airways confirms airflow obstruction.[1] The severity of the obstruction is graded in GOLD stages 1 to 4. A CT scan of the chest shows emphysema; blood tests can show a rare inherited form (alpha-1 antitrypsin deficiency). To date no cure is known for COPD.
Common symptoms include breathlessness, especially on exertion, a long-lasting cough with or without mucus, wheezing, chest tightness and tiredness. Flare-ups (exacerbations) can make the symptoms suddenly worse.
More details can be found below in our scientific section on COPD.
What is the ANOVA COPD programme?
ANOVA offers autologous mesenchymal stem cell secretome (MSEC) for people with COPD, in addition to the treatment their pulmonologist prescribes. The programme combines an optional CT scan of the lungs with repeated applications of MSEC, given mainly as an infusion into a vein. Each component is selected individually; the programme is not a fixed package.
Stem cells are thought to act mainly through soluble factors, together called the secretome, which includes exosomes and many other factors. In COPD, a long-lasting inflammation of the airways and air sacs continues even after a person has stopped smoking.[10] MSEC is intended to potentially influence this inflammation and the environment of the remaining lung tissue; it is not intended to replace air sacs that have been destroyed. Our hypothesis is that, after an infusion into a vein, the secretome reaches the lungs first, because they are the first network of small blood vessels the blood passes through.
ANOVA IRM has not yet tested MSEC in a clinical study. The current state of research is described in the clinical and scientific section below.

The ANOVA COPD Programme — Components
CT of the lungs (optional, where needed)
Where needed, a CT scan of the lungs can be carried out in-house. It shows how far emphysema and changes of the airways have progressed, and whether there is a finding that needs to be clarified first. It helps to plan treatment with MSEC and does not replace the follow-up by your pulmonologist.
MSC secretome (MSEC)
MSEC is the cell-free mixture of signalling molecules released by your own mesenchymal stromal cells from fat tissue, given mainly as an infusion into a vein or, where suitable, inhaled as a fine mist. External laboratory and animal studies suggest that such factors may reduce inflammation and damage to the air sacs in models of emphysema.[29],[30] Small external clinical studies with mesenchymal stem cells — cells, not secretome — are summarised in the clinical and scientific section below.
Inhalers, pulmonary rehabilitation and vaccinations are not part of our programme; they continue with your pulmonologist and GP at home.
Which diagnostics do we use for COPD at ANOVA IRM?
Which tests are used to diagnose COPD?
COPD is diagnosed from your history, a physical examination and spirometry after an inhaler that opens the airways.[1] Body plethysmography measures trapped air in the lungs, and the diffusion capacity (DLCO) shows how well oxygen passes into the blood. A CT scan of the chest shows emphysema and other changes of the lungs. Blood tests include the alpha-1 antitrypsin level and the eosinophil count, and a blood gas test or pulse oximetry shows the oxygen level.
What do we review before COPD treatment at ANOVA IRM?
Before any treatment decision we review your lung function results, your scans, your current inhaled medication and how many flare-ups you have had in the last year. We also review your alpha-1 antitrypsin status as found by your own doctors, the oxygen values they have measured, and whether you are fit for the brief sedation required for tissue collection.
- Standard: an MRI of the abdominal wall to exclude a hernia is required before the liposuction, taken no more than four weeks beforehand. It can be done at home or at ANOVA IRM.
- Optional: a CT scan of the lungs at ANOVA IRM before treatment, if no recent scan is available, or to document the extent of emphysema.
- Optional: further MRI or CT scans, with or without contrast, where your COPD situation calls for them, for example to clarify a finding on an earlier scan.
Imaging can be carried out in-house; all examinations can also be done by your own doctors. Lung function tests, pulse oximetry, blood gases and the six-minute walk test are not carried out at ANOVA IRM; please bring these findings from your doctors. The full diagnostic pathway is described on our diagnostics page.
Why ANOVA IRM for COPD?
ANOVA IRM has made MSEC in its own facility in Offenbach since 2018 (see our regulatory status). Where needed, a CT scan of the lungs is carried out by the radiology in the same building. Your pulmonologist and GP remain the basis of your care.
What can you expect as a patient with COPD?
The first assessment can take place remotely, by phone or video, before any journey to Germany. Treatment itself takes place in person in Offenbach am Main, less than 20 minutes from Frankfurt Airport. Before you decide, you receive an individual written cost estimate; the services of our patient care team are free of charge. If you would like existing findings assessed independently, we also offer a second opinion.
Quick answers
Is there a cure for COPD?
No. Lung tissue destroyed by emphysema does not grow back. Stopping smoking, inhaled medication, pulmonary rehabilitation and, in severe cases, oxygen therapy, valves or surgery ease the symptoms, reduce flare-ups and can slow the decline.[1] Experimental approaches such as mesenchymal stem cell secretome (MSEC) and cell-based therapies are being explored.[26]
Does stem cell therapy cure COPD or emphysema?
No. Stem cell therapy is not a cure for COPD. The use of MSEC at ANOVA IRM aims to influence the inflammation in the airways and the remaining lung tissue, and it is given alongside inhalers and pulmonary rehabilitation, never instead of them.
Is COPD stem cell therapy legal in Germany?
Yes, provided the manufacturer holds the official authorisations for its product. For people with COPD, ANOVA IRM produces MSEC under a collection (procurement) authorisation (Section 20b AMG) and a manufacturing authorisation under Section 20c AMG. These were granted by the Darmstadt Regional Council, today the Hessian State Office for Health and Care (HLfGP), with the involvement of the Paul-Ehrlich-Institut; the HLfGP inspects the facility regularly. MSEC is given as an individual therapeutic attempt (individueller Heilversuch); the legal basis is set out on our regulatory status page.
Is COPD stem cell therapy safe?
Not without qualification. The fat collection, the brief sedation and the application of MSEC carry risks, which your doctor explains before treatment. Manufacturing under an official authorisation adds a layer of safety: the competent authority inspects the facility every two years, and every change to the process and every new material must be reported to it. Providers without an authorisation are not subject to this control.
Dr. mult. Stehling and ANOVA IRM have made MSEC with the same process since 2016, under an authorisation according to Section 20c AMG since 2018, and have treated 355 people with it (as of October 2026). Experience with inhaled MSEC is more limited. To date, no serious adverse event has been caused by the product. No karyotyping is required for MSEC, because MSEC is cell-free and therefore cannot contain cancer cells. Safety is first examined in phase 1/2 studies with roughly 10 to 100 patients; ANOVA IRM has not run such a study, but has treated well above that number. Ask every provider for its authorisations; what regulators warn about is summarised under unproven therapies.
What medication is used for COPD?
Long-acting inhaled bronchodilators, which open the airways — LAMA and LABA, usually combined in one inhaler — are the basis of treatment.[1] Inhaled corticosteroids are added for people with frequent flare-ups and higher blood eosinophil counts; roflumilast, azithromycin and, for some patients, the antibody dupilumab are further options.[1],[17] MSC secretome (MSEC) at ANOVA IRM is added to this treatment and does not replace it.
Who qualifies, what the process actually involves, and what it costs — step by step.
You are hereCOPD Treatment: Eligibility, Process & Cost
In this section you will find everything about treatment for chronic obstructive pulmonary disease (COPD) at ANOVA IRM: who is eligible, the process step by step and the cost.
What does the COPD treatment timeline look like?
- 01
Initial evaluation
Remote, by phone or video — typically 2 weeks to a few months
- 02
Preliminary screening
In your home country, to avoid an unnecessary journey
- 03
First visit — bloodwork and tissue collection
Two-day outpatient visit to Offenbach: bloodwork first, then — if the results are in order — mini-liposuction under brief sedation
- 04
Production and quality control
Approximately 4 weeks; yields 10 doses
- 05
Storage
Up to 2 years, allowing an extended personalised schedule
- 06
Application schedule
Set individually: one dose every 4–6 weeks, or two doses every 3 months
Who qualifies for COPD treatment, and what are the requirements?
We consider adults with COPD in GOLD stages 1 to 3, confirmed by spirometry, whose condition has been stable for at least four weeks without a flare-up (exacerbation). Your inhaled medication should be set up according to the guideline, and pulmonary rehabilitation should have been offered or completed. You must be able to breathe on your own, without a ventilator, and be well enough for mini-liposuction under brief sedation. If MSEC is to be inhaled, you need to be able to inhale through a mouthpiece for several minutes. You also need to be able to travel to Offenbach for repeated applications. Every treatment recommendation follows a full clinical evaluation in which the treating physician weighs benefit and risk. Applying for an evaluation does not mean that treatment will be offered.
What are the contraindications for COPD treatment?
Our treatments are experimental. We treat only people for whom, after medical assessment, we consider the benefit-risk balance to support treatment.
Applies to all ANOVA treatments:
- Active cancer within the last two years
- Under the age of legal majority
- Pregnancy or breastfeeding
- Active infectious disease (hepatitis A, B, C, HIV, syphilis or other)
Specific to COPD:
- Unable to breathe unaided, or dependent on a ventilator
- Difficulty breathing in the supine position (sedation for the tissue collection)
- A flare-up (exacerbation) or chest infection within the last four weeks
- An unclarified nodule or mass on a lung scan
- Severe pulmonary hypertension or right heart failure (cor pulmonale)
- Psychiatric disorder that would prevent informed consent or cooperation
Long-term oxygen therapy and blood-thinning medication are not contraindications in themselves. Whether medication needs to be paused for the fat collection is decided with your treating doctors; please never stop it on your own.
What does COPD therapy at ANOVA IRM involve, step by step?
What screening is needed before you travel for COPD treatment?
A preliminary screening in your home country helps you avoid an unnecessary journey. It usually consists of a blood test for HIV, hepatitis A, B or C, syphilis and other active infections. Together with your latest lung function test and lung scan, it also shows early whether medical factors would rule out treatment.
What happens at your first visit to Offenbach for COPD?
The first treatment visit takes about two days in Offenbach and is outpatient. On the first day, bloodwork is repeated at ANOVA IRM as German medical rules require. The physician then completes the final assessment, including your breathing, the oxygen values from your doctors’ findings and your fitness for sedation. If the results are in order, a small amount of abdominal fat tissue is collected the next day by mini-liposuction under brief sedation. The first secretome application usually follows four to six weeks later.
How is your MSEC for COPD produced and quality-controlled?
In our own facility in Offenbach, mesenchymal stromal cells are isolated from the collected fat tissue and expanded. This takes place under official authorisation and officially inspected good professional practice (GFP, gute fachliche Praxis; similar to Good Tissue Practice, GTP, in the US, but more than GTP). From these cells we obtain your MSEC — the signalling molecules they release, not the living cells. Production and quality control take approximately four weeks and yield 10 doses per production cycle. Every patient batch is tested with methods validated according to the European Pharmacopoeia (Ph. Eur.) and GMP and released under a documented procedure. The released secretome is stored at −80 °C and keeps for up to two years.
How is MSEC applied for COPD?
COPD is a chronic, progressive disease, and there is currently no cure. We therefore recommend a longer-term treatment using all 10 doses produced rather than a single application; see the timeline above.
The schedule is set individually for each patient, for example:
- At the start: two doses.
- Boost: optionally, treatment can start with a boost of three doses during one stay when MSEC is given intravenously; after that the schedule depends on where you live.
- If you live close by: a single MSEC dose every 4 to 6 weeks.
- If you live further away: a double dose every 3 months.
- Standard route for COPD: an infusion of MSEC into a vein (intravenous), given by an ANOVA IRM physician in Offenbach. Our hypothesis is that the secretome then reaches the lungs first, because blood from the veins passes through the lungs before it reaches the rest of the body.
- Further route: inhalation of nebulised MSEC through a mouthpiece, under medical supervision in Offenbach, where your doctor considers it suitable.
All doses must be used within the two-year shelf life of the stored MSEC; continuing after that requires a new tissue collection and production cycle. Intravenous infusions are standard procedures when performed by experienced physicians, and inhaling medicines with a nebuliser is an established, everyday procedure in lung medicine.
What does COPD treatment with MSEC cost?
MSEC treatment costs approximately €20,000–€36,000, depending on the number of doses (three to ten), and requires a two-day visit for tissue collection, followed by further visits. It is billed according to the German Medical Fee Schedule (GOÄ). The base package — the mini-liposuction and the first three MSEC doses — costs approximately €20,000; each further dose costs approximately €2,250, whether it is given intravenously or inhaled. Because we recommend using all 10 doses over a longer period for a chronic, progressive disease such as COPD, most treatment plans reach the upper end of this range.
A double liposuction can be recommended for a chronic condition: it yields 20 doses, which can be used over the current shelf life of two years from a single collection. The cost is correspondingly higher and is shown in your individual estimate.
Further examinations and your sedation preferences also affect the total, and you receive an individual written estimate before any treatment decision. Our blog post on treatment cost explains what drives the cost of stem cell treatment in general. Travel, accommodation and other personal expenses, including those of an accompanying person, are not included. MSEC treatment for COPD is generally self-funded; you can still ask your insurer about possible reimbursement. All prices are subject to change.
Why does the cost of COPD treatment vary with the application route?
All treatments at ANOVA IRM are billed according to the German Medical Fee Schedule (Gebührenordnung für Ärzte, GOÄ); within it, the cost varies mainly with the route of application. For COPD we mainly administer MSEC intravenously: our hypothesis is that, after an infusion, the secretome reaches the lungs first with the bloodstream. Inhalation is used where your doctor considers it suitable; a dose costs approximately €2,250 either way. The exact cost of your treatment plan is set out in your individual written cost estimate.
Frequently asked questions — eligibility, process and travel
How is MSEC administered for COPD?
Mainly by an infusion into a vein (intravenously), given by an ANOVA IRM physician in Offenbach. Where your doctor considers it suitable, MSEC can also be inhaled as a fine mist through a mouthpiece. Treatment starts with two doses; optionally, it can start with a boost of three doses during one stay when MSEC is given intravenously. After that, a single dose follows every 4 to 6 weeks if you live nearby, or a double dose every 3 months if you live further away.
How long does the whole COPD treatment process take?
About one and a half years from the first contact to the last dose. The remote assessment takes from about two weeks to several months, depending on how quickly your lung function results and scans are available. The tissue collection in Offenbach takes about two days, followed by approximately four weeks of production and quality control. The applications then extend over about a year and must be completed within the two-year shelf life of the stored MSEC.
Does health insurance cover COPD stem cell therapy in Germany?
No. Health insurers do not ordinarily reimburse experimental MSEC treatment for COPD, so you should plan to pay privately. Your inhaled medication, pulmonary rehabilitation and oxygen therapy remain covered as usual; for MSEC you can ask your insurer directly about an individual decision.
Should I stop my current COPD medication such as LAMA, LABA or inhaled corticosteroids?
No. The programme complements guideline-based care. Please continue to work with your treating pulmonologist or GP throughout.
Should I continue my existing COPD treatment such as pulmonary rehabilitation?
Yes. Pulmonary rehabilitation, regular physical activity, vaccinations and, where prescribed, oxygen therapy continue as before. MSEC is added to this care, and nothing changes unless your treating physician recommends it.
How often do I need to travel to Germany for COPD stem cell treatment?
If you live further away, usually about six times over about a year. The first trip of about two days is for bloodwork and tissue collection in Offenbach, less than 20 minutes from Frankfurt Airport. The further trips are for the applications: two doses at the start (or an optional boost of three during one stay), then a double dose every 3 months. If you live close by, you come more often, for a single dose every 4 to 6 weeks. The full sequence is described on the MSC secretome page. If you use oxygen, please let us know early; airlines require advance notice for oxygen on board.
What medical records should I send for a COPD assessment?
Please send us your most recent documents; we will ask if we need anything else. Helpful are, for example, your latest lung function test with spirometry, and if available body plethysmography and diffusion capacity (DLCO). A recent CT scan of the chest, a blood gas or oxygen measurement, and a list of flare-ups and hospital stays in the last year also help. A current medication list and your alpha-1 antitrypsin result, if tested, are useful too.
Does ANOVA IRM treat international patients with COPD?
Yes. People with COPD from other countries can start from home: we advise in English and carry out the first assessment by phone or video.
What happens in the airways and air sacs, the standard of care, the rationale for MSEC and all references.
You are hereCOPD: Clinical & Scientific Evidence
What happens in the lungs in COPD?
The Global Initiative for Chronic Obstructive Lung Disease (GOLD) defines COPD as a heterogeneous lung condition with chronic respiratory symptoms: breathlessness (dyspnoea), cough, sputum and flare-ups. They are caused by abnormalities of the airways and/or the air sacs (emphysema) that lead to persistent, often progressive airflow obstruction.[1] A post-bronchodilator ratio of FEV1 to FVC below 0.7 on spirometry is required for the diagnosis.[1]
Two processes usually occur together. In the small airways, chronic inflammation, mucus and thickening of the airway wall narrow the airways (chronic bronchitis and small airway disease). In emphysema, the walls between the alveoli are destroyed, the lung loses its elastic recoil and air is trapped; the surface for gas exchange shrinks.[10] The severity of airflow obstruction is graded in GOLD stages 1 to 4, with an FEV1 of at least 80%, 50 to 79%, 30 to 49% and below 30% of the predicted value.[1] Symptoms and flare-ups are assessed separately, with questionnaires such as the COPD Assessment Test (CAT) and the mMRC dyspnoea scale.
Worldwide, an estimated 10.3% of people aged 30 to 79 had COPD in 2019, about 392 million people.[4] The World Health Organization ranks COPD as the third leading cause of death worldwide, with 3.4 million deaths in 2023.[3] In Germany, 5.8% of adults reported a known COPD diagnosis in the previous 12 months, with a steep rise in older age groups.[5]
What causes COPD, and what are the risk factors?
COPD develops from an interplay of inhaled noxious particles and gases with individual susceptibility, often over decades. What causes COPD and what keeps it going are two different questions; the next section deals with the second.
- Tobacco smoking: the main cause in high-income countries, where it accounts for more than 70% of cases; second-hand smoke also contributes.[3]
- Indoor and outdoor air pollution: smoke from burning wood, coal or other biomass for cooking and heating is a major cause in low- and middle-income countries. An estimated 25 to 45% of people with COPD worldwide have never smoked.[6]
- Dust, fumes and chemicals at work: long-term occupational exposure.[1]
- Alpha-1 antitrypsin deficiency: a rare inherited lack of a protein that guards the lung tissue against breakdown by enzymes; it can cause emphysema at a young age.[7]
- Lung development: in a long-term study, about half of the people who later developed COPD already had low lung function as young adults.[8] Premature birth, childhood respiratory infections and asthma play a part.[1]
- Age: COPD is usually diagnosed after the age of 40.[1]
What drives the progression of COPD?
Once the disease has begun, inflammation in the airways and the lung tissue persists, even after a person stops smoking. Inflammatory cells such as macrophages, neutrophils and lymphocytes release enzymes (proteases) and reactive oxygen species that break down the connective tissue of the alveolar walls, while repair is impaired.[10] Ageing of lung cells (cellular senescence) is thought to contribute.[10]
Flare-ups (exacerbations) accelerate the course. In the ECLIPSE study, the best single predictor of future exacerbations was a history of previous exacerbations, at every stage of the disease.[9] Continued smoking speeds up the loss of lung function. After stopping, the yearly decline of FEV1 returns towards the normal rate, but lung function that has been lost is not regained.[11]
This is where our programme aims — at the persistent inflammation and the environment of the remaining lung tissue, not at the cause of COPD, and not at a cure.
What is the guideline-based standard of care for COPD?
In Germany, the National Disease Management Guideline (Nationale VersorgungsLeitlinie, NVL) COPD describes care; internationally, the GOLD report is updated every year.[1],[12] Stopping smoking comes first: in the Lung Health Study, a smoking cessation programme lowered mortality over 14.5 years.[13] Vaccinations, for example against influenza, pneumococci, RSV and COVID-19, reduce infections that can trigger flare-ups.[1]
Long-acting inhaled bronchodilators are the basis of drug treatment: long-acting muscarinic antagonists (LAMA) and long-acting beta2-agonists (LABA), usually combined.[1],[2] For people with flare-ups and blood eosinophils of 300 cells per microlitre or more, an inhaled corticosteroid (ICS) can be added as triple therapy. In the IMPACT trial, triple therapy reduced moderate or severe flare-ups by 15% compared with ICS/LABA and by 25% compared with LAMA/LABA.[14] Roflumilast and long-term azithromycin are options for selected patients.[2] Since 2024, the antibody dupilumab has been authorised in the EU for COPD with raised blood eosinophils that is not controlled despite inhaled therapy.[17] In the BOREAS and NOTUS trials, it reduced flare-ups by about 30% compared with placebo.[15],[16]
Pulmonary rehabilitation, with supervised exercise training and education, improves quality of life and exercise capacity to a clinically meaningful degree.[18] For severe low blood oxygen at rest, long-term oxygen therapy for at least 15 hours a day prolongs life.[19],[20] In selected patients with severe emphysema, endobronchial valves or lung volume reduction surgery can reduce trapped air. In the LIBERATE trial, 48% of patients with valves and 17% with standard care improved their FEV1 by at least 15% after one year.[21] Lung transplantation is an option for very few.
These treatments ease breathlessness, reduce flare-ups and, in some cases, prolong life, but none of them restores destroyed alveoli. Research into cell-based approaches is exploring this question; whether it is possible has not been shown. MSEC does not replace standard care.
How is COPD diagnosed, and what do we not do ourselves?
COPD is diagnosed by your pulmonologist or GP, not by us. Spirometry after a bronchodilator confirms the airflow obstruction (FEV1/FVC below 0.7) and grades it (GOLD 1 to 4).[1] Body plethysmography measures trapped air (hyperinflation) and residual volume, and the diffusion capacity for carbon monoxide (DLCO) shows how much gas-exchange surface remains. Pulse oximetry and arterial blood gases show low oxygen (hypoxaemia) or raised carbon dioxide (hypercapnia). The six-minute walk test measures exercise capacity; the CAT and mMRC scales record symptoms, and the number of flare-ups in the last year completes the assessment (GOLD groups A, B and E).[1]
Every person with COPD should be tested once for alpha-1 antitrypsin deficiency.[1] The blood eosinophil count guides the use of inhaled corticosteroids and biologics. A chest CT shows the extent and pattern of emphysema, bronchiectasis and lung nodules; low-dose CT screening for lung cancer is offered to some long-term smokers.[1] Echocardiography is used if pulmonary hypertension is suspected.
What we can do ourselves where needed is imaging: CT of the lungs and MRI with or without contrast. This is carried out at the Prof. Dr. Stehling Institut für Bildgebende Diagnostik GmbH in the same building, which also belongs to Dr. Stehling. We do not perform spirometry, body plethysmography, DLCO, pulse oximetry, blood gas analysis, the six-minute walk test or the pulmonological diagnosis itself; please bring these findings from your doctors.
What is the scientific rationale for MSEC in COPD?
MSC secretome (MSEC)
ANOVA IRM has not yet tested MSEC in a clinical study. MSEC is a mesenchymal stromal cell secretome: the growth factors, cytokines (cell-to-cell messengers) and extracellular vesicles released by these cells, without the cells themselves. Mesenchymal stem cells and mesenchymal stromal cells are two names for the same cells (MSC); the International Society for Cell & Gene Therapy recommends ‘stromal’ for cells grown in the laboratory. Most of its effects are thought to come from these released factors, including the small vesicles called exosomes.[27],[28]
In an external animal study in rats exposed to cigarette smoke for twelve weeks, extracellular vesicles from human umbilical cord MSC reduced airway inflammation and the enlargement of the air spaces typical of emphysema.[29] In an external mouse study of emphysema, artificial nanovesicles made from adipose-derived stem cells were followed by less damage to the lung structure, about as much as with the cells themselves.[30] An external review describes the factors involved, such as hepatocyte growth factor, TSG-6, IL-10 and microRNAs carried in the vesicles.[31] One external animal study, however, found that vesicles from the bone marrow cells of donors with emphysema were not effective, whereas vesicles from healthy donors were.[32] Whether this also applies to fat-derived secretome from people with COPD is not known.
In humans, mainly mesenchymal stem cells — cells, not secretome — have been tested, in a few small external studies. They were well tolerated in small external phase 1 studies in severe emphysema and in stable COPD, and some patients showed short-term changes in inflammation markers in the blood.[22],[23] In a small external uncontrolled study in Vietnam with 20 patients, breathlessness scores and the number of flare-ups improved after one infusion of umbilical cord MSC; lung function did not change.[24] In the small external randomised phase 2 trial by Weiss and colleagues, 62 patients received four monthly infusions of donor bone marrow MSC or placebo. A benefit for lung function, quality of life or flare-ups could not yet be demonstrated; in patients with raised CRP, this inflammation marker fell.[25] An external meta-analysis of 11 studies with 371 patients found a longer six-minute walking distance after cell-based treatment, but no significant change in FEV1, and calls for large randomised trials.[26]
For secretome or vesicles in COPD, only small external uncontrolled reports with donor-derived exosome products exist.[33],[34] For inhalation, a small external phase 1 study in 24 healthy volunteers found nebulised vesicles from adipose MSC well tolerated.[35] A small external randomised phase 1 trial tested inhaled vesicles from umbilical cord MSC in 24 people with pulmonary fibrosis. They were well tolerated; lung function and questionnaire scores improved, but the overall difference from placebo was borderline.[36] To our knowledge, no clinical study has yet tested an autologous adipose-derived secretome in COPD.
What is the efficacy hypothesis behind MSC secretome in COPD?
In COPD, inflammatory cells in the airways and alveoli release proteases and reactive oxygen species, the alveolar walls break down and the cells lining the air sacs die (apoptosis), while repair is impaired.[10] The hypothesis is that the soluble factors of the mesenchymal stromal cell secretome influence this environment. After an infusion into a vein, they would reach the lungs first, as the first network of small blood vessels the blood passes through. In animal models they may dampen inflammation, reduce cell death in the lung and slow the destruction of alveolar walls.[29],[30],[31]
One limitation belongs with it: alveoli that have been destroyed are not expected to grow back. Our aim is to influence the inflammation and the function of the remaining lung tissue, not to cure COPD.
Talk to us about current changes or additions to the programme. For several conditions, including some lung diseases, ANOVA IRM also offers other infusion therapies alongside MSEC.
Where does our own COPD evidence stand?
We do not currently publish our own outcome data for COPD. What we can say about MSEC in COPD therefore rests on the published literature and on the rationale described above.
Stem cell-based therapy for COPD remains experimental, and outcomes vary from patient to patient. Treatment goals are agreed individually and followed with lung function tests, the six-minute walk test and questionnaires such as the CAT. Treatment cannot guarantee better breathing or fewer flare-ups.
What is the realistic goal of COPD treatment?
Care for COPD aims to reduce symptoms and flare-ups, to keep people active and to slow the loss of lung function.[1] For MSEC, too, the aim is to influence the inflammation and the remaining lung tissue, not to rebuild alveoli that have been destroyed.
Legal framework for MSEC in COPD
MSEC is an autologous tissue preparation from the patient’s own fat tissue, which ANOVA IRM manufactures under a collection (procurement) authorisation (Section 20b AMG) and a manufacturing authorisation under Section 20c AMG. Both were granted by the Darmstadt Regional Council, today the Hessian State Office for Health and Care (HLfGP), with the involvement of the Paul-Ehrlich-Institut; the HLfGP inspects the facility regularly. For COPD, MSEC is given as an individual therapeutic attempt (individueller Heilversuch), which concerns the administration only and follows full disclosure and informed consent. Because the product is used only for ANOVA IRM’s own patients, no authorisation under Section 4b(3) or Section 21a AMG is required (see our regulatory status page).
Frequently asked questions — COPD, evidence and approval status
Are MSC studies evidence that MSEC works in COPD?
No. Animal studies and small clinical studies with mesenchymal stem cells provide a rationale, but no proof. In a small external randomised phase 2 trial with 62 patients, a benefit of donor MSC on lung function could not yet be demonstrated.[25] Proof would require a randomised controlled trial with MSEC itself, and none exists. See the scientific rationale.
What type of stem cell therapy does ANOVA use for COPD?
ANOVA uses an autologous mesenchymal stem cell secretome (MSEC), produced from mesenchymal stromal cells taken from the patient’s own abdominal fat tissue. The preparation, given mainly as an infusion into a vein, is cell-free and contains no living cells.
How common is COPD?
Very common. An estimated 10.3% of people aged 30 to 79 worldwide had COPD in 2019, about 392 million people.[4] According to the World Health Organization, COPD is the third leading cause of death worldwide, with 3.4 million deaths in 2023.[3] Nearly 90% of COPD deaths under the age of 70 occur in low- and middle-income countries.[3] In Germany, 5.8% of adults reported a known COPD diagnosis in the previous 12 months, women and men about equally often; the share rises steeply with age.[5] COPD is usually diagnosed after the age of 40.[1]
What are the symptoms of COPD?
The symptoms vary between people and usually develop slowly over years, so they are often noticed late.[1]
Breathing
- breathlessness (dyspnoea), at first on exertion, later also at rest
- wheezing and a feeling of tightness in the chest
- frequent chest infections
Cough and mucus
- a cough lasting for months, often worse in the morning
- mucus (sputum), sometimes discoloured during flare-ups
Other symptoms
- tiredness and reduced exercise capacity
- in advanced stages, weight loss, loss of muscle mass and swollen ankles
Which forms of COPD are there, and how does it progress?
COPD is described by its main changes in the lung and graded by severity; most people have a mixture of the forms.[1],[10]
- Chronic bronchitis: cough with mucus on most days for at least three months in two consecutive years, caused by inflammation of the airways.
- Emphysema: destruction of the alveolar walls with enlarged air spaces and trapped air, best seen on a CT scan.
- COPD with alpha-1 antitrypsin deficiency: an inherited form, often with emphysema at a younger age.[7]
- GOLD stages 1 to 4: mild, moderate, severe and very severe airflow obstruction by FEV1 on spirometry.[1]
- Course: lung function usually declines slowly over years; flare-ups (exacerbations) speed up the decline. In the ECLIPSE study, there were on average 0.85 flare-ups per person in the first year in GOLD stage 2, 1.34 in stage 3 and 2.00 in stage 4.[9]
What complications can COPD cause?
COPD affects more than the lungs, and several of its complications can be prevented or treated early.[1],[10]
- Flare-ups and infections: exacerbations and pneumonia, sometimes requiring a hospital stay.
- Heart and circulation: raised blood pressure in the lungs (pulmonary hypertension) and strain on the right heart (cor pulmonale), and a higher risk of heart disease.
- Low oxygen: chronic respiratory failure, which may require long-term oxygen therapy.
- Lung cancer: a higher risk, especially in people with emphysema who have smoked.
- Muscles and bones: loss of muscle mass, weight loss and osteoporosis.
- Mood: anxiety and depression, which are common and treatable.
Important Pages
Questions people usually ask next. Each is answered in full on its own page.
- Who are we?
- Is ANOVA legal?
- Is stem cell therapy safe?
- What is MSC secretome (MSEC)?
- What is BMC (Bone Marrow Concentrate)?
- What are stem cells?
- What should I ask when looking for a stem cell treatment?
- Which conditions do we treat?
- Translational medicine — works in progress
- Targeted triple action in pulmonary fibrosis
Affiliations of ANOVA
ANOVA IRM shares its premises in Offenbach with two further institutions owned by Dr. Stehling: the Institut für Bildgebende Diagnostik (IBDO), providing MRI and CT imaging, and the VITUS PRIVATKLINIK Prof. Dr. Stehling GmbH. Because imaging is carried out in the same building, condition-specific diagnostics — including a CT of the lungs before treatment for COPD where needed — can be performed in-house rather than referred elsewhere. See diagnostics at ANOVA IRM.
References — COPD literature
Literature specific to COPD is listed here. General literature on MSC, secretome and extracellular vesicles is maintained on the MSC secretome page, bone marrow literature on the BMC page.
COPD — definition, frequency, causes and course
- [1] Global Initiative for Chronic Obstructive Lung Disease (GOLD). Global Strategy for the Diagnosis, Management, and Prevention of Chronic Obstructive Pulmonary Disease: 2026 Report. Version 1.3, 8 December 2025. Accessed 21 October 2026. https://goldcopd.org/2026-gold-report-and-pocket-guide/
- [2] Agustí A, Celli BR, Criner GJ, et al. Global Initiative for Chronic Obstructive Lung Disease 2023 Report: GOLD Executive Summary. Eur Respir J. 2023;61(4):2300239. doi:10.1183/13993003.00239-2023. PMID: 36858443.
- [3] World Health Organization. Chronic obstructive pulmonary disease (COPD). Fact sheet, 10 June 2026. Accessed 21 October 2026. https://www.who.int/news-room/fact-sheets/detail/chronic-obstructive-pulmonary-disease-(copd)
- [4] Adeloye D, Song P, Zhu Y, et al. Global, regional, and national prevalence of, and risk factors for, chronic obstructive pulmonary disease (COPD) in 2019: a systematic review and modelling analysis. Lancet Respir Med. 2022;10(5):447–458. doi:10.1016/S2213-2600(21)00511-7. PMID: 35279265.
- [5] Steppuhn H, Kuhnert R, Scheidt-Nave C. 12-month prevalence of known chronic obstructive pulmonary disease (COPD) in Germany. J Health Monit. 2017;2(3):43–50. doi:10.17886/RKI-GBE-2017-065. PMID: 37168950.
- [6] Salvi SS, Barnes PJ. Chronic obstructive pulmonary disease in non-smokers. Lancet. 2009;374(9691):733–743. doi:10.1016/S0140-6736(09)61303-9. PMID: 19716966.
- [7] Strnad P, McElvaney NG, Lomas DA. Alpha1-antitrypsin deficiency. N Engl J Med. 2020;382(15):1443–1455. doi:10.1056/NEJMra1910234. PMID: 32268028.
- [8] Lange P, Celli B, Agustí A, et al. Lung-function trajectories leading to chronic obstructive pulmonary disease. N Engl J Med. 2015;373(2):111–122. doi:10.1056/NEJMoa1411532. PMID: 26154786.
- [9] Hurst JR, Vestbo J, Anzueto A, et al. Susceptibility to exacerbation in chronic obstructive pulmonary disease. N Engl J Med. 2010;363(12):1128–1138. doi:10.1056/NEJMoa0909883. PMID: 20843247.
- [10] Barnes PJ, Burney PGJ, Silverman EK, et al. Chronic obstructive pulmonary disease. Nat Rev Dis Primers. 2015;1:15076. doi:10.1038/nrdp.2015.76. PMID: 27189863.
- [11] Fletcher C, Peto R. The natural history of chronic airflow obstruction. Br Med J. 1977;1(6077):1645–1648. doi:10.1136/bmj.1.6077.1645. PMID: 871704.
Standard of care
- [12] Bundesärztekammer (BÄK), Kassenärztliche Bundesvereinigung (KBV), Arbeitsgemeinschaft der Wissenschaftlichen Medizinischen Fachgesellschaften (AWMF). Nationale VersorgungsLeitlinie COPD – Teilpublikation der Langfassung, 2. Auflage, Version 1. 2021. doi:10.6101/AZQ/000477. AWMF-Register-Nr. nvl-003. https://www.leitlinien.de/copd
- [13] Anthonisen NR, Skeans MA, Wise RA, et al. The effects of a smoking cessation intervention on 14.5-year mortality: a randomized clinical trial. Ann Intern Med. 2005;142(4):233–239. doi:10.7326/0003-4819-142-4-200502150-00005. PMID: 15710956.
- [14] Lipson DA, Barnhart F, Brealey N, et al. Once-daily single-inhaler triple versus dual therapy in patients with COPD. N Engl J Med. 2018;378(18):1671–1680. doi:10.1056/NEJMoa1713901. PMID: 29668352.
- [15] Bhatt SP, Rabe KF, Hanania NA, et al. Dupilumab for COPD with type 2 inflammation indicated by eosinophil counts. N Engl J Med. 2023;389(3):205–214. doi:10.1056/NEJMoa2303951. PMID: 37272521.
- [16] Bhatt SP, Rabe KF, Hanania NA, et al. Dupilumab for COPD with blood eosinophil evidence of type 2 inflammation. N Engl J Med. 2024;390(24):2274–2283. doi:10.1056/NEJMoa2401304. PMID: 38767614.
- [17] European Medicines Agency. Dupixent (dupilumab): EPAR — product information, therapeutic indication COPD. Page updated 18 August 2026. Accessed 21 October 2026. https://www.ema.europa.eu/en/medicines/human/EPAR/dupixent
- [18] McCarthy B, Casey D, Devane D, et al. Pulmonary rehabilitation for chronic obstructive pulmonary disease. Cochrane Database Syst Rev. 2015;(2):CD003793. doi:10.1002/14651858.CD003793.pub3. PMID: 25705944.
- [19] Nocturnal Oxygen Therapy Trial Group. Continuous or nocturnal oxygen therapy in hypoxemic chronic obstructive lung disease: a clinical trial. Ann Intern Med. 1980;93(3):391–398. doi:10.7326/0003-4819-93-3-391. PMID: 6776858.
- [20] Medical Research Council Working Party. Long term domiciliary oxygen therapy in chronic hypoxic cor pulmonale complicating chronic bronchitis and emphysema. Lancet. 1981;1(8222):681–686. doi:10.1016/S0140-6736(81)91970-X. PMID: 6110912.
- [21] Criner GJ, Sue R, Wright S, et al. A multicenter randomized controlled trial of Zephyr endobronchial valve treatment in heterogeneous emphysema (LIBERATE). Am J Respir Crit Care Med. 2018;198(9):1151–1164. doi:10.1164/rccm.201803-0590OC. PMID: 29787288.
Mesenchymal stem cells in COPD — clinical studies (cells, other products than MSEC)
- [22] Stolk J, Broekman W, Mauad T, et al. A phase I study for intravenous autologous mesenchymal stromal cell administration to patients with severe emphysema. QJM. 2016;109(5):331–336. doi:10.1093/qjmed/hcw001. PMID: 26819296.
- [23] Armitage J, Tan DBA, Troedson R, et al. Mesenchymal stromal cell infusion modulates systemic immunological responses in stable COPD patients: a phase I pilot study. Eur Respir J. 2018;51(3):1702369. doi:10.1183/13993003.02369-2017. PMID: 29348155.
- [24] Le Thi Bich P, Nguyen Thi H, Dang Ngo Chau H, et al. Allogeneic umbilical cord-derived mesenchymal stem cell transplantation for treating chronic obstructive pulmonary disease: a pilot clinical study. Stem Cell Res Ther. 2020;11(1):60. doi:10.1186/s13287-020-1583-4. PMID: 32054512.
- [25] Weiss DJ, Casaburi R, Flannery R, et al. A placebo-controlled, randomized trial of mesenchymal stem cells in COPD. Chest. 2013;143(6):1590–1598. doi:10.1378/chest.12-2094. PMID: 23172272.
- [26] Calzetta L, Aiello M, Frizzelli A, et al. Stem cell-based regenerative therapy and derived products in COPD: a systematic review and meta-analysis. Cells. 2022;11(11):1797. doi:10.3390/cells11111797. PMID: 35681492.
Secretome and extracellular vesicles — clinical reports, inhalation and animal studies
- [27] Phinney DG, Pittenger MF. Concise review: MSC-derived exosomes for cell-free therapy. Stem Cells. 2017;35(4):851–858. doi:10.1002/stem.2575. PMID: 28294454.
- [28] Galipeau J, Sensébé L. Mesenchymal stromal cells: clinical challenges and therapeutic opportunities. Cell Stem Cell. 2018;22(6):824–833. doi:10.1016/j.stem.2018.05.004. PMID: 29859173.
- [29] Ridzuan N, Zakaria N, Widera D, et al. Human umbilical cord mesenchymal stem cell-derived extracellular vesicles ameliorate airway inflammation in a rat model of chronic obstructive pulmonary disease (COPD). Stem Cell Res Ther. 2021;12(1):54. doi:10.1186/s13287-020-02088-6. PMID: 33436065.
- [30] Kim YS, Kim JY, Cho R, et al. Adipose stem cell-derived nanovesicles inhibit emphysema primarily via an FGF2-dependent pathway. Exp Mol Med. 2017;49(1):e284. doi:10.1038/emm.2016.127. PMID: 28082743.
- [31] Abbaszadeh H, Ghorbani F, Abbaspour-Aghdam S, et al. Chronic obstructive pulmonary disease and asthma: mesenchymal stem cells and their extracellular vesicles as potential therapeutic tools. Stem Cell Res Ther. 2022;13(1):262. doi:10.1186/s13287-022-02938-5. PMID: 35725505.
- [32] Antunes MA, Braga CL, Oliveira TB, et al. Mesenchymal stromal cells from emphysematous donors and their extracellular vesicles are unable to reverse cardiorespiratory dysfunction in experimental severe emphysema. Front Cell Dev Biol. 2021;9:661385. doi:10.3389/fcell.2021.661385. PMID: 34136481.
- [33] Harrell CR, Miloradovic D, Sadikot R, et al. Molecular and cellular mechanisms responsible for beneficial effects of mesenchymal stem cell-derived product “Exo-d-MAPPS” in attenuation of chronic airway inflammation. Anal Cell Pathol (Amst). 2020;2020:3153891. doi:10.1155/2020/3153891. PMID: 32257769.
- [34] Yusof B, Foo RQ, Ravichandran M, et al. A case report on nebulized human umbilical cord mesenchymal stem cell-derived exosome therapy for asthma and chronic obstructive pulmonary disease: a preliminary clinical evaluation. SAGE Open Med Case Rep. 2026;14:2050313X251386547. doi:10.1177/2050313X251386547. PMID: 41625138.
- [35] Shi MM, Yang QY, Monsel A, et al. Preclinical efficacy and clinical safety of clinical-grade nebulized allogenic adipose mesenchymal stromal cells-derived extracellular vesicles. J Extracell Vesicles. 2021;10(10):e12134. doi:10.1002/jev2.12134. PMID: 34429860.
- [36] Li M, Huang H, Wei X, et al. Clinical investigation on nebulized human umbilical cord MSC-derived extracellular vesicles for pulmonary fibrosis treatment. Signal Transduct Target Ther. 2025;10(1):179. doi:10.1038/s41392-025-02262-3. PMID: 40461474.
Approval status
- [37] U.S. Food and Drug Administration. Approved Cellular and Gene Therapy Products. Content current as of 17 September 2026. Accessed 21 October 2026. https://www.fda.gov/vaccines-blood-biologics/cellular-gene-therapy-products/approved-cellular-and-gene-therapy-products