

Stem Cell Therapy for Neurological and Neurodegenerative Diseases
The ANOVA ALS Stem Cell Secretome
Treatment Programme Germany
An individualised treatment programme combining autologous, adipose tissue-derived MSC secretome (MSEC) therapy with supportive components, for people living with amyotrophic lateral sclerosis (ALS). Offenbach, Germany. Experimental — fully legal — manufactured under German regulatory authorisation and official inspection since 2018.
ALS, also known as motor neuron disease (MND) or Lou Gehrig's disease, progressively destroys the motor neurons that control voluntary movement. ANOVA IRM has been treating people with ALS since 2016 — before a manufacturing authorisation under Section 20c AMG became necessary — and today manufactures MSC secretome (MSEC) in its own facility under official authorisation and officially inspected good professional practice (GFP). GFP is the German counterpart of Good Tissue Practice (GTP) in the US. A registration with the US FDA is, on its own, no official confirmation that the rules are met. In Germany, by contrast, GFP is a condition of the official authorisation and is regularly inspected by the authorities. MSEC is cell-free: it contains the signalling molecules released by the patient's own mesenchymal stromal cells, not the cells themselves. It is administered intrathecally, by lumbar puncture into the cerebrospinal fluid. The programme is offered alongside — never instead of — guideline-based care such as riluzole; see current ALS treatment options.
| Component | Detail |
|---|---|
| Two products | Bone Marrow Concentrate (BMC) and Mesenchymal Stem Cell Secretome (MSEC), each manufactured under official authorisation; no marketing authorisation (experimental) |
| Authorisations | BMC § 20b / § 13 AMG · MSEC § 20b / § 20c AMG (German Medicines Act) |
| Location | Offenbach am Main, Germany |

ALS in brief, the programme and its five components — the essentials at a glance.
You are hereIntroduction & Summary
What is ALS or MND, in brief?
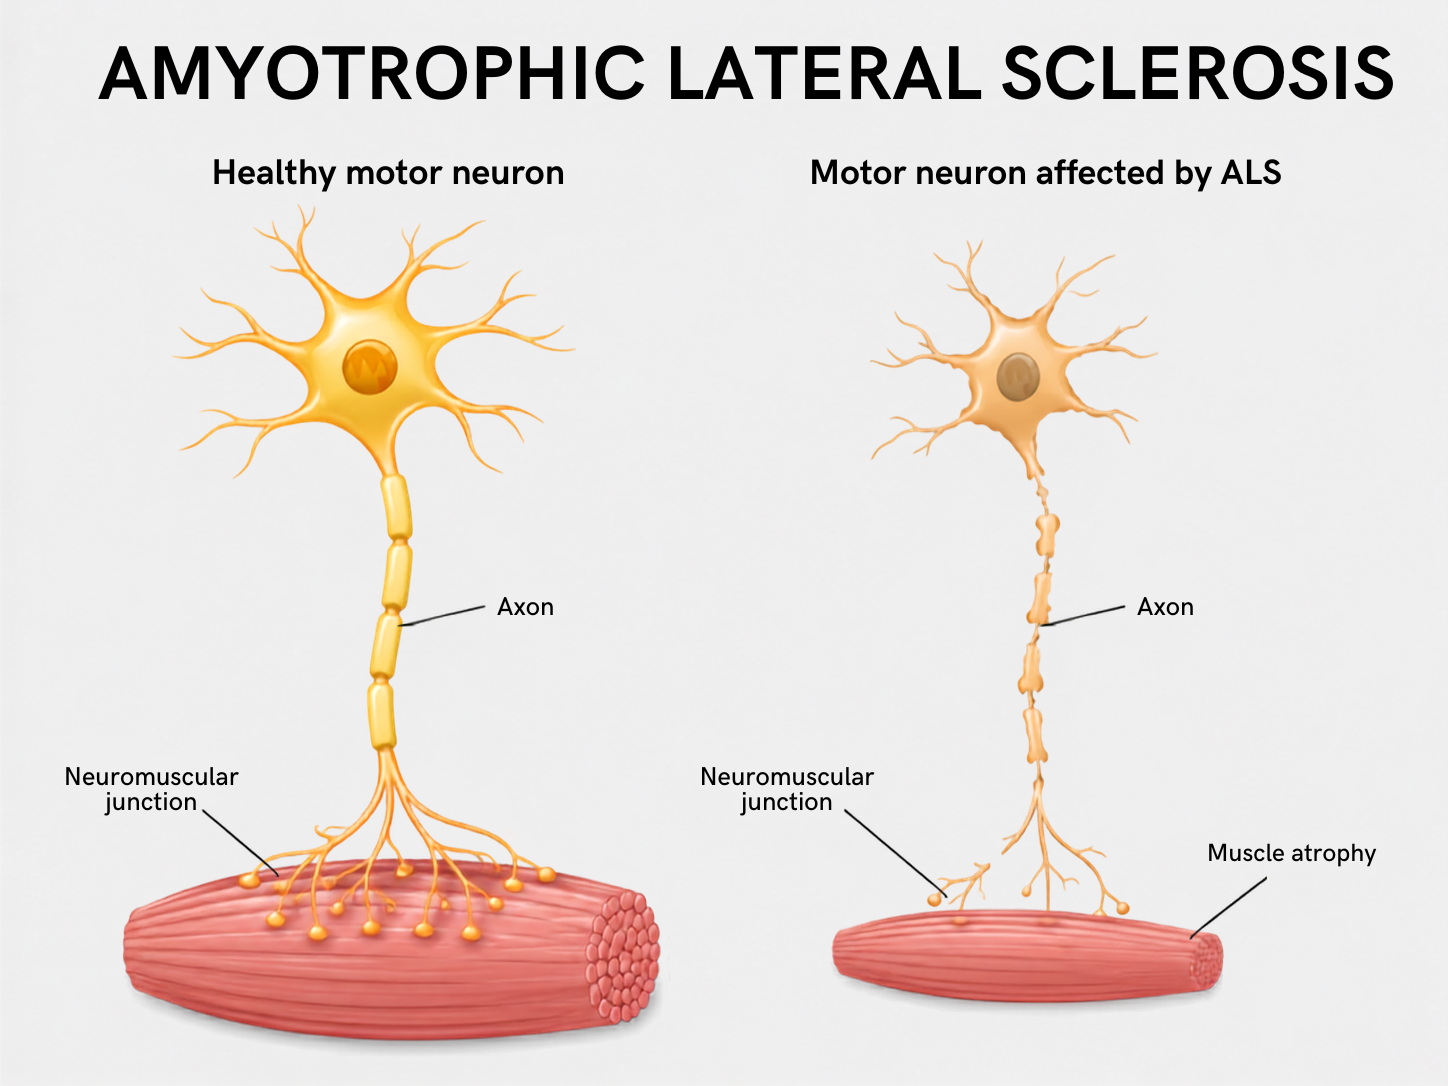
Amyotrophic lateral sclerosis (ALS) is a progressive disease of the motor neurons — the nerve cells that carry movement signals from the brain and spinal cord to the muscles. As upper and lower motor neurons degenerate, muscles weaken and waste (atrophy), affecting mobility, speech, swallowing (dysphagia) and breathing. Early signs often include muscle twitching (fasciculations), weakness in a hand or foot, slurred speech (dysarthria) or cramps.
ALS usually begins in the arms or legs (limb-onset or spinal-onset ALS) or in the muscles for speech and swallowing (bulbar-onset ALS). It progresses at very different speeds; clinicians distinguish fast and slow progressors. About 90% of cases occur without a known family history (sporadic ALS, sALS); the remaining 10% are familial (familial ALS, fALS). Diagnosis rests on clinical examination, electromyography (EMG) and nerve conduction studies, with MRI to exclude other causes. To date no cure is known for amyotrophic lateral sclerosis or motor neuron disease.
Progression is often described with the King's staging system: stages 1 to 3 reflect how many body regions are affected, stage 4 the need for feeding support (gastrostomy) or breathing support.
Common symptoms include weakness in a hand, arm or leg, muscle wasting, cramps and twitching, stiffness, slurred speech, difficulty swallowing and shortness of breath.
More details can be found below in our scientific section on amyotrophic lateral sclerosis.
What is the ANOVA ALS/MND programme?
ANOVA offers autologous MSC secretome (MSEC) therapy for amyotrophic lateral sclerosis. The programme contains MSC secretome, TUDCA, senolytic therapy, gut microbiome analysis and, where appropriate, HAL robotic exoskeleton training. Each component is selected individually; the programme is not a fixed package.
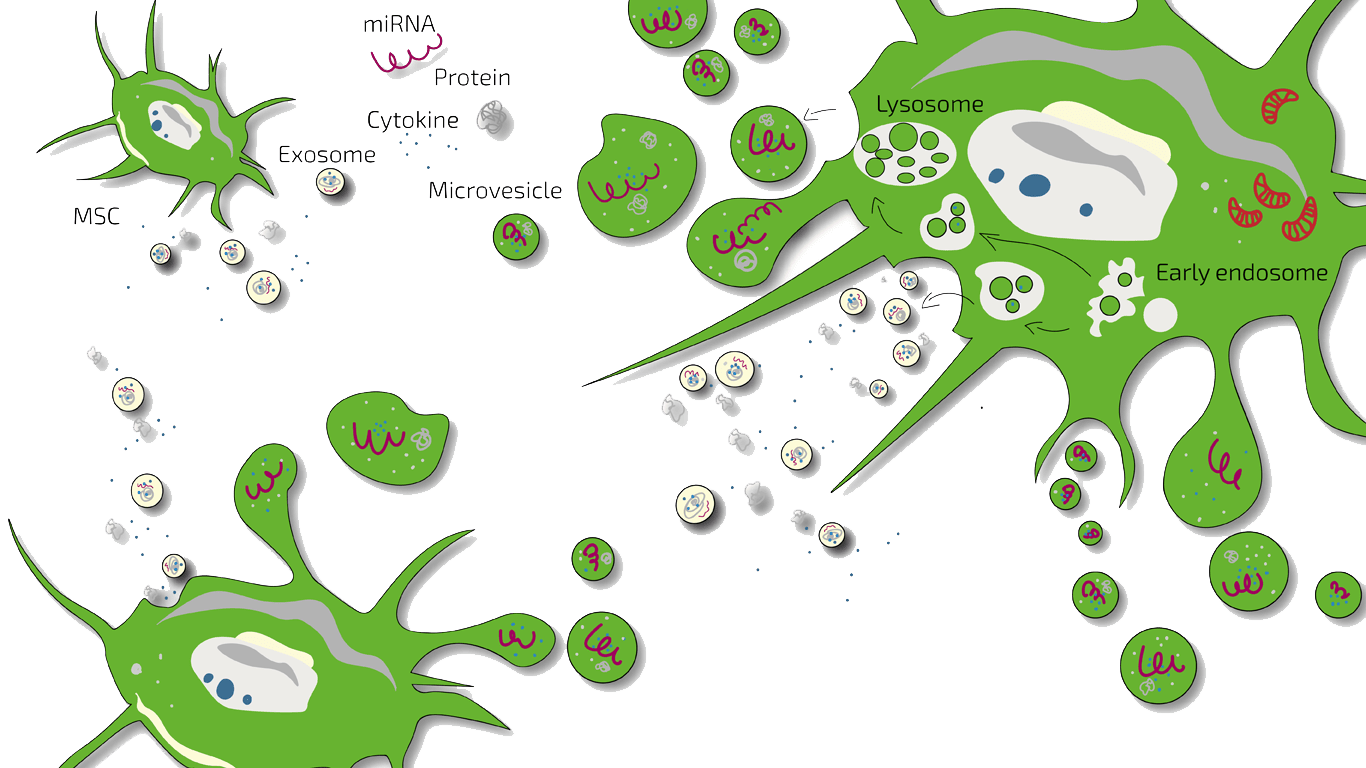
Stem cells are thought to act mainly through soluble factors, together called the secretome, which includes exosomes and many other factors. In ALS and MND, the loss of motor neurons is accompanied by inflammation in their immediate surroundings, driven by supporting cells such as microglia and astrocytes. MSEC is given intrathecally, so the spinal cord and the nerve roots are the structures it reaches best, and it is intended to influence that environment rather than to replace motor neurons.
The ANOVA ALS/MND Programme — Components
MSC Secretome (MSEC)
The signalling molecules released by the patient's own mesenchymal stromal cells, given intrathecally into the cerebrospinal fluid. Laboratory and animal studies suggest they may dampen inflammation and help nerve cells survive. Small external early clinical studies (phase 1/2) with related MSC products given intrathecally mainly examined safety; MSEC itself has not yet been tested in a clinical trial in ALS.
TUDCA (tauroursodeoxycholic acid)
A naturally occurring bile acid under investigation for possible neuroprotective effects; the evidence and why we still use it are set out in the clinical and scientific section below. It is prescribed individually as a pharmacy-compounded preparation (Rezepturarzneimittel) and is not an approved ALS treatment.
Senolytic therapy
Intended to reduce senescent (biologically aged) cells, which release inflammatory signalling molecules. Evidence in ALS so far comes only from laboratory and animal studies; a small external phase 1 study in Alzheimer's disease examined safety. No senolytic compound is approved for ALS, and we do not name individual substances on this website.
Gut microbiome analysis and substitution
Analysis of the gut–brain axis, with personalised dietary or probiotic advice where clinically indicated. External observational studies have found differences in the gut microbiome of people with ALS; that changing it influences the disease has not been proven by clinical studies.
HAL robotic exoskeleton training (optional)
A robotic leg exoskeleton driven by the patient's own residual muscle signals. In an external randomised controlled crossover trial in slowly progressive neuromuscular diseases, including ALS, it improved walking distance; a small external ALS study showed improved step frequency. An optional adjunct, not a substitute for the components above.
What do our own early data show in ALS or MND?
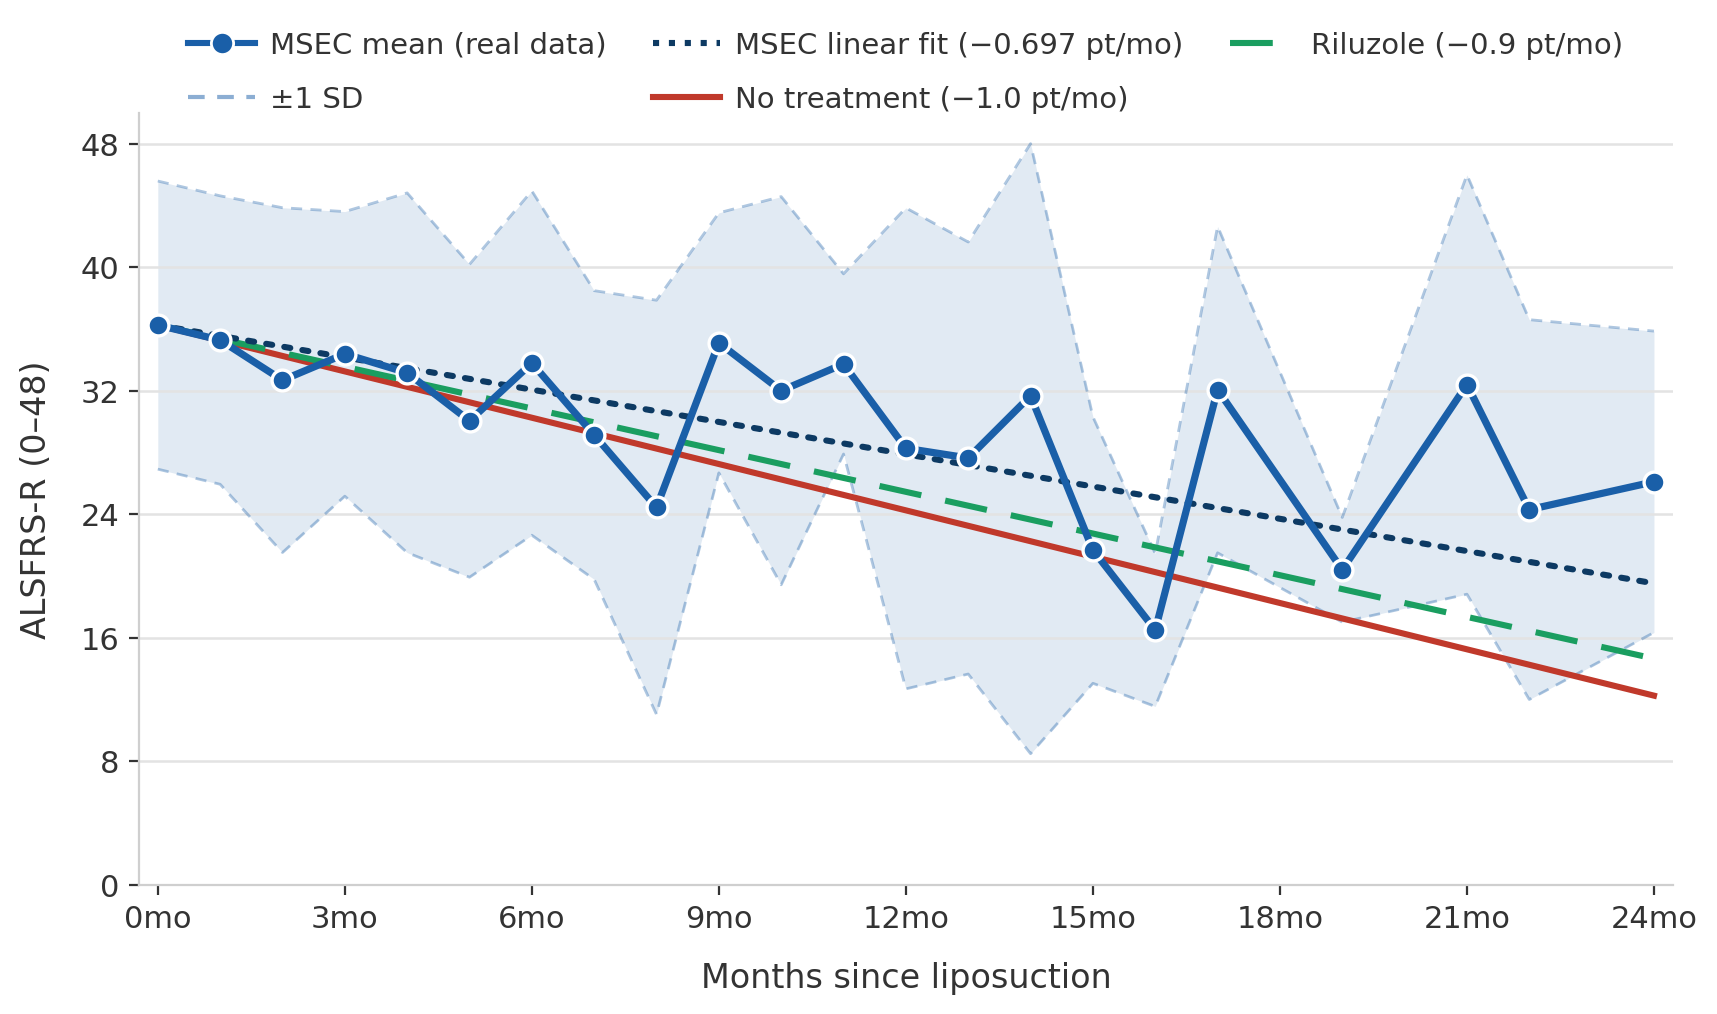
Of the 86 people treated at ANOVA IRM for ALS or MND with MSEC at that time, 69 had enough follow-up data to analyse. In this group, functional decline on the ALSFRS-R was on average about 30% slower than reference rates reported for no treatment, and about 23% slower than reference rates reported for riluzole. This is an early signal, not proof: the finding is not statistically significant, there is no control group, and our patients may not be a typical group.
The full analysis, including every limitation, is in our ALS real-world data report.
Which diagnostics do we use for ALS or MND at ANOVA IRM?
Which tests are used to diagnose ALS or MND?
The diagnosis rests on clinical examination, electromyography (EMG) and nerve conduction studies. MRI of brain and spinal cord, with contrast where needed, serves mainly to exclude other causes, and the El Escorial and Gold Coast criteria structure the assessment. Function is tracked with the ALSFRS-R and breathing with forced vital capacity (FVC); genetic testing and neurofilament light chain (NfL) may be added.
What do we review before ALS or MND treatment at ANOVA IRM?
Before any treatment decision we review your neurological findings, your ALSFRS-R score and your respiratory function. We also assess whether you are fit for the brief sedation required for tissue collection. Where relevant we add genetic testing and gut microbiome analysis.
- Standard: an MRI of the abdominal wall to exclude a hernia is required before the liposuction, taken no more than four weeks beforehand. It can be done at home or at ANOVA IRM.
- Optional: CT guidance for the intrathecal application at ANOVA IRM, used while the dose is given.
- Optional: further MRI scans, with or without contrast, where your ALS or MND situation calls for them — for example to reassess the spine before an application or to follow up another finding.
Imaging can be carried out in-house. The full diagnostic pathway is described on our diagnostics page.
Why ANOVA IRM for ALS or MND?
ANOVA IRM has manufactured MSEC under German regulatory authorisation and official inspection since 2018 and has treated more than 86 people with ALS (September 2026). Why an autologous tissue preparation used only for our own patients requires no marketing authorisation is set out on our regulatory status page.
What can you expect as an ALS or MND patient?
Initial evaluation can begin remotely, by phone or video, without travel to Germany. Treatment itself requires an in-person visit to Offenbach am Main, less than 20 minutes from Frankfurt Airport. You receive an individual written cost estimate before any treatment decision.
Quick answers
Is there a cure for ALS or MND?
No. There is currently no cure for ALS. Standard care combines riluzole, edaravone in some countries, tofersen for people with a SOD1 mutation and multidisciplinary supportive care; beyond this, experimental approaches such as MSC secretome (MSEC) and further gene-targeted therapies are under investigation.
Does stem cell therapy cure ALS or MND?
No. Stem cell therapy is not a cure for ALS. The use of MSC secretome (MSEC) at ANOVA IRM aims to slow functional decline and support the remaining motor neurons, alongside — never instead of — standard treatment such as riluzole.
Is ALS stem cell therapy legal in Germany?
Yes, provided the provider holds the required official authorisations. ANOVA IRM manufactures MSEC for people with ALS under a procurement authorisation (Section 20b AMG) and a manufacturing authorisation under Section 20c AMG, and gives it as an individual treatment attempt. The details are on our regulatory status page.
Is ALS stem cell therapy safe?
Not without qualification: like any medical treatment it carries risks, which your doctor discusses with you in detail before treatment. Safety also depends on the quality of the product. Following the logic of the medicines authorities, a secretome manufactured under official authorisation and inspection is to be regarded as safer than products from unregulated providers. Ask every provider for its authorisations and certificates. More on the regulators' view: unproven therapies.
What medication is used for ALS?
Riluzole is the standard medication for ALS; edaravone is approved in some countries, and tofersen for people with a SOD1 mutation. MSC secretome (MSEC) at ANOVA IRM is offered as a complement to this medication, not as a replacement.
Who qualifies, what the process actually involves, and what it costs — step by step.
You are hereALS/MND Treatment: Eligibility, Process & Cost
MSEC treatment for ALS at ANOVA IRM costs approximately €20,000–€36,000, depending on the number of doses used. It requires a two-day outpatient visit to Offenbach, Germany, for tissue collection, followed by further visits for the applications according to your individual treatment plan. It is available to people with early-to-mid stage ALS who can breathe unassisted.

What does the ALS/MND treatment timeline look like?
- 01
Initial evaluation
Remote, by phone or video — typically 2 weeks to a few months
- 02
Preliminary screening
In your home country, to avoid an unnecessary journey
- 03
First visit — bloodwork and tissue collection
Two-day outpatient visit to Offenbach: bloodwork first, then — if the results are in order — mini-liposuction under brief sedation
- 04
Production and quality control
Approximately 4 weeks; yields 10 doses per production cycle
- 05
Storage
Up to 2 years, allowing an extended personalised schedule
- 06
Application schedule
Set individually: two doses at the start, then one dose every 4–6 weeks, or two doses every 3 months
Who qualifies for ALS/MND treatment, and what are the requirements?
We treat people in the early to mid stage of ALS who can breathe unassisted and are medically fit for the brief sedation required to collect fat tissue. We treat both fast and slow progressors. Every treatment recommendation follows a full clinical evaluation: medical history, neurological status, ALSFRS-R, respiratory function and, where relevant, genetic or microbiome testing.
What are the contraindications for ALS or MND treatment?
Our treatments are experimental. We treat only people for whom, after medical assessment, we consider the benefit-risk balance to support treatment.
Applies to all ANOVA treatments:
- Active cancer within the last two years
- Under the age of legal majority
- Pregnancy or breastfeeding
- Active infectious disease (hepatitis A, B, C, HIV, syphilis or other)
Specific to ALS:
- Unable to breathe unaided, or requiring a ventilator
- Difficulty breathing in the supine position
- Dysphagia (severe difficulty swallowing)
- Psychiatric disorder that would prevent informed consent or cooperation
What does ALS/MND therapy at ANOVA IRM involve, step by step?
What screening is needed before you travel for ALS or MND treatment?
Before you travel, a preliminary screening in your home country — usually a blood test for medical or infectious-disease factors that would prevent treatment — helps you avoid an unnecessary journey.
What happens at your first ALS or MND visit to Offenbach, Germany?
The first treatment visit takes about two days in Offenbach, on an outpatient basis. It begins with bloodwork at ANOVA IRM; if the results are in order, a small amount of abdominal fat tissue is collected by mini-liposuction under brief sedation. From this point to the first secretome application is usually four to six weeks.
How is your MSEC for ALS or MND produced and quality-controlled?
Mesenchymal stromal cells are isolated from the collected tissue and expanded under controlled conditions in our own facility in Offenbach, under official authorisation and officially inspected good professional practice (GFP). These cells are then used to produce your MSEC preparation — the signalling molecules they release, not the living cells. Production and quality control take approximately four weeks and yield 10 doses per production cycle. Each patient batch is tested with methods validated according to the European Pharmacopoeia (Ph. Eur.) and GMP, and released under a documented procedure; the released secretome is stored at −80 °C and keeps for up to two years.
How often is MSEC applied in ALS or MND?
Because ALS is a chronic, progressive disease for which there is currently no cure, we recommend a longer-term treatment using all 10 doses produced rather than a single application; see the timeline above.
The schedule is set individually for each patient, for example:
- At the start: two intrathecal doses.
- If you live close by: a single MSEC dose every 4 to 6 weeks.
- If you live further away: a double dose every 3 months — about five visits over 15 months for the 10 doses produced.
- Standard route for ALS: intrathecal, by lumbar puncture into the cerebrospinal fluid. This is intended to bring the secretome closer to the spinal cord and brain than an infusion into the bloodstream, which would have to cross the blood–brain barrier.
- Individual alternative: intravenous, if you specifically wish it or if systemic treatment is medically necessary.
Intrathecal applications are standard procedures when performed by experienced physicians; where the anatomy requires it, ANOVA IRM uses CT guidance from its in-house radiology. The benefit-risk assessment of intrathecal administration is set out on a separate page.
What does ALS/MND treatment with MSEC cost?
MSEC treatment for ALS costs approximately €20,000 to €36,000 and is billed according to the German Medical Fee Schedule (GOÄ). The base package — the mini-liposuction and the first three MSEC doses — costs approximately €20,000; each further dose is charged separately at approximately €2,250 to €2,350 depending on the application route. Because we recommend using all 10 doses over a longer period for a chronic, progressive disease such as ALS, most treatment plans end up at the upper end of this range. The total also depends on additional examinations and your sedation or anaesthesia preferences. You receive an individual written estimate before any treatment decision. Travel, accommodation and other personal expenses are separate. Experimental ALS treatment is generally self-funded; you can still ask your insurer about possible reimbursement. All prices are subject to change.
Because ALS is a chronic, progressive disease, a double liposuction can be recommended: it yields 20 doses, which can be used over the current shelf life of two years from a single collection. The cost is correspondingly higher and is shown in your individual estimate.
Why does the cost of ALS or MND treatment vary with the application route?
All treatments at ANOVA IRM are billed according to the German Medical Fee Schedule (Gebührenordnung für Ärzte, GOÄ); within it, the cost varies mainly with the route of application. For ALS we mainly administer MSEC intrathecally, because in our assessment it is most likely to act there: the cerebrospinal fluid is a small, closed compartment in direct contact with the spinal cord and brain. We use intravenous administration only if you specifically wish it or if systemic treatment is medically necessary. The exact cost of your treatment plan is set out in your individual written cost estimate.
Frequently asked questions — eligibility, process and travel
How is MSEC administered for ALS or MND?
By intrathecal injection via lumbar puncture into the cerebrospinal fluid. Treatment starts with two doses. If you live close by, a single dose every 4 to 6 weeks is usual; otherwise a double dose every 3 months.
How long does the whole ALS or MND process take?
Initial evaluation can begin remotely and takes from about two weeks to several months. Tissue collection takes about two days in Offenbach, followed by approximately four weeks of production and quality control.
Does health insurance cover ALS or MND stem cell therapy in Germany?
No. Experimental ALS treatment is almost always paid for privately; an insurer may review an individual request, but reimbursement should not be expected.
Should I stop my current ALS medication such as riluzole?
No. The programme complements guideline-based care. Please continue to work with your treating neurologist throughout.
Should I continue my existing ALS treatment such as riluzole?
Yes. The programme complements established neurological care rather than replacing it.
How often do I need to travel to Germany for ALS stem cell treatment?
Usually about five times over 15 months. After a remote first evaluation, one two-day visit to Offenbach is needed for bloodwork and tissue collection. Applications then follow every 4 to 6 weeks as a single dose if you live close by, or otherwise as a double dose every 3 months. Offenbach is less than 20 minutes from Frankfurt Airport. The full sequence is described on the MSC secretome page.
What medical records should I send for an ALS assessment?
Please send us your most recent documents; we will ask if we need anything else. Helpful are, for example, your neurologist's letters with the confirmed diagnosis and your EMG and nerve conduction results. MRI reports and images, your latest ALSFRS-R score, lung function (FVC), genetic test results and a current medication list are useful too. Large image files can be sent electronically; our patient care team will tell you how.
Does ANOVA IRM treat international patients with ALS?
Yes. Consultations are held in English, and the first assessment of your ALS takes place by phone or video, before any travel is needed.
ALS biology, the rationale behind each component, our real-world data and all references.
You are hereALS/MND: Clinical & Scientific Evidence
1. What happens in ALS or MND?
ALS is now widely regarded as a complex disorder involving multiple interacting pathways rather than a single mechanism.[29] Onset is limb (spinal) or bulbar, and the rate of progression differs widely between fast and slow progressors.[30] Diagnosis follows criteria such as El Escorial and Gold Coast. Function is measured on the ALSFRS-R and respiratory function on forced vital capacity (FVC); neurofilament light chain (NfL) is used as a biomarker of neuronal damage.[30]
What causes ALS, and what are the risk factors?
The cause is not known in most cases. ALS is understood as a complex disorder in which genetic predisposition and environmental factors interact. What triggers the disease and what drives its progression are two different questions; the next section deals with progression.[28],[29],[30]
- Age: onset is most common between 55 and 75 years.
- Sex: men are affected somewhat more often than women, and the difference narrows with age.
- Family history: about 10% of cases are familial, with variants in genes such as SOD1, C9orf72, TARDBP and FUS.[29]
- Genetic variants without family history: the same variants are also found in some people with no affected relatives.
- Discussed, not established: smoking, military service, intense physical activity and certain occupational exposures have been discussed as risk factors; the evidence is mixed.[30]
What drives the progression of ALS or MND?
The cause of ALS is unknown, and the drivers of progression are a separate question. Motor neurons are thought to be where the disease begins, while the cells around them — microglia and astrocytes — shape how fast it advances. They maintain a local inflammatory response and release mediators that add to the damage.[17],[18]
Further processes contribute: oxidative stress, mitochondrial dysfunction, impaired protein homeostasis and disturbed energy metabolism.[20],[23],[29] This is where our programme aims — at the course of the disease, not at its cause, and not at a cure.
2. What is the guideline-based standard of care for ALS or MND?
Riluzole can modestly prolong survival, with benefit varying between individuals, and may cause gastrointestinal symptoms and elevated liver enzymes.[1],[2],[3],[4],[5] Edaravone is approved in several countries for selected patients.[6] Tofersen is approved for patients with a SOD1 mutation.[7] Sodium phenylbutyrate with taurursodiol showed a benefit in an external phase 2 trial that was not confirmed in the external phase 3 trial; the product has since been withdrawn.[12],[13] Multidisciplinary supportive care remains essential throughout: physiotherapy, occupational therapy, speech and language therapy, nutritional support including PEG feeding where needed, and respiratory support such as non-invasive ventilation (NIV) and cough assistance.[30] The ANOVA programme is offered alongside these therapies, not in place of them.
How is ALS or MND diagnosed, and what do we not do ourselves?
The diagnosis of ALS or MND is made by neurologists, not by us. The standard work-up includes clinical examination, electromyography (EMG) and nerve conduction studies, MRI of brain and spinal cord to exclude other causes, blood tests, sometimes examination of the cerebrospinal fluid, and genetic testing where indicated. Assessment follows the El Escorial and Gold Coast criteria, and progression is tracked with the ALSFRS-R and lung function.
What we do ourselves is imaging: MRI with or without contrast, and CT guidance for an intrathecal application. This is carried out at the Institut für Bildgebende Diagnostik in the same building, which also belongs to Dr. Stehling. We do not perform EMG, nerve conduction studies or the neurological diagnosis itself; please bring these findings from your neurologist.
3. What is the scientific rationale for ALS and MND treatment, component by component?
MSC secretome (MSEC)
MSEC uses the signalling molecules released by mesenchymal stromal cells — growth factors, cytokines, extracellular vesicles — rather than living cells.[10],[11] Small external phase 1 and phase 1/2 studies with related MSC products given intrathecally mainly examined safety and reported acceptable tolerability.[8],[9] External phase 3 trials with two such cell products (NurOwn, NeuroNata-R) did not meet their primary endpoints in the full study population.[34] MSEC itself has not yet been tested in a clinical trial in ALS; our own real-world data are set out in section 4.
What is the efficacy hypothesis behind MSC secretome in ALS and MND?
ALS is regarded as a non-cell-autonomous disease: the onset is thought to lie in the motor neurons, while supporting cells drive the progression. Activated microglia and astrocytes maintain a local inflammatory response, migrate to the site of injury and release inflammatory mediators.[17]
In the SOD1-G93A mouse model, removing three factors released by microglia — IL-1α, TNFα and C1q — markedly extended survival, which identifies the microglia-to-astrocyte axis as a strong driver of progression.[18] Astrocytes also carry the main glutamate transporter EAAT2, and its loss alone causes severe motor neuron damage.[17]
The hypothesis behind MSEC is that its soluble factors influence this environment rather than the motor neuron itself. Two limitations belong with it: anti-inflammatory approaches have so far had only modest effects in ALS, and the cause of the disease remains unknown. Our aim is to slow progression, not to cure the disease.
TUDCA
A bile acid studied for possible effects on mitochondrial function, endoplasmic reticulum stress and apoptosis.[12],[14],[15] In the external phase 3 trial TUDCA-ALS, TUDCA added to riluzole showed no benefit over placebo after 18 months; the results were reported in 2024.[16] TUDCA is not an approved ALS treatment.
Why do we still use TUDCA? Talk to us about it.
Gut microbiome
External observational studies report differences in gut microbiome composition between people with ALS and healthy individuals; that changing the microbiome influences ALS has not been proven by clinical studies.[19]–[23]
Cellular senescence and senolytics
Senescent cells stop dividing but continue releasing inflammatory signalling molecules.[25],[26] In animal models, senolytic compounds have reduced the number of senescent cells; a small external phase 1 study in Alzheimer's disease examined safety.[24] In an ALS mouse model, removing senescent cells with engineered immune cells did not improve motor function or survival.[27] No senolytic compound is approved for ALS, and we do not name individual substances on this website.
HAL robotic exoskeleton training
An external multicentre randomised controlled crossover trial across nine Japanese hospitals found that cybernic treatment with HAL significantly improved ambulatory function in patients with slowly progressive rare neuromuscular diseases.[31] In a small external ALS study, a full course of HAL training significantly improved gait cadence on the 10-metre walk test, although gait speed and step length were not significantly affected.[32] A small external study in limb-girdle muscular dystrophy found HAL-supported treadmill training safe and feasible.[33]
Talk to us about current changes or additions to the programme. For a number of conditions ANOVA IRM also offers infusion therapies alongside the components described above.
4. Where does our own ALS and MND evidence stand?
In 2026 we had treated 86 people with a diagnosis of ALS or MND with MSEC since 2016 and tracked functional ability on the ALSFRS-R. Of these, 69 had enough follow-up data; these were analysed. In this group, decline was on average about 30% slower than published reference rates for no treatment and about 23% slower than published rates for riluzole.
What this does not yet tell us
- It is not statistically significant. With this number of patients we cannot rule out chance.
- There is no control group. We compare our patients with published rates from other studies, not with a matched untreated group.
- Our patients may not be a typical group. People who return for repeated treatments over months or years tend to be doing relatively well.
- ALS varies enormously between people, which makes small studies hard to interpret.
How this compares with riluzole
Riluzole's approval and status as standard of care rest on large controlled trials and real-world data showing a statistically significant survival benefit, together with decades of safety experience.[1],[4] Its evidence base is substantially stronger than what we have for MSEC today. We say this plainly rather than imply the two are on equal footing.
What comes next
As a private treatment centre we are not in a position to sponsor a randomised clinical trial. We continue to treat individually, collect data on everyone we treat, and evaluate that data against the growing published literature, including its limitations.
5. Legal framework for MSEC in ALS/MND
MSEC is an autologous tissue preparation. ANOVA IRM manufactures it under a procurement authorisation (Section 20b AMG) and a manufacturing authorisation under Section 20c AMG, issued and regularly inspected by the Hessian State Office for Health and Care (HLfGP). The individual treatment attempt (individueller Heilversuch) concerns the administration only and follows full disclosure and informed consent; because the product is used only for ANOVA IRM's own patients, no authorisation under Section 4b, no marketing authorisation under Section 21 and no approval under Section 21a AMG is required. The full derivation is on our regulatory status page.
6. Frequently asked questions — ALS or MND, evidence and approval status
Is stem cell therapy approved for ALS or MND anywhere?
Yes, in one country and only conditionally. In South Korea, NeuroNata-R (lenzumestrocel), an autologous bone marrow-derived MSC product, has held conditional approval since 2013/2014.[35] Its phase 3 trial (ALSUMMIT)[36] missed its primary endpoint in the full study population; a post hoc analysis showed benefit in slower-progressing patients. According to the manufacturer, the Korean Ministry of Food and Drug Safety updated the label with these data in May 2026 and kept the conditional approval. In Germany and the EU, no stem cell therapy is approved for ALS. NeuroNata-R contains living cells and is a different product from ANOVA's cell-free MSEC.
Are MSC studies evidence that MSEC works in ALS or MND?
No. They provide a scientific rationale and indirect evidence, not proof. Proof of efficacy requires a randomised controlled phase 3 trial with the specific product; no such trial exists for MSEC. The reasoning behind a cell-free product is set out on the MSC secretome page.
What type of stem cell therapy does ANOVA use for ALS or MND?
An autologous MSC secretome (MSEC) produced from the patient's own mesenchymal stromal cells. The final preparation is cell-free.
What are the symptoms of ALS or MND?
The main symptoms of ALS are progressive muscle weakness and wasting with twitching and cramps and, depending on where the disease begins, difficulties with speech, swallowing and breathing. Symptoms depend on which motor neurons are affected first, and they change as the disease progresses. Most people notice weakness in one region before others follow.
Movement and muscle
- weakness in a hand, arm or leg, usually starting on one side
- muscle wasting, cramps and visible twitching (fasciculations)
- stiffness and spasticity, with brisk reflexes
- unsteady gait and frequent stumbling or falls
Speech, swallowing and breathing
- slurred or slowed speech, sometimes a nasal voice (bulbar onset)
- difficulty swallowing, with coughing while eating or drinking
- shortness of breath on exertion or when lying flat, and disturbed sleep
- weak cough and difficulty clearing secretions
Other symptoms
- excess saliva or, conversely, a dry mouth
- uncontrolled laughing or crying that does not match the situation (pseudobulbar affect)
- weight loss and fatigue
- in a minority, changes in behaviour, language or executive function; a small proportion develop frontotemporal dementia
Sensation, vision, hearing and bladder function are usually preserved, and eye movements are often spared until late.[30]
Which forms of ALS and MND are there, and how do they progress?
The main forms are sporadic and familial ALS and, by where it begins, limb-onset and bulbar-onset ALS; the course varies widely between people. ALS is one of several conditions grouped as motor neuron disease (MND). The course differs widely, which is why clinicians distinguish fast and slow progressors.
- Sporadic ALS (sALS): about 90% of cases, without a known family history.
- Familial ALS (fALS): about 10% of cases, linked to inherited gene variants.[29]
- Limb-onset (spinal-onset) ALS: begins in an arm or leg; the more common presentation.
- Bulbar-onset ALS: begins with speech and swallowing; on average it progresses faster.
- Related MND forms: primary lateral sclerosis (PLS), progressive muscular atrophy (PMA) and progressive bulbar palsy (PBP) affect upper or lower motor neurons selectively and usually progress more slowly.
Progression is tracked with the ALSFRS-R and with respiratory function (FVC); King's staging describes how many body regions are involved and when nutritional or respiratory support becomes necessary.[30]
What complications can ALS or MND cause?
As the disease progresses, complications arise mainly from weakness of the muscles for breathing, swallowing and movement. Respiratory insufficiency, aspiration and pneumonia, malnutrition and weight loss, immobility with pressure sores and thrombosis, pain from stiffness and joint contractures, and disturbed sleep are the most common. Non-invasive ventilation, a feeding tube (PEG) and multidisciplinary care address these complications and can improve quality of life.[30]
Important Pages
Questions people usually ask next. Each is answered in full on its own page.
- Who are we?
- Is ANOVA legal?
- Is stem cell therapy safe?
- What is MSC secretome (MSEC)?
- What is BMC (Bone Marrow Concentrate)?
- What are stem cells?
- What should I ask when looking for a stem cell treatment?
- Which conditions do we treat?
- Benefit-risk assessment of intrathecal administration
- Does the secretome pass the blood–brain barrier?
- HAL robotic exoskeleton training
- ALS treatment options — standard and emerging
- ALS real-world data report
Affiliations of ANOVA
ANOVA IRM shares its premises in Offenbach with two further institutions owned by Dr. Stehling: the Institut für Bildgebende Diagnostik (IBDO), providing MRI and CT imaging, and the Vitus Prostate Center. Because imaging is carried out in the same building, condition-specific diagnostics — including CT-guided procedures — can be performed in-house rather than referred elsewhere. See diagnostics at ANOVA IRM.
References — ALS-specific literature
Current standard therapy for ALS
- [1] Bensimon G, Lacomblez L, Meininger V. A controlled trial of riluzole in amyotrophic lateral sclerosis. N Engl J Med. 1994;330(9):585–591. doi:10.1056/NEJM199403033300901. PMID: 8302340.
- [2] Miller RG, Mitchell JD, Moore DH. Riluzole for amyotrophic lateral sclerosis (ALS)/motor neuron disease (MND). Cochrane Database Syst Rev. 2012;(3):CD001447.
- [3] Fang T, Al Khleifat A, Meurgey JH, et al. Stage at which riluzole treatment prolongs survival in patients with amyotrophic lateral sclerosis: a retrospective analysis of data from a dose-ranging study. Lancet Neurol. 2018;17(5):416–422. doi:10.1016/S1474-4422(18)30054-1. PMID: 29525492.
- [4] Andrews JA, Jackson CE, Heiman-Patterson TD, et al. Real-world evidence of riluzole effectiveness in treating amyotrophic lateral sclerosis. Amyotroph Lateral Scler Frontotemporal Degener. 2020;21(7-8):509–518. doi:10.1080/21678421.2020.1771734. PMID: 32573277.
- [5] Thakore NJ, Lapin BR, Mitsumoto H; PRO-ACT Consortium. Early initiation of riluzole may improve absolute survival in amyotrophic lateral sclerosis. Muscle Nerve. 2022;66(6):702–708. doi:10.1002/mus.27724. PMID: 36117390.
- [6] Writing Group; Edaravone (MCI-186) ALS 19 Study Group. Safety and efficacy of edaravone in well defined patients with amyotrophic lateral sclerosis: a randomised, double-blind, placebo-controlled trial. Lancet Neurol. 2017;16(7):505–512. doi:10.1016/S1474-4422(17)30115-1. PMID: 28522181.
- [7] Miller TM, Cudkowicz ME, Genge A, et al. Trial of antisense oligonucleotide tofersen for SOD1 ALS. N Engl J Med. 2022;387(12):1099–1110. doi:10.1056/NEJMoa2204705. PMID: 36129998.
Mesenchymal stromal cells and regenerative medicine
- [8] Oh KW, Moon C, Kim HY, et al. Phase I trial of repeated intrathecal autologous bone marrow-derived mesenchymal stromal cells in amyotrophic lateral sclerosis. Stem Cells Transl Med. 2015;4(6):590–597. doi:10.5966/sctm.2014-0212. PMID: 25934946.
- [9] Petrou P, Gothelf Y, Argov Z, et al. Safety and clinical effects of mesenchymal stem cells secreting neurotrophic factor transplantation in patients with amyotrophic lateral sclerosis: results of phase 1/2 and 2a clinical trials. JAMA Neurol. 2016;73(3):337–344. doi:10.1001/jamaneurol.2015.4321. PMID: 26751635.
- [10] Gugliandolo A, Bramanti P, Mazzon E. Mesenchymal stem cells: a potential therapeutic approach for amyotrophic lateral sclerosis? Stem Cells Int. 2019;2019:3675627. doi:10.1155/2019/3675627. PMCID: PMC6431432.
- [11] Deng S, et al. Cell-based regenerative and rejuvenation strategies for treating neurodegenerative diseases. Stem Cell Res Ther. 2025;16:167. PMID: 40189500.
TUDCA and neuroprotection
- [12] Paganoni S, Macklin EA, Hendrix S, et al. Trial of sodium phenylbutyrate–taurursodiol for amyotrophic lateral sclerosis (CENTAUR, phase 2). N Engl J Med. 2020;383(10):919–930. doi:10.1056/NEJMoa1916945. PMID: 32877582.
- [13] PHOENIX trial of sodium phenylbutyrate–taurursodiol in ALS (ClinicalTrials.gov NCT05021536). Topline results, March 2024: primary endpoint not met, no significant difference in secondary endpoints; the product was subsequently withdrawn from the market. Manufacturer announcement; no peer-reviewed full publication as of September 2026.
- [14] Albanese A, et al. Tauroursodeoxycholic acid in patients with amyotrophic lateral sclerosis: the TUDCA-ALS trial protocol. Front Neurol. 2022;13:1009113. PMID: 36237618.
- [15] Lombardo FL, Spila Alegiani S, Mayer F, et al. A randomized double-blind clinical trial on safety and efficacy of tauroursodeoxycholic acid (TUDCA) as add-on treatment in patients affected by amyotrophic lateral sclerosis (ALS): the statistical analysis plan of TUDCA-ALS trial. Trials. 2023;24:792. doi:10.1186/s13063-023-07638-w.
- [16] TUDCA-ALS trial (ClinicalTrials.gov NCT03800524). Topline results, March 2024: the phase 3 trial did not meet its primary endpoint (ALSFRS-R slope after 18 months); no differences were seen in secondary endpoints including survival. Announcement by the TUDCA-ALS consortium; no peer-reviewed publication of the results was available as of September 2026.
Glia and non-cell-autonomous mechanisms
- [17] Lee J, Hyeon SJ, Im H, et al. Astrocytes and microglia as non-cell-autonomous players in the pathogenesis of ALS. Exp Neurobiol. 2016;25(5):233–240. doi:10.5607/en.2016.25.5.233. PMID: 27790057.
- [18] Guttenplan KA, Weigel MK, Adler DI, et al. Knockout of reactive astrocyte activating factors slows disease progression in an ALS mouse model. Nat Commun. 2020;11:3753. doi:10.1038/s41467-020-17514-9. PMID: 32719333.
Gut–brain axis and the ALS microbiome
- [19] Cryan JF, O'Riordan KJ, Cowan CSM, et al. The microbiota-gut-brain axis. Physiol Rev. 2019;99(4):1877–2013. doi:10.1152/physrev.00018.2018. PMID: 31460832.
- [20] Cryan JF, O'Riordan KJ, Sandhu K, Peterson V, Dinan TG. The gut microbiome in neurological disorders. Lancet Neurol. 2020;19(2):179–194. doi:10.1016/S1474-4422(19)30356-4. PMID: 31753762.
- [21] Dandamudi BJ, Dimaano KAM, Shah N, et al. Neurodegenerative disorders and the gut-microbiome-brain axis: a literature review. Cureus. 2024;16(10):e72427. doi:10.7759/cureus.72427.
- [22] Liu X, Liu Y, Liu J, et al. Correlation between the gut microbiome and neurodegenerative diseases: a review of metagenomics evidence. Neural Regen Res. 2024;19(4):833–845. doi:10.4103/1673-5374.382223. PMID: 37843219.
- [23] Yang EJ. The emerging role of the brain–gut axis in amyotrophic lateral sclerosis: pathogenesis, mechanisms, and therapeutic perspectives. Int J Mol Sci. 2025;26(17):8419. doi:10.3390/ijms26178419. PMID: 40943341.
Cellular senescence and healthy ageing
- [24] Gonzales MM, Garbarino VR, Kautz TF, et al. Senolytic therapy in mild Alzheimer's disease: a phase 1 feasibility trial. Nat Med. 2023;29(10):2481–2488. doi:10.1038/s41591-023-02543-w. PMID: 37679434.
- [25] Tan X, Gao N. The emerging role of cellular senescence in amyotrophic lateral sclerosis. Front Neurosci. 2025;19:1599492. doi:10.3389/fnins.2025.1599492.
- [26] Tsang VSK, Malaspina A, Henson SM. The metabolic intersection between immunosenescence and neuroinflammation in amyotrophic lateral sclerosis. J Inflamm (Lond). 2025;22:36. doi:10.1186/s12950-025-00460-y. PMID: 40866928.
- [27] Fang L, Bai Z, Yang D, et al. Elimination of senescent cells fails to attenuate disease progression in an ALS mouse model. Neurol Sci. 2026;47:411. doi:10.1007/s10072-026-09023-2.
Translational medicine and ALS genetics
- [28] Bedlack R, Li X, Evangelista BA, et al. The scientific and therapeutic rationale for off-label treatments in amyotrophic lateral sclerosis. Ann Neurol. 2025;97(1):15–27. doi:10.1002/ana.27126. PMID: 39503319.
- [29] Mejzini R, Flynn LL, Pitout IL, et al. ALS genetics, mechanisms, and therapeutics: where are we now? Front Neurosci. 2019;13:1310. doi:10.3389/fnins.2019.01310. PMID: 31866818.
- [30] van Es MA, Hardiman O, Chio A, et al. Amyotrophic lateral sclerosis. Lancet. 2017;390(10107):2084–2098. doi:10.1016/S0140-6736(17)31287-4. PMID: 28552366.
HAL robotic exoskeleton training
- [31] Nakajima T, Sankai Y, Takata S, et al. Cybernic treatment with wearable cyborg Hybrid Assistive Limb (HAL) improves ambulatory function in patients with slowly progressive rare neuromuscular diseases: a multicentre, randomised, controlled crossover trial for efficacy and safety (NCY-3001). Orphanet J Rare Dis. 2021;16(1):304. PMID: 34233722.
- [32] Morioka H, Hirayama T, Sugisawa T, et al. Robot-assisted training using hybrid assistive limb ameliorates gait ability in patients with amyotrophic lateral sclerosis. J Clin Neurosci. 2022;99:158–163. PMID: 35279589.
- [33] Sczesny-Kaiser M, Kowalewski R, Schildhauer TA, et al. Treadmill training with HAL exoskeleton — a novel approach for symptomatic therapy in patients with limb-girdle muscular dystrophy — preliminary study. Front Neurosci. 2017;11:449. PMID: 28848377.
Mesenchymal stromal cell products — phase 3
- [34] Cudkowicz ME, Lindborg SR, Goyal NA, et al. A randomized placebo-controlled phase 3 study of mesenchymal stem cells induced to secrete high levels of neurotrophic factors in amyotrophic lateral sclerosis (NurOwn). Muscle Nerve. 2022;65(3):291–302. doi:10.1002/mus.27472. PMID: 34890069.
- [35] Nam JY, Chun S, Lee TY, et al. Long-term survival benefits of intrathecal autologous bone marrow-derived mesenchymal stem cells (Neuronata-R®: lenzumestrocel) treatment in ALS: propensity-score-matched control, surveillance study. Front Aging Neurosci. 2023;15:1148444. doi:10.3389/fnagi.2023.1148444. PMID: 37122380 (manufacturer-affiliated study with an external control group from the PRO-ACT database; conditional approval by the Korean MFDS in 2013).
- [36] Nam JY, Lee TY, Kim K, et al. Efficacy and safety of lenzumestrocel (Neuronata-R® inj.) in patients with amyotrophic lateral sclerosis (ALSUMMIT study): study protocol for a multicentre, randomized, double-blind, parallel-group, sham procedure-controlled, phase III trial. Trials. 2022. doi:10.1186/s13063-022-06327-4.
General MSC, extracellular vesicle and secretome literature is maintained on the MSC secretome page; bone marrow literature on the BMC page.
Last medically reviewed on 23 September 2026