

Stem Cell Therapy for Erectile Dysfunction
The ANOVA ED Stem Cell Treatment Programme Germany
An individualised treatment programme combining autologous bone marrow concentrate (BMC) or cell-free MSC secretome (MSEC) therapy with supportive components, for men with erectile dysfunction (ED). The product is chosen case by case. Offenbach, Germany. Experimental — fully legal — manufactured under German regulatory authorisation and official inspection since 2018.
Erectile dysfunction (ED) affects about half of all men between the ages of 40 and 70 to some degree.[2] In most men a physical cause can be found, such as cardiovascular disease, diabetes mellitus, side effects of medication or nerve damage after surgical removal of the prostate.[1] ANOVA IRM manufactures BMC under good manufacturing practice (GMP) and MSEC under officially inspected good professional practice (GFP), both in its own facility in Offenbach. The programme is offered alongside — never instead of — guideline-based treatment such as PDE5 inhibitors; see erectile dysfunction treatment options.
| Component | Detail |
|---|---|
| Two products | Bone Marrow Concentrate (BMC) and Mesenchymal Stem Cell Secretome (MSEC), each manufactured under official authorisation; no marketing authorisation (experimental) |
| Authorisations | BMC § 20b / § 13 AMG · MSEC § 20b / § 20c AMG (German Medicines Act) |
| Location | Offenbach am Main, Germany |

ED in brief, the programme and its five components — the essentials at a glance.
You are hereIntroduction & Summary
What is erectile dysfunction (ED), in brief?
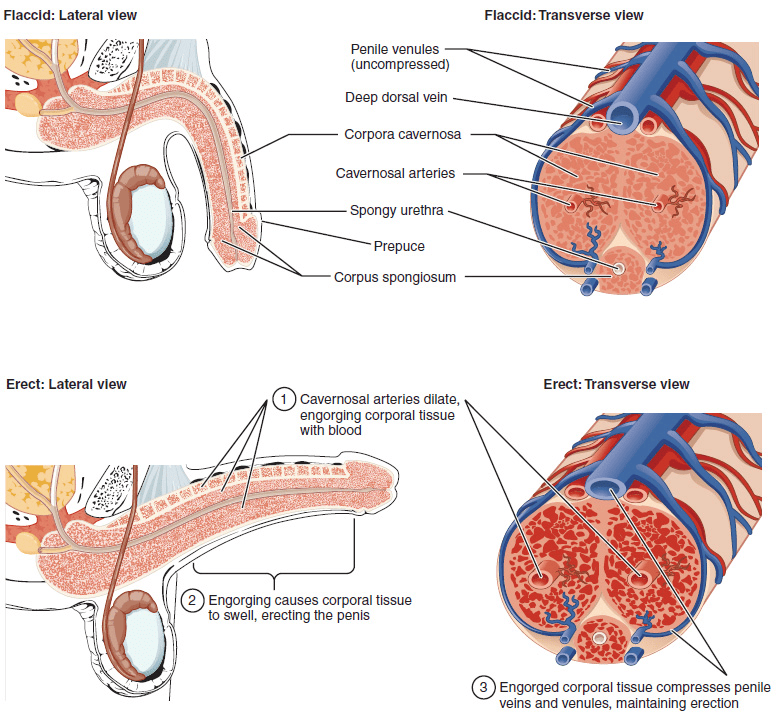
An erection happens when nerve signals relax the smooth muscle of the two erectile bodies of the penis (corpora cavernosa), so that they fill with blood and the draining veins are compressed. ED occurs when blood flow, nerve signals, hormones or the erectile tissue itself no longer work together properly.
Doctors distinguish vasculogenic ED (reduced arterial inflow or a venous leak), neurogenic ED (for example after radical prostatectomy or with diabetes), hormonal ED (for example low testosterone) and drug-induced ED. In psychogenic ED, thoughts or feelings prevent or impair an erection; many men have a mixed form. The typical sign is an erection that is too weak or does not last long enough for intercourse.
More details can be found below in our scientific section on erectile dysfunction.
What is the ANOVA ED programme?
ANOVA offers bone marrow concentrate (BMC) or MSC secretome (MSEC) for erectile dysfunction; we choose the product case by case, with BMC as our first choice. The programme contains a precision diagnostic work-up, BMC or MSEC injected into the erectile tissue, correction of a low testosterone level where needed and, optionally, components of our anti-ageing programme. Each component is selected individually; the programme is not a fixed package.
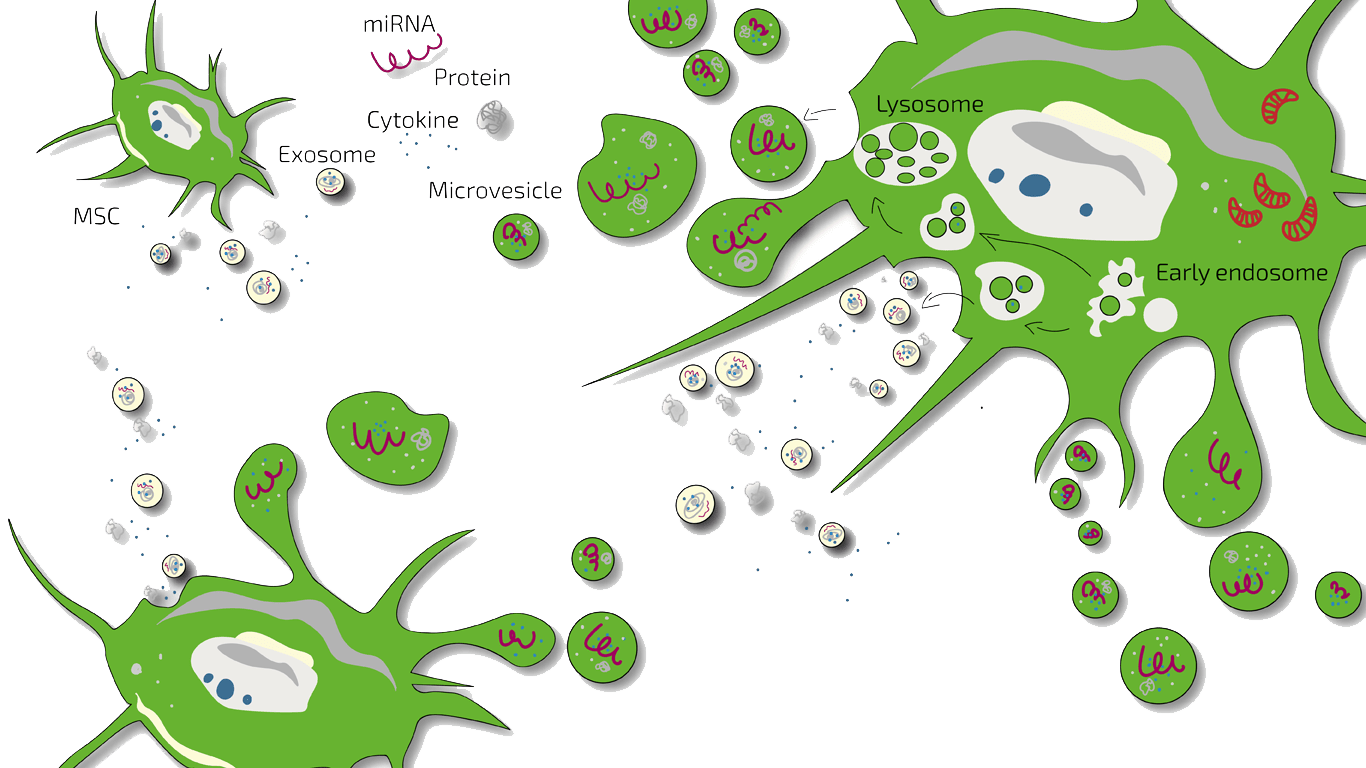
In most men with ED the problem lies in the blood vessels, nerves and smooth muscle of the erectile bodies; fibrosis and chronic inflammation of the erectile tissue are thought to contribute. BMC and MSEC are injected directly into this tissue. Stem cells are thought to act mainly through the factors they release, the secretome. The aim is to target fibrosis and inflammation; whether this can be achieved in men has not been shown. The efficacy hypothesis is set out in the clinical and scientific section below.
The ANOVA ED Programme — Components
Precision diagnostics
Before any treatment we look for the cause and stage of your ED. This includes blood tests with hormones, an examination by a urologist, Doppler ultrasound of the penile arteries and, where needed, MRI during an erection induced by an injection. The result decides whether BMC, MSEC or another treatment is the right path — including referral for established treatment.
Bone marrow concentrate (BMC)
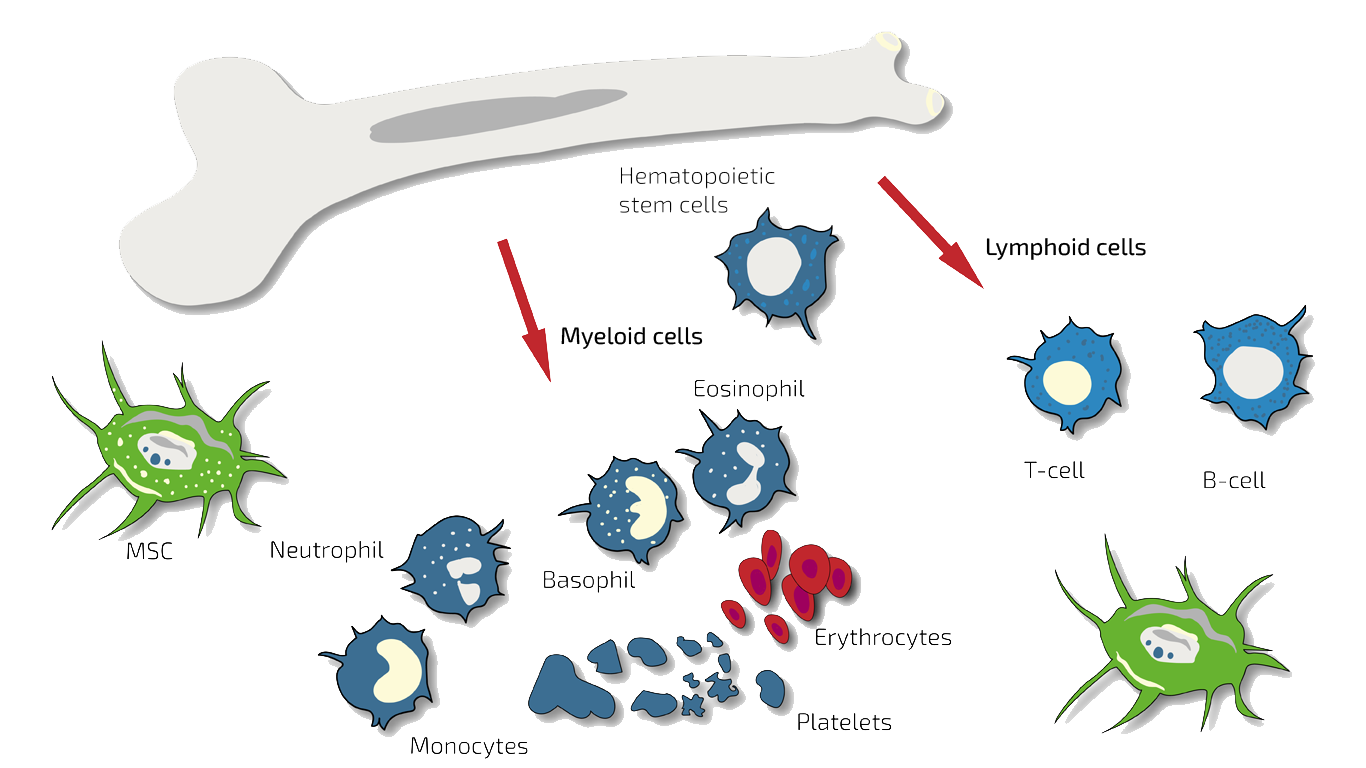
Your own bone marrow is collected from the pelvic bone under brief sedation, concentrated, tested and injected into the erectile bodies on the same day, during a two-day visit. Small external early studies with bone marrow-derived cells injected into the erectile tissue mainly examined safety; some reported better erectile function scores, without a control group.[7],[8] BMC has no marketing authorisation for ED.
MSC secretome (MSEC)
The signalling molecules released by your own mesenchymal stromal cells, obtained from fat tissue in a mini-liposuction and injected into the erectile bodies over several sessions. MSEC requires several visits: first a two-day visit for tissue collection, then 1 to 10 further visits for the treatment, depending on how many doses are given per session. Laboratory and animal studies suggest that such cell-free factors may protect the smooth muscle and blood vessel cells of the erectile tissue.[12],[13] There are no clinical studies of MSC secretome in men with ED; the evidence is set out in the clinical and scientific section below.
Hormonal correction
Where blood tests show a low testosterone level, it can be corrected with medication that stimulates the body's own testosterone production, rather than with testosterone replacement alone. The decision is made individually; current guidelines describe the diagnosis and treatment of male hypogonadism.[1]
Anti-ageing combination (optional)
Vascular ageing plays a part in both erectile dysfunction and general ageing. Treatment can therefore be combined with components of our anti-ageing programme, such as senolytic therapy or infusion therapy. There are no clinical studies of these components in ED; no senolytic is approved for ED, and we do not name individual substances on this website.
Which diagnostics do we use for ED at ANOVA IRM?
As there are many causes of ED, a comprehensive diagnostic work-up is needed to find the problem and, in turn, the right treatment. We therefore clarify the cause and stage of your ED and rule out other conditions as the trigger before recommending BMC, MSEC or another treatment.
Which tests are used to diagnose erectile dysfunction?
Diagnosis starts with a detailed medical and sexual history, a validated questionnaire such as the International Index of Erectile Function (IIEF-5) and a physical examination.[1] Blood tests cover blood sugar (HbA1c), blood lipids and a morning testosterone level. Doppler and duplex ultrasound of the penile arteries after an injection that triggers an erection show arterial inflow and venous outflow. MRI with contrast, including penile MRI during an induced erection, can show structural and vascular causes.[15]
What do we review before ED treatment at ANOVA IRM?
Before any treatment decision we review whether your ED is mainly vascular, nerve-related, hormonal, medication-related or psychological. A urologist from the Vitus Prostate Center in the same building can be involved in the examination. We also assess whether you are fit for the brief sedation required for tissue collection.
With BMC:
- Standard: no MRI required.
- Optional: further diagnostic MRI, with or without contrast, where your ED situation calls for it — for example a penile MRI during an induced erection to look for a venous leak.
- Optional: MRI- or CT-guided application.
With MSEC:
- Standard: an MRI of the abdominal wall to exclude a hernia is required before the liposuction, taken no more than four weeks beforehand. It can be done at home or at ANOVA IRM.
- Optional: CT support at ANOVA IRM while the dose is given.
- Optional: further MRI scans, with or without contrast, where your ED situation calls for them — for example to assess the penile arteries and veins.
All of these examinations can also be carried out by your own doctors at home; please send us the results. For your convenience they can also be done in-house at ANOVA IRM, where imaging and urology are available in the same building. The full diagnostic pathway is described on our diagnostics page.
Why ANOVA IRM for erectile dysfunction?
ANOVA IRM manufactures BMC and MSEC in its own facility in Offenbach, under German regulatory authorisation and official inspection since 2018. Urology, MRI and CT imaging are available in the same building. Why an autologous preparation used only for our own patients requires no marketing authorisation is set out on our regulatory status page.
What can you expect as a patient with erectile dysfunction?
Initial evaluation can begin remotely, by phone or video, without travel to Germany. Treatment itself requires an in-person visit to Offenbach am Main, less than 20 minutes from Frankfurt Airport. You receive an individual written cost estimate before any treatment decision.
Quick answers
Is there a cure for erectile dysfunction (ED)?
Not in general. It depends on the cause: ED can sometimes be resolved by treating its cause, such as a hormone deficiency, a side effect of medication or a psychological cause. Most vascular or nerve-related ED is managed rather than cured; tablets, injections, vacuum devices and penile implants treat the symptoms.[1] Low-intensity shockwave therapy is an option for mild vasculogenic ED, and BMC or MSEC at ANOVA IRM is an experimental option alongside these treatments, not a cure.[1]
Does stem cell therapy cure erectile dysfunction (ED)?
No. Stem cell therapy is not a cure for ED. BMC or MSEC at ANOVA IRM is intended to support the erectile tissue — alongside standard treatment such as PDE5 inhibitors, never instead of it.
Is ED stem cell therapy legal in Germany?
Yes, provided the provider holds the required official authorisations. ANOVA IRM manufactures BMC under a procurement authorisation (Section 20b AMG) and a manufacturing authorisation under Section 13 AMG, and MSEC under Section 20b and a manufacturing authorisation under Section 20c AMG. Both are given as an individual treatment attempt. The details are on our regulatory status page.
Is ED stem cell therapy safe?
Not without qualification. Every medical treatment carries risks, and your doctor explains them to you in detail before ED treatment. The safety of BMC and MSEC depends above all on product quality. Following the logic of the medicines authorities, products manufactured under official authorisation and inspection are to be regarded as safer than those from unregulated providers. Ask any provider for its authorisations and certificates; the regulators' view is summarised under unproven therapies.
What medication is used for erectile dysfunction (ED)?
Tablets from the group of PDE5 inhibitors are the first choice for ED; other options include medication injected into the erectile tissue or placed in the urethra. BMC or MSEC at ANOVA IRM is offered alongside this medication, not instead of it.
Who qualifies, what the process actually involves, and what it costs — step by step.
You are hereED Treatment: Eligibility, Process & Cost
BMC treatment for ED at ANOVA IRM costs approximately €8,000–€9,000, and MSEC treatment approximately €20,000–€36,000, depending on the number of doses used. BMC requires one two-day outpatient visit to Offenbach, Germany. MSEC requires a two-day outpatient visit for tissue collection, followed by further visits for the applications according to your individual treatment plan. Treatment is available to men with persistent ED with a physical cause.
What does the ED treatment timeline look like?
- 01
Initial evaluation
Remote, by phone or video — typically 2 weeks to a few months
- 02
Preliminary screening
In your home country, to avoid unnecessary travel
- 03
First visit — bloodwork and collection
Two-day outpatient visit. Day 1: consultation, informed consent and blood tests. Day 2 with BMC: bone marrow collection, preparation, testing and application (about 2–4 hours). Day 2 with MSEC: mini-liposuction under brief sedation, if the results are normal
- 04
Production and quality control (MSEC)
Approximately 4 weeks; yields 10 doses
- 05
Storage (MSEC)
Up to 2 years, for a longer individual treatment plan
- 06
Application schedule
Set individually: BMC on day 2 of the first visit; MSEC one or two doses per session, spread over several visits
Who qualifies for ED treatment, and what are the requirements?
We treat men with persistent erectile dysfunction with a suspected or confirmed physical cause, after a full diagnostic work-up. This includes vasculogenic and neurogenic ED, ED with diabetes or another metabolic condition, ED after radical prostatectomy or other pelvic treatment where medically appropriate, and ED after penile or pelvic injury. Many men we see have tried PDE5 inhibitors or injections with limited effect, or cannot use them. You need to be medically fit for the bone marrow collection (BMC) or the mini-liposuction under brief sedation (MSEC), and able to travel to Offenbach.
What are the contraindications for ED treatment?
Our treatments are experimental. We treat only people for whom, after medical assessment, we consider the benefit-risk balance to support treatment.
Applies to all ANOVA treatments:
- Active cancer within the last two years
- Under the age of legal majority
- Pregnancy or breastfeeding
- Active infectious disease (hepatitis A, B, C, HIV, syphilis or other)
Specific to ED:
- Surgery for prostate cancer less than two years ago
- ED that is primarily psychological (psychogenic) — here a different treatment pathway is more suitable
- Unable to breathe unaided, or difficulty breathing in the supine position (sedation for tissue collection)
- Psychiatric disorder that would prevent informed consent or cooperation
What does ED therapy at ANOVA IRM involve, step by step?
What screening is needed before you travel for ED treatment?
Before you travel, a preliminary screening in your home country helps to avoid an unnecessary journey — for BMC as well as for MSEC. This is usually a blood test for medical or infectious reasons against treatment, together with your existing urological findings.
What happens at your first ED visit to Offenbach, Germany?
The first visit takes two days in Offenbach and is outpatient, for BMC and MSEC alike. On the first day your doctor explains the treatment and obtains your consent, and blood tests are carried out at ANOVA IRM. With BMC, bone marrow is collected from the pelvic bone under brief sedation on the second day. It is concentrated, tested and injected into the erectile bodies the same day, which takes about two to four hours. With MSEC, a small amount of abdominal fat is collected on the second day by mini-liposuction under brief sedation, if the results are normal. The first MSEC application usually follows four to six weeks later.
How are your BMC and MSEC for ED produced and quality-controlled?
BMC: BMC is prepared from your bone marrow on the day of collection in our own facility, under a manufacturing authorisation and good manufacturing practice (GMP). Part of the quality control takes place on the same day, before the application; further tests are completed afterwards.
MSEC: Mesenchymal stromal cells are isolated from the collected fat tissue and expanded under controlled conditions in our own facility, under official authorisation and officially inspected good professional practice (GFP). These cells are then used to produce your MSEC preparation — the signalling molecules they release, not the living cells. Production and quality control take approximately four weeks and yield 10 doses per production cycle. Each patient batch is tested with methods validated according to the European Pharmacopoeia (Ph. Eur.) and GMP, and the complete quality control is finished before the first application. The released secretome is stored at −80 °C and keeps for up to two years.
How often are BMC and MSEC applied in ED?
ED with a physical cause is often a chronic condition. With MSEC we therefore plan several sessions rather than a single application; see the timeline above.
The schedule is set individually for each patient, for example:
- BMC: one application on the second day of the first visit; a repeat is possible after assessment.
- MSEC: one or two doses per session, depending on your individual needs.
- If you live close by: one MSEC dose per session, at shorter intervals.
- If you live further away: two MSEC doses per session, so that fewer visits are needed.
- Standard route for ED: injection into the erectile bodies (intracavernous). A urologist places the needle, and an ANOVA IRM physician administers BMC or MSEC. This is intended to bring the product directly to the tissue in which the erection takes place.
- No intravenous alternative: we do not give BMC or MSEC intravenously for ED, because in our assessment it would not reach the erectile tissue in a useful way.
Injections into the erectile bodies are standard urological procedures when performed by experienced physicians; your doctors discuss the procedure and its risks with you beforehand.
What does ED treatment with BMC or MSEC cost?
BMC treatment for ED costs approximately €8,000 to €9,000, and MSEC treatment approximately €20,000 to €36,000; both are billed according to the German Medical Fee Schedule (GOÄ). For MSEC, the base package — the mini-liposuction and the first three MSEC doses — costs approximately €20,000; each further dose is charged separately at approximately €2,250. If two doses are given in one session, each dose is charged; the total therefore depends on the number of doses. The total also depends on additional examinations and your sedation or anaesthesia preferences. You receive an individual written estimate before any treatment decision. Travel, accommodation and other personal expenses are separate. Experimental ED treatment is generally self-funded; you can still ask your insurer about possible reimbursement. All prices are subject to change.
With MSEC, a double liposuction is possible and yields 20 doses, allowing more doses from a single collection. The cost is correspondingly higher and is shown in your individual estimate.
Why does the cost of ED treatment vary?
All treatments at ANOVA IRM are billed according to the German Medical Fee Schedule (Gebührenordnung für Ärzte, GOÄ). Within it, the cost varies mainly with the product and, for MSEC, with the number of doses. The exact cost of your treatment plan is set out in your individual written cost estimate.
Frequently asked questions — eligibility, process and travel
How are BMC and MSEC administered for ED?
By injection into the erectile bodies (intracavernous): a urologist places the needle, and an ANOVA IRM physician administers the product. BMC is given on the second day of the first visit; MSEC is given as one or two doses per session, over several sessions.
Can BMC or MSEC help with ED after prostate cancer treatment?
Not proven. After surgery for prostate cancer, ED results mainly from damage to the cavernous nerves. Small uncontrolled studies have used bone marrow-derived cells[8] or adipose-derived cells[11] in this situation and mainly examined safety. At ANOVA IRM, treatment is possible at the earliest two years after the operation, and only if your follow-up shows no signs of active cancer. We assess this together with the findings of your treating urologist.
How long does the whole ED process take?
The initial evaluation can begin remotely and takes about two weeks to several months. BMC is completed within one two-day visit. With MSEC, tissue collection takes about two days in Offenbach, followed by about four weeks of production and quality control and then the sessions of your treatment plan.
Does health insurance cover ED stem cell therapy in Germany?
No. Health insurers generally do not cover experimental ED treatment, so it is usually self-funded. You can still submit an individual request to your insurer.
Should I stop my current ED medication such as sildenafil or tadalafil?
No. The programme complements guideline-based treatment. Please continue to work closely with your treating urologist or doctor.
Should I continue my existing ED treatment such as sildenafil or tadalafil?
Yes, where it helps you. The programme complements established ED treatment rather than replacing it.
How often do I need to travel to Germany for ED stem cell treatment?
With BMC usually once, for two days. With MSEC, after a remote first assessment, a two-day visit to Offenbach for blood tests and tissue collection is needed, followed by visits for the sessions of your plan. Offenbach is less than 20 minutes from Frankfurt Airport. The full process is described on our BMC page.
What medical records should I send for an ED assessment?
Please send us your most recent documents; we will ask if we need anything else. Helpful are, for example, letters from your urologist or doctor, your current medication, recent blood tests including testosterone, blood sugar and lipids, and any Doppler ultrasound or MRI findings.
Does ANOVA IRM treat international patients with ED?
Yes. We advise patients from abroad in English, and your first ED assessment takes place by phone or video, so no travel is needed at this stage.
ED biology, standard of care, the rationale behind each component and all references.
You are hereED: Clinical & Scientific Evidence
1. What happens in erectile dysfunction?
Erectile dysfunction (ED), sometimes also called impotence, means that an erection is not firm enough or does not last long enough for satisfactory intercourse. Erection of the penis is achieved by filling the erectile bodies with blood. Triggered by psychological or physical stimuli, nerve signals travel from the brain via the spinal cord to the cavernous nerves, which release nitric oxide (NO) in the erectile bodies. NO relaxes the smooth muscle via the second messenger cyclic guanosine monophosphate (cGMP), so that the erectile bodies fill with blood; this trigger phase requires the nerves to function normally.[1]
The enlarging erectile bodies compress the draining veins between the erectile bodies and the tunica albuginea, which closes the venous outflow and produces a full erection (veno-occlusion). The erection subsides when the enzyme phosphodiesterase type 5 (PDE5) breaks down cGMP, the smooth muscle contracts and blood drains again. The key components are therefore the endothelial cells, the cavernous smooth muscle cells and the release of NO from the cavernous nerves.
What causes erectile dysfunction, and what are the risk factors?
ED usually has several contributing factors. What triggers it and what makes it progress are two different questions; progression is covered in the next section.[1]
- Age: the most important single factor.
- Cardiovascular and metabolic disease: high blood pressure, heart disease, diabetes mellitus, raised blood lipids and obesity.
- Smoking, lack of exercise and alcohol.
- Surgery and radiotherapy in the pelvis: especially radical prostatectomy, the standard operation for prostate cancer, which can damage the cavernous nerves.
- Hormones: low testosterone (hypogonadism), thyroid disorders, raised prolactin.
- Medication: for example certain antidepressants, antipsychotics, blood pressure medication, medication for stomach ulcers and lipid-lowering medication.
- Psychological factors: depression, anxiety, performance anxiety and relationship problems.
What drives the progression of erectile dysfunction?
After damage to the cavernous nerves, for example after radical prostatectomy, the resulting neurogenic ED may be reversible at first. In the longer term, reduced NO production and loss of cavernous smooth muscle cells can lead to atrophy and fibrosis of the erectile bodies and to permanent ED. In biopsies of men after radical prostatectomy, smooth muscle decreased and collagen increased over the following months — a sign of progressive fibrosis of the erectile tissue.[6] High blood sugar in diabetes and raised blood lipids can act through similar mechanisms.[1] Chronic low-grade inflammation is regarded, alongside cardiovascular risk factors and hormones, as one of the links through which damage to the vessel lining (endothelium) develops.[4] Men with ED more often have raised inflammatory markers; whether inflammation contributes to causing ED has not been established.[4],[5] This is where our programme aims — at the course of the condition in the erectile tissue, not at its original cause, and not with the claim of a cure.
2. What is the guideline-based standard of care for erectile dysfunction?
Treatment starts with lifestyle changes and the treatment of risk factors and underlying conditions. Oral PDE5 inhibitors such as sildenafil, tadalafil, vardenafil and avanafil are the established first-line medication; they improve the NO–cGMP pathway and help many men.[3],[1] Some men cannot take or tolerate them, and others do not respond sufficiently, particularly where the nerves, blood vessels or erectile tissue are severely damaged.
Further options include testosterone therapy for proven hypogonadism, psychosexual therapy, medication injected into the erectile bodies or placed in the urethra (alprostadil), vacuum erection devices and low-intensity shockwave therapy for mild vasculogenic ED. A penile prosthesis is the last option.[1] In selected men with an isolated arterial narrowing or a venous leak, vascular procedures such as arterial revascularisation or embolisation of the leaking veins are possible; the evidence for them is limited.[1]
Important This is the guideline-based standard of care. ANOVA IRM's programme is offered alongside — not in place of — appropriate established treatment.
How is erectile dysfunction diagnosed, and what do we not do ourselves?
ED is diagnosed from the medical and sexual history, validated questionnaires, a physical examination and blood tests. Depending on the findings, Doppler ultrasound, tests of nerve function or a cardiovascular assessment follow. Treating underlying conditions such as diabetes, high blood pressure or heart disease, as well as psychosexual therapy, stays with your family doctor, urologist or specialist.
We carry out the imaging ourselves: MRI with or without contrast, including penile MRI during an induced erection, and CT support where needed. It takes place at the Institut für Bildgebende Diagnostik in the same building, also owned by Dr. Stehling; the urological examination and Doppler ultrasound are carried out with a urologist from the Vitus Prostate Center. Please bring your existing findings from your treating doctor.
3. What is the scientific rationale for ED treatment, component by component?
Precision diagnostics and penile MRI
A standard scan of the flaccid penis cannot show how the erectile tissue, arteries and veins behave during an erection. MRI during a pharmacologically induced erection can show structural and vascular causes, including arterial inflow and a venous leak; MRI also characterises the tunica albuginea and the erectile tissue.[15] The result decides whether a man is a candidate for BMC or MSEC, or whether another treatment is more suitable.
Bone marrow concentrate (BMC)
An industry-associated phase 1 study injected bone marrow concentrate into the erectile bodies of 40 men whose ED did not respond to PDE5 inhibitors; a registry added 100 further men. Side effects were limited to short-term bruising; the mean IIEF-5 score improved by 2 to 9 points depending on the protocol, without a control group.[7]
In a French pilot study, 12 men with ED after radical prostatectomy received escalating doses of bone marrow mononuclear cells; there were no serious side effects, and erectile function scores improved at six months.[8] Two small open-label studies from Jordan injected cultured bone marrow-derived MSCs — a different product from BMC — into the erectile bodies of 4 and 8 diabetic men, followed for up to 24 months.[9],[10] In the phase 2 study, erectile function scores improved over the first months but had returned to baseline levels at 24 months.[10] None of these studies was randomised or placebo-controlled.
MSC secretome (MSEC)
There are no clinical studies of MSC secretome in men with ED. In rats with cavernous nerve injury, a cell-free lysate of adipose-derived stem cells improved erectile function to a similar extent as the cells themselves.[12] Exosomes from MSCs improved erectile function and reduced damage to the erectile tissue in rat models of artery injury and cavernous nerve injury.[13],[14]
In humans, a single injection of freshly isolated adipose-derived regenerative cells — living cells, not a secretome — was studied in 17 men with ED after radical prostatectomy. It was well tolerated, and 8 of the 17 men were able to have intercourse again; there was no control group.[11] Because MSEC is cell-free, these studies provide background for the rationale, not direct evidence for MSEC.
What is the efficacy hypothesis behind MSC secretome in ED?
MSCs are thought to act mainly through the factors they release — exosomes and other extracellular vesicles, growth factors, cytokines and microRNAs — rather than by settling in the tissue. In ED, these factors are being studied for possible effects on the endothelium, the survival of smooth muscle cells and the cavernous nerves. Possible endpoints are a slowing of the fibrosis of the erectile tissue, in which smooth muscle is gradually replaced by collagen, and a reduction of chronic inflammation in the erectile tissue. MSEC is injected into the erectile bodies so that these factors reach the tissue in which the erection takes place. Whether this changes the course of ED in men has not been shown.
Hormonal correction
Low testosterone can contribute to ED and reduce the response to PDE5 inhibitors. Guidelines recommend measuring testosterone in men with ED and treating proven hypogonadism.[1] Where appropriate, we use medication that stimulates the body's own testosterone production; its use for this purpose is decided individually and discussed with you.
Anti-ageing combination
Vascular and endothelial ageing play a part in both ED and general ageing. The scientific rationale for senolytic therapy and infusion therapy is described on our anti-ageing pages; there are no clinical studies of these components in ED.
Talk to us about current changes or additions to the ED programme. For several conditions ANOVA IRM also offers infusion therapies alongside the components described above.
4. Where does our own ED evidence stand?
ANOVA IRM does not yet have an evaluated dataset for erectile dysfunction. This section is therefore a summary of published external evidence, not of our own patient outcomes. We will publish our own ED data once a sufficiently large group with sufficient follow-up can be reported.
Individual patients describe their experiences on our testimonials page, including a man treated with BMC for ED. These are personal accounts of single cases, not evidence that a treatment works, and results differ from person to person.
What the published evidence does not yet tell us
- Laboratory and animal studies consistently report effects relevant to erectile function, but they cannot show whether a treatment helps men with ED.
- Human studies are small, open-label phase 1 and phase 2 studies, mostly in diabetic men and after radical prostatectomy; none is randomised or placebo-controlled.
- The products studied differ from BMC and MSEC at ANOVA IRM in source, preparation and dose.
- European urology guidelines summarise 18 early-phase trials with 373 patients: safety has been confirmed, but the efficacy data are not sufficient for a recommendation.[1]
- Where longer follow-up exists, improvements have faded over time; in one phase 2 study, scores had returned to baseline after 24 months.
- No stem cell-based ED treatment is an approved standard treatment in Germany or the EU.
5. Legal framework for BMC and MSEC in ED
BMC is an advanced therapy medicinal product; ANOVA IRM manufactures it under a procurement authorisation (Section 20b AMG) and a manufacturing authorisation under Section 13 AMG. MSEC is an autologous tissue preparation, manufactured under a procurement authorisation (Section 20b AMG) and a manufacturing authorisation under Section 20c AMG. All authorisations were issued and are regularly inspected by the Hessian State Office for Health and Care (HLfGP). The individual treatment attempt (individueller Heilversuch) concerns the administration only and follows full disclosure and informed consent; because both products are used only for ANOVA IRM's own patients, no authorisation under Section 4b, no marketing authorisation under Section 21 and no approval under Section 21a AMG is required. The full derivation is on our regulatory status page.
6. Frequently asked questions — erectile dysfunction (ED), evidence and approval status
Is stem cell therapy approved for erectile dysfunction (ED) anywhere?
No. To our knowledge, no stem cell-based ED treatment has a marketing authorisation in Germany, the EU or elsewhere. Current European urology guidelines do not recommend it: 18 early-phase trials with 373 patients have confirmed safety but do not provide enough efficacy data.[1] ANOVA IRM gives BMC and MSEC as an individual treatment attempt after individual medical assessment and informed consent.
Are stem cell studies evidence that BMC or MSEC works in ED?
No. The published studies used different products, and the human studies are small and uncontrolled. They show that the approach is being investigated and that early safety data are available, not that BMC or MSEC works in ED.
How common is erectile dysfunction (ED)?
What are the symptoms of erectile dysfunction (ED)?
The main symptom of ED is an erection that is not firm enough, or does not last long enough, for satisfactory intercourse. Symptoms differ between men and can change over time.
- An erection that is too weak for intercourse
- An erection that cannot be maintained until the end of intercourse
- Fewer or weaker spontaneous and morning erections
- A curved or painful erection may point to a structural cause and needs separate assessment
Which forms of erectile dysfunction (ED) are there, and how do they progress?
ED is classified by its cause: vasculogenic, neurogenic, endocrine, drug-induced, psychogenic or mixed ED. The course depends on the cause and on whether it can be treated.
- Vasculogenic ED: reduced arterial inflow (arteriogenic ED, often with atherosclerosis) or a venous leak (veno-occlusive dysfunction); the most common form.
- Neurogenic ED: damage to the nerves supplying the penis, for example after radical prostatectomy (post-prostatectomy ED), with diabetes, spinal cord injury or multiple sclerosis.
- Endocrine (hormonal) ED: for example with low testosterone.
- Drug-induced ED: as a side effect of medication.
- Psychogenic ED: thoughts or feelings prevent or impair an erection; spontaneous and morning erections are often preserved.
- Mixed ED: several of these causes together; common in practice.
What complications can erectile dysfunction (ED) cause?
ED can strain relationships and self-esteem and is associated with depressive symptoms. Because vascular ED and heart disease share risk factors, ED can be an early sign of cardiovascular disease; guidelines therefore recommend a cardiovascular risk assessment.[1]
Important Pages
Questions people usually ask next. Each is answered in full on its own page.
- Who are we?
- Is ANOVA legal?
- Is stem cell therapy safe?
- What is MSC secretome (MSEC)?
- What is BMC (Bone Marrow Concentrate)?
- What are stem cells?
- What should I ask when looking for a stem cell treatment?
- Which conditions do we treat?
- Erectile dysfunction treatment options — standard and emerging
- MSC secretome and erectile dysfunction — research overview and a patient report
Affiliations of ANOVA
ANOVA IRM shares its premises in Offenbach with two further institutions owned by Dr. Stehling: the Institut für Bildgebende Diagnostik (IBDO), providing MRI and CT imaging, and the Vitus Prostate Center, whose urologists are involved in the examination and treatment of men with erectile dysfunction. Because imaging and urology are available in the same building, condition-specific diagnostics — including penile MRI and CT-guided procedures — can be performed in-house rather than referred elsewhere. See diagnostics at ANOVA IRM.
References — erectile dysfunction literature
We maintain general literature on MSCs, extracellular vesicles and secretome on our MSC secretome page, and on bone marrow on the BMC page.
Guidelines, epidemiology and standard of care
- [1] Salonia A, Capogrosso P, Boeri L, et al. European Association of Urology Guidelines on Male Sexual and Reproductive Health: 2025 Update on Male Hypogonadism, Erectile Dysfunction, Premature Ejaculation, and Peyronie's Disease. Eur Urol. 2025;88(1):76–102. doi:10.1016/j.eururo.2025.04.010. PMID: 40340108.
- [2] Feldman HA, Goldstein I, Hatzichristou DG, Krane RJ, McKinlay JB. Impotence and its medical and psychosocial correlates: results of the Massachusetts Male Aging Study. J Urol. 1994;151(1):54–61. doi:10.1016/s0022-5347(17)34871-1. PMID: 8254833.
- [3] Goldstein I, Lue TF, Padma-Nathan H, Rosen RC, Steers WD, Wicker PA; Sildenafil Study Group. Oral sildenafil in the treatment of erectile dysfunction. N Engl J Med. 1998;338(20):1397–1404. doi:10.1056/NEJM199805143382001. PMID: 9580646.
- [4] Gandaglia G, Briganti A, Jackson G, et al. A systematic review of the association between erectile dysfunction and cardiovascular disease. Eur Urol. 2014;65(5):968–978. doi:10.1016/j.eururo.2013.08.023. PMID: 24011423.
- [5] Esposito K, Giugliano F, Di Palo C, et al. Effect of lifestyle changes on erectile dysfunction in obese men: a randomized controlled trial. JAMA. 2004;291(24):2978–2984. doi:10.1001/jama.291.24.2978. PMID: 15213209.
- [6] Iacono F, Giannella R, Somma P, Manno G, Fusco F, Mirone V. Histological alterations in cavernous tissue after radical prostatectomy. J Urol. 2005;173(5):1673–1676. doi:10.1097/01.ju.0000154356.76027.4f.
Human studies with bone marrow-derived cells
- [7] Bieri M, Said E, Antonini G, Dickerson D, Tuma J, Bartlett CE, Patel AN, Gershman A. Phase I and registry study of autologous bone marrow concentrate evaluated in PDE5 inhibitor refractory erectile dysfunction. J Transl Med. 2020;18(1):24. doi:10.1186/s12967-019-02195-w. PMID: 31937310. Manufacturer involvement: one author affiliation is Creative Medical Health, San Diego, which offers the CaverStem procedure studied; no control group.
- [8] Yiou R, Hamidou L, Birebent B, et al. Safety of intracavernous bone marrow-mononuclear cells for postradical prostatectomy erectile dysfunction: an open dose-escalation pilot study. Eur Urol. 2016;69(6):988–991. doi:10.1016/j.eururo.2015.09.026. PMID: 26439886.
- [9] Al Demour S, Jafar H, Adwan S, et al. Safety and potential therapeutic effect of two intracavernous autologous bone marrow derived mesenchymal stem cells injections in diabetic patients with erectile dysfunction: an open label phase I clinical trial. Urol Int. 2018;101(3):358–365. doi:10.1159/000492120. PMID: 30173210.
- [10] Al Demour S, Adwan S, Jafar H, Alhawari H, Awidi A. Stem cell therapy in diabetic men with erectile dysfunction: a 24-month follow-up of safety and efficacy of two intracavernous autologous bone marrow derived mesenchymal stem cells injections, an open label phase 2 clinical trial. Basic Clin Androl. 2024;34:13. doi:10.1186/s12610-024-00229-y. PMCID: PMC11225209.
Human study with adipose-derived cells
- [11] Haahr MK, Jensen CH, Toyserkani NM, et al. Safety and potential effect of a single intracavernous injection of autologous adipose-derived regenerative cells in patients with erectile dysfunction following radical prostatectomy: an open-label phase I clinical trial. EBioMedicine. 2016;5:204–210. doi:10.1016/j.ebiom.2016.01.024. PMID: 27077129.
Laboratory and animal studies with cell-free preparations
- [12] Albersen M, Fandel TM, Lin G, et al. Injections of adipose tissue-derived stem cells and stem cell lysate improve recovery of erectile function in a rat model of cavernous nerve injury. J Sex Med. 2010;7(10):3331–3340. doi:10.1111/j.1743-6109.2010.01875.x. PMID: 20561166.
- [13] Liu Y, Zhao S, Luo L, et al. Mesenchymal stem cell-derived exosomes ameliorate erection by reducing oxidative stress damage of corpus cavernosum in a rat model of artery injury. J Cell Mol Med. 2019;23(11):7462–7473. doi:10.1111/jcmm.14615. PMCID: PMC6815831.
- [14] Ouyang X, Han X, Chen Z, Fang J, Huang X, Wei H. MSC-derived exosomes ameliorate erectile dysfunction by alleviation of corpus cavernosum smooth muscle apoptosis in a rat model of cavernous nerve injury. Stem Cell Res Ther. 2018;9:246. doi:10.1186/s13287-018-1003-1. PMID: 30257719. PMCID: PMC6158845. Correction: Stem Cell Res Ther. 2022;13:508.
Diagnostic imaging
- [15] Regent B, Nowak K, Skrobisz K, Matuszewski M, Studniarek M. MRI of the Scrotum and Penis: Current Applications and Clinical Relevance. Diagnostics. 2025;15(24):3134. doi:10.3390/diagnostics15243134. PMCID: PMC12732017. Open access, CC BY 4.0.